Related Experiment Video
Updated: May 5, 2026
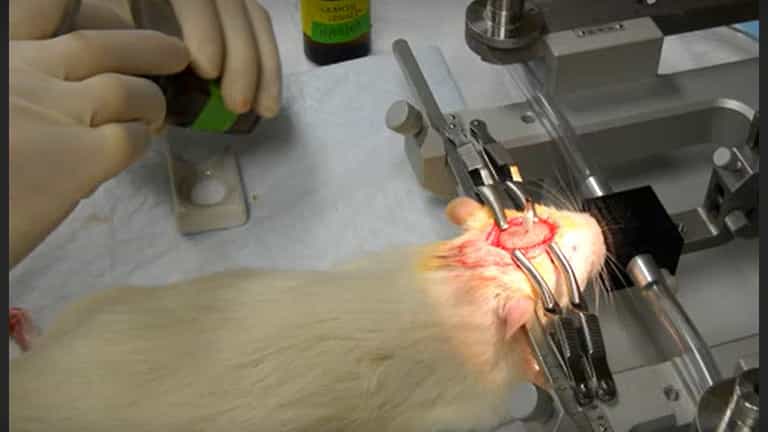

Novel Apparatus and Method for Drug Reinforcement
Published on: August 21, 2010
Potentiation of cocaine-induced coronary vasoconstriction by beta-adrenergic blockade
R A Lange1, R G Cigarroa, E D Flores
1University of Texas Southwestern Medical Center, Parkland Memorial Hospital, Dallas.

Insights
Beta-adrenergic blockade potentiates cocaine-induced coronary artery vasoconstriction. These findings suggest that beta-adrenergic blocking agents should be avoided in patients experiencing cocaine-associated myocardial ischemia or infarction.
Area of Science:
- Cardiology
- Pharmacology
Background:
- Cocaine use is associated with cardiovascular complications, including myocardial infarction.
- The role of beta-adrenergic blockade in cocaine-induced coronary vasoconstriction is not fully understood.
Purpose of the Study:
- To investigate whether beta-adrenergic blockade exacerbates cocaine-induced coronary artery vasoconstriction.
Main Methods:
- A randomized, double-blind, placebo-controlled trial was conducted in a cardiac catheterization laboratory.
- Thirty patients undergoing evaluation for chest pain received intranasal cocaine (2 mg/kg) or saline, followed by intracoronary propranolol.
- Measurements included heart rate, arterial pressure, coronary sinus blood flow, and coronary arterial dimensions.
Main Results:
- Cocaine administration increased arterial pressure and rate-pressure product, decreased coronary sinus blood flow, and reduced coronary arterial diameters.
- Subsequent intracoronary propranolol administration further decreased coronary sinus blood flow and increased coronary vascular resistance.
- These changes indicate potentiation of cocaine-induced vasoconstriction by beta-adrenergic blockade.
Conclusions:
- Beta-adrenergic blockade potentiates cocaine-induced coronary vasoconstriction.
- Beta-adrenergic blocking agents should likely be avoided in patients with cocaine-associated myocardial ischemia or infarction.
Study Objective:
To determine whether beta-adrenergic blockade augments cocaine-induced coronary artery vasoconstriction.
Design:
Randomized, double-blind, placebo-controlled trial.
Setting:
A cardiac catheterization laboratory in an urban teaching hospital.
Patients:
Thirty clinically stable patient volunteers referred for catheterization for evaluation of chest pain.
Interventions:
Heart rate, arterial pressure, coronary sinus blood flow (by thermodilution), and epicardial left coronary arterial dimensions were measured before and 15 minutes after intranasal saline or cocaine administration (2 mg/kg body weight) and again after intracoronary propranolol administration (2 mg in 5 minutes).
Measurements And Main Results:
No variables changed after saline administration. After cocaine administration, arterial pressure and rate-pressure product increased; coronary sinus blood flow fell (139 +/- 28 [mean +/- SE] to 120 +/- 20 mL/min); coronary vascular resistance (mean arterial pressure divided by coronary sinus blood flow) rose (0.87 +/- 0.10 to 1.05 +/- 0.10 mm Hg/mL.min); and coronary arterial diameters decreased by between 6% and 9% (P less than 0.05 for all variables). Subsequently, intracoronary propranolol administration caused no change in arterial pressure or rate-pressure product but further decreased coronary sinus blood flow (to 100 +/- 14 mL/min) and increased coronary vascular resistance (to 1.20 +/- 0.12 mm Hg/mL.min) (P less than 0.05 for both).
Conclusions:
Cocaine-induced coronary vasoconstriction is potentiated by beta-adrenergic blockade. Beta-adrenergic blocking agents probably should be avoided in patients with cocaine-associated myocardial ischemia or infarction.


Related Concept Videos
 01:26
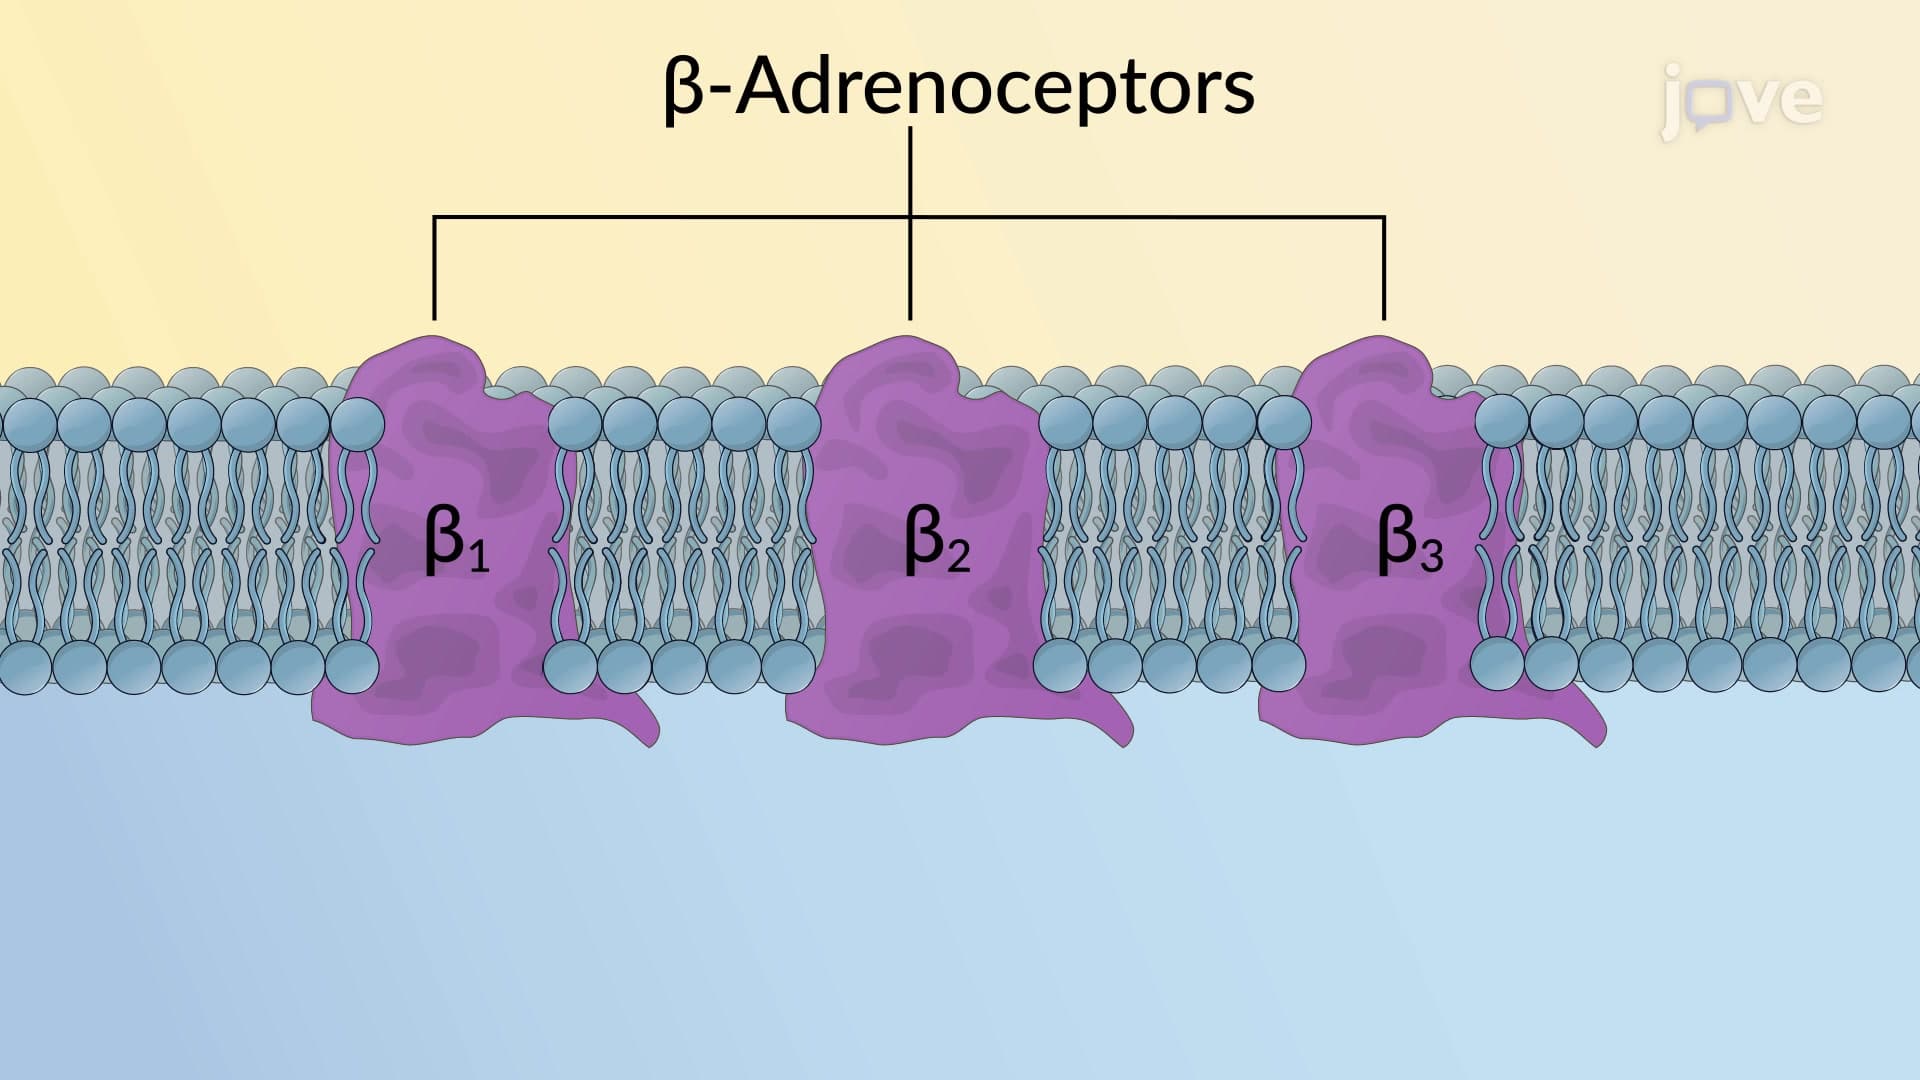
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:25
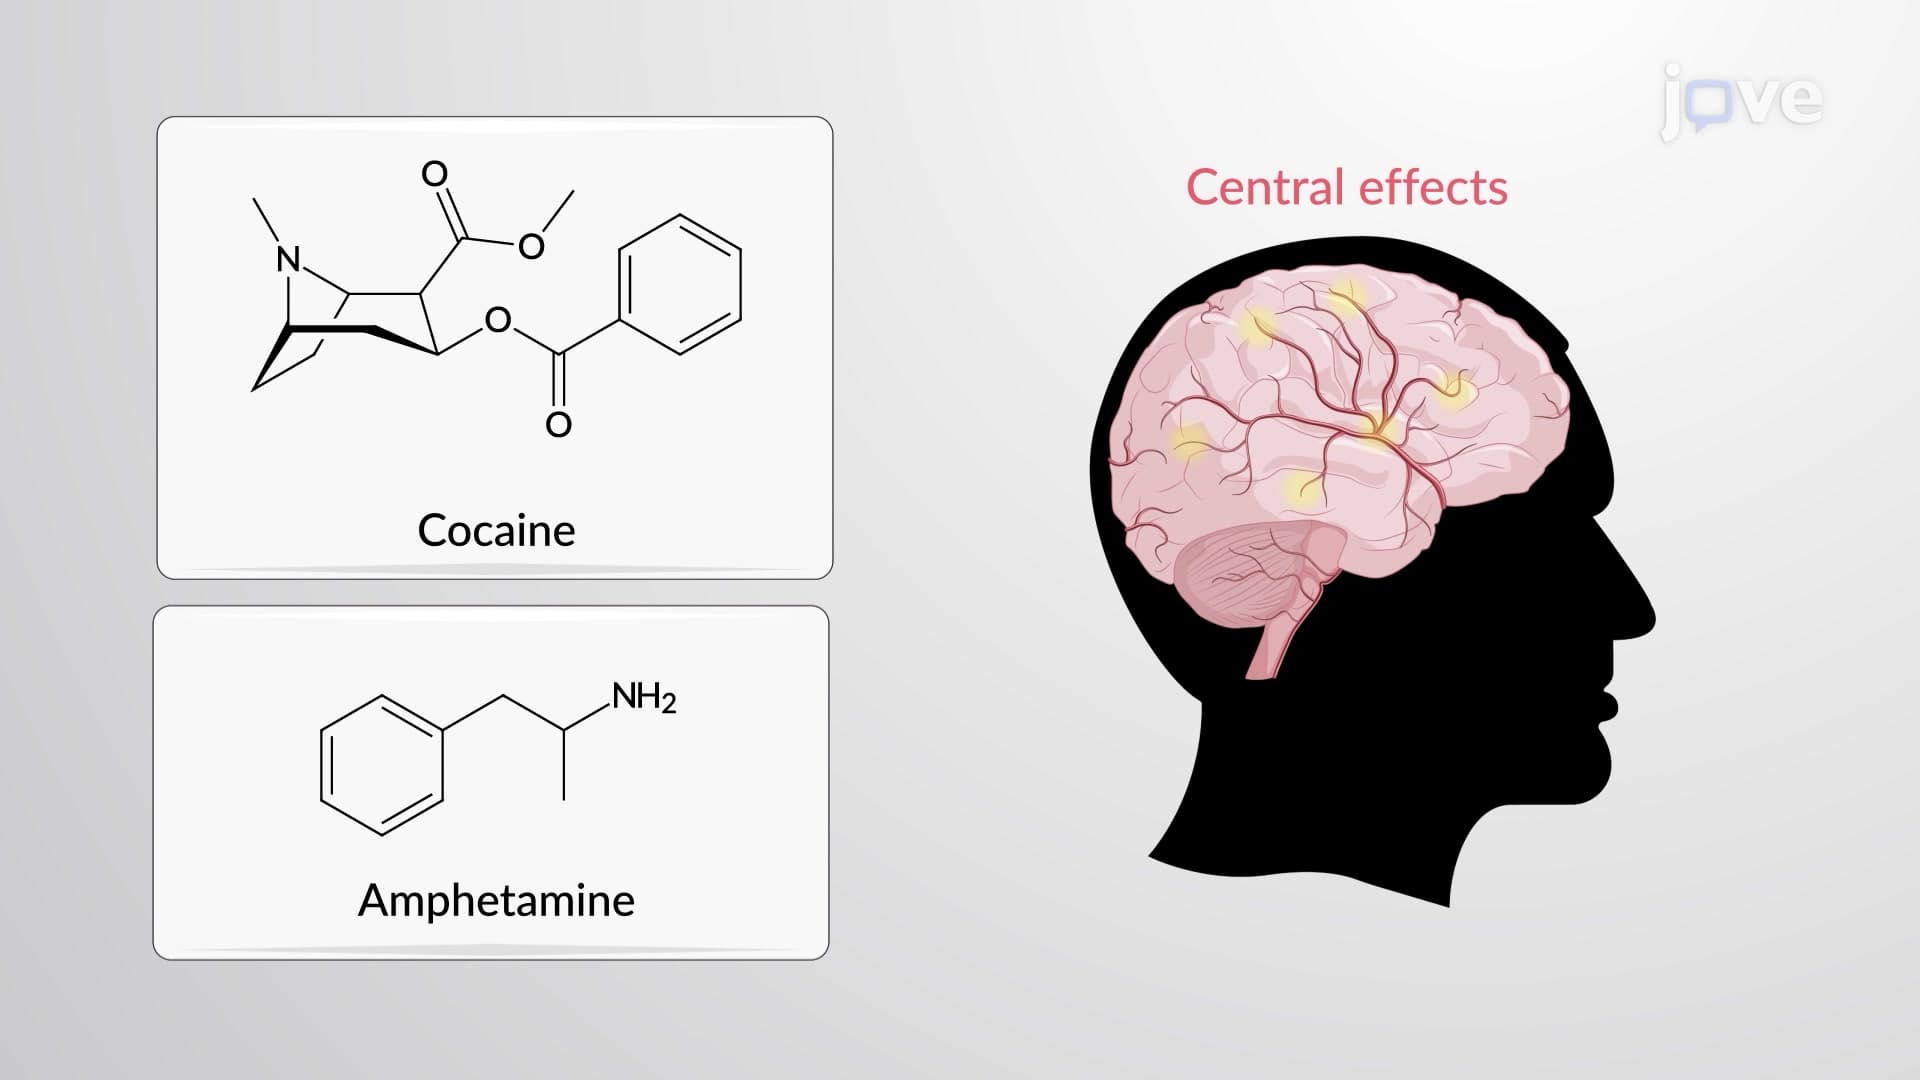
Adrenergic Agonists: Indirect-Acting Agents
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:22
Heart Failure Drugs: β-Blockers