Related Experiment Video
Updated: Jun 20, 2026
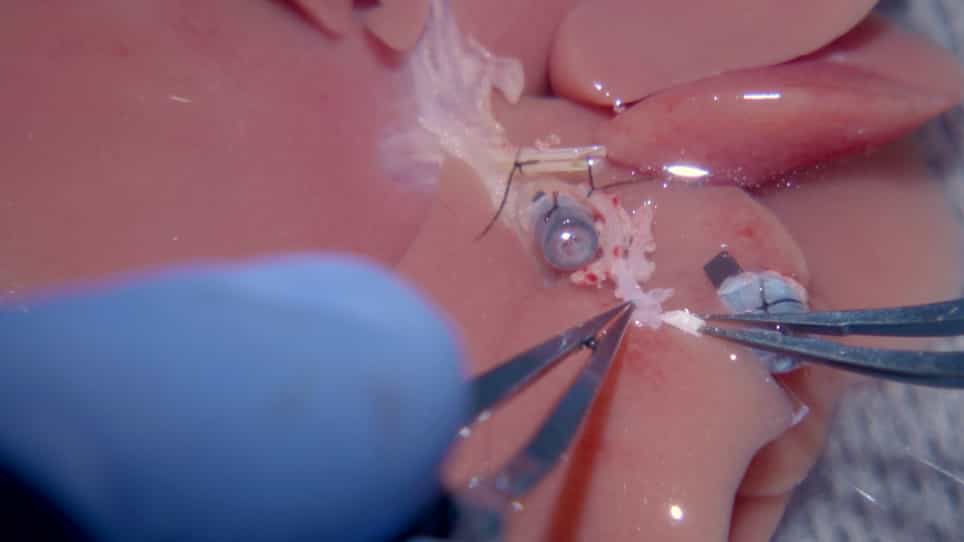
Reduced Complications after Arterial Reconnection in a Rat Model of Orthotopic Liver Transplantation
Published on: November 7, 2020
Switching to sirolimus in renal transplant recipients with hepatitis C virus: a safe option
R Gallego1, F Henriquez, E Oliva
1Nephrology Service, Hospital Universitario of Gran Canaria Dr Negrin, Las Palmas de Gran Canaria, Spain. rgalsam@gobiernodecanarias.org

Introduction:
The presence of hepatitis C virus (HCV) in renal transplant recipients is an independent risk factor for death and graft failure. Chronic allograft nephropathy (CAN) favored by the use of calcineurin inhibitors (CNI) is one of the main causes of graft loss, whereas sirolimus (SRL) has proven to maintain better graft function with lower rates of CAN.
Objectives And Methods:
We developed a protocol to evaluate the safety of SRL in transplant recipients with respect to HCV. We studied 5 patients (3 men) of mean age 52 +/- 9.2 years with HCV who had not received antiviral treatment. The viral genotypes were 1b in 4 cases and 2a/2c in 1 case. Basic immunosuppression was mycophenolate mofetil (MMF) and corticosteroids in all patients, cyclosporine (CsA) in 4 cases, and tacrolimus (Tac) in 1 case. Before the switch, a renal biopsy was performed and viral replication and cryoglobulins determined.
Results:
Biopsy provided a diagnosis of CAN in 1 case, CNI toxicity-associated CAN in 2 cases, CNI toxicity in 1 case, and no renal damage in the remaining case. We observed a nonsignificant decrease in the number (log) of viral copies with a stabilization of renal function but with a slight to moderate increase in proteinuria.
Conclusions:
The switch seemed to be safe with no increase in viral copies. Graft renal function remained stable with increased proteinuria that must be supervised, even though it did not reach statistical significance.
Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:16
Kidney Transplant III: Nursing Management