Related Experiment Video
Updated: Jun 20, 2026
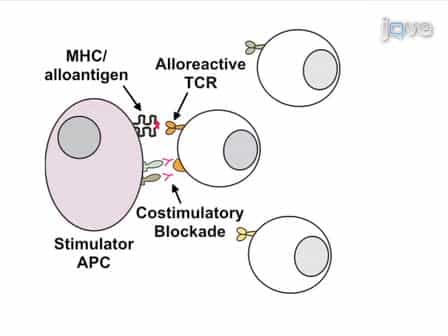
Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
Comparison of thrombotic microangiopathy after allogeneic hematopoietic cell transplantation with high-dose or
1Division of Hematology, Department of Medicine, University of Liège and CHU of Liège, Liège, Belgium.

The role of conditioning intensity on occurrence of thrombotic microangiopathy (TMA) after allogeneic hematopoietic cell transplantation (HCT) has remained unclear thus far. Here, we retrospectively compared the incidence of TMA in patients given allogeneic hematopoietic stem cells after either nonmyeloablative (n=176) or high-dose (n=111) conditioning. The 1-year cumulative incidence of TMA was 13% in nonmyeloablative recipients versus 15% in high-dose conditioning recipients (P=0.5). In multivariate Cox analysis, occurrence of grade 3-4 acute graft-versus-host disease (GVHD) (hazard ratio (HR)=2.3, P<0.001), older age (HR=1.01, P=0.045), and unrelated donors (HR=1.6, P=0.01) were each associated with a higher risk of TMA, whereas nonmyeloablative conditioning was associated with a lower risk of TMA (HR=0.6, P=0.01). We conclude that acute GVHD, age, donor type, and conditioning intensity might have a role in the physiopathology of TMA after allogeneic HCT.
The role of conditioning intensity on occurrence of thrombotic microangiopathy (TMA) after allogeneic hematopoietic cell transplantation (HCT) has remained unclear thus far. Here, we retrospectively compared the incidence of TMA in patients given allogeneic hematopoietic stem cells after either nonmyeloablative (n=176) or high-dose (n=111) conditioning. The 1-year cumulative incidence of TMA was 13% in nonmyeloablative recipients versus 15% in high-dose conditioning recipients (P=0.5). In multivariate Cox analysis, occurrence of grade 3-4 acute graft-versus-host disease (GVHD) (hazard ratio (HR)=2.3, P<0.001), older age (HR=1.01, P=0.045), and unrelated donors (HR=1.6, P=0.01) were each associated with a higher risk of TMA, whereas nonmyeloablative conditioning was associated with a lower risk of TMA (HR=0.6, P=0.01). We conclude that acute GVHD, age, donor type, and conditioning intensity might have a role in the physiopathology of TMA after allogeneic HCT.


