Related Experiment Video
Updated: Jun 20, 2026

Visualization of Chondrocyte Intercalation and Directional Proliferation via Zebrabow Clonal Cell Analysis in the Embryonic Meckel’s Cartilage
Published on: October 21, 2015
Chondroblastoma of bone in a pediatric population
Frédéric Sailhan1, Franck Chotel, Roger Parot
1Department of Orthopaedic Surgery, Hôpital Cochin, Paris, France. fred.sailhan@wanadoo.fr

Background:
Chondroblastoma is a rare benign bone lesion that occurs in young patients and has a high rate of recurrence. The purpose of the present study was to report on eighty-seven cases of chondroblastoma in children and to identify the possible factors that increase the risk of recurrence.
Methods:
We retrospectively reviewed eighty-seven cases of chondroblastoma in patients with open physes at the time of diagnosis and treatment. Historical data, complete imaging data, histological findings, and surgical charts were analyzed. Multiple logistic regression was used to identify predictors of recurrence.
Results:
The series included fifty-three boys and thirty-four girls with a mean age of 12.5 years. Lesions were located in the epiphysis in 68% of the patients, especially in the proximal part of the tibia (twenty-four patients) and the proximal part of the femur (twenty-three patients). Pain was the presenting symptom in 84% of the patients. The treatment consisted of intralesional curettage with autogenous bone-grafting in 63% of the patients. The functional outcome at an average of 62.5 months of follow-up was good for 68.5% of the patients. At a minimum of twenty-four months of follow-up, 32% of the lesions had recurred. Sex, radiographic aggressiveness, an aneurysmal bone-cyst component on histological analysis, and the method of surgical treatment had no significant influence on recurrence. Epiphyseal chondroblastomas were associated with a higher risk of recurrence when compared with metaphyseal, apophyseal, and epiphyseal-metaphyseal lesions (p = 0.004).
Conclusions:
Chondroblastoma in growing children is most frequently located in the proximal part of the tibia and the proximal femoral epiphysis. The recurrence rate is high, particularly for strictly epiphyseal lesions. Proximal femoral lesions and tarsal lesions are associated with a poorer outcome.
Related Concept Videos
 01:24
Bone Formation by Endochondral Ossification
 01:27
Growth of Cartilage and Bone Tissue
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
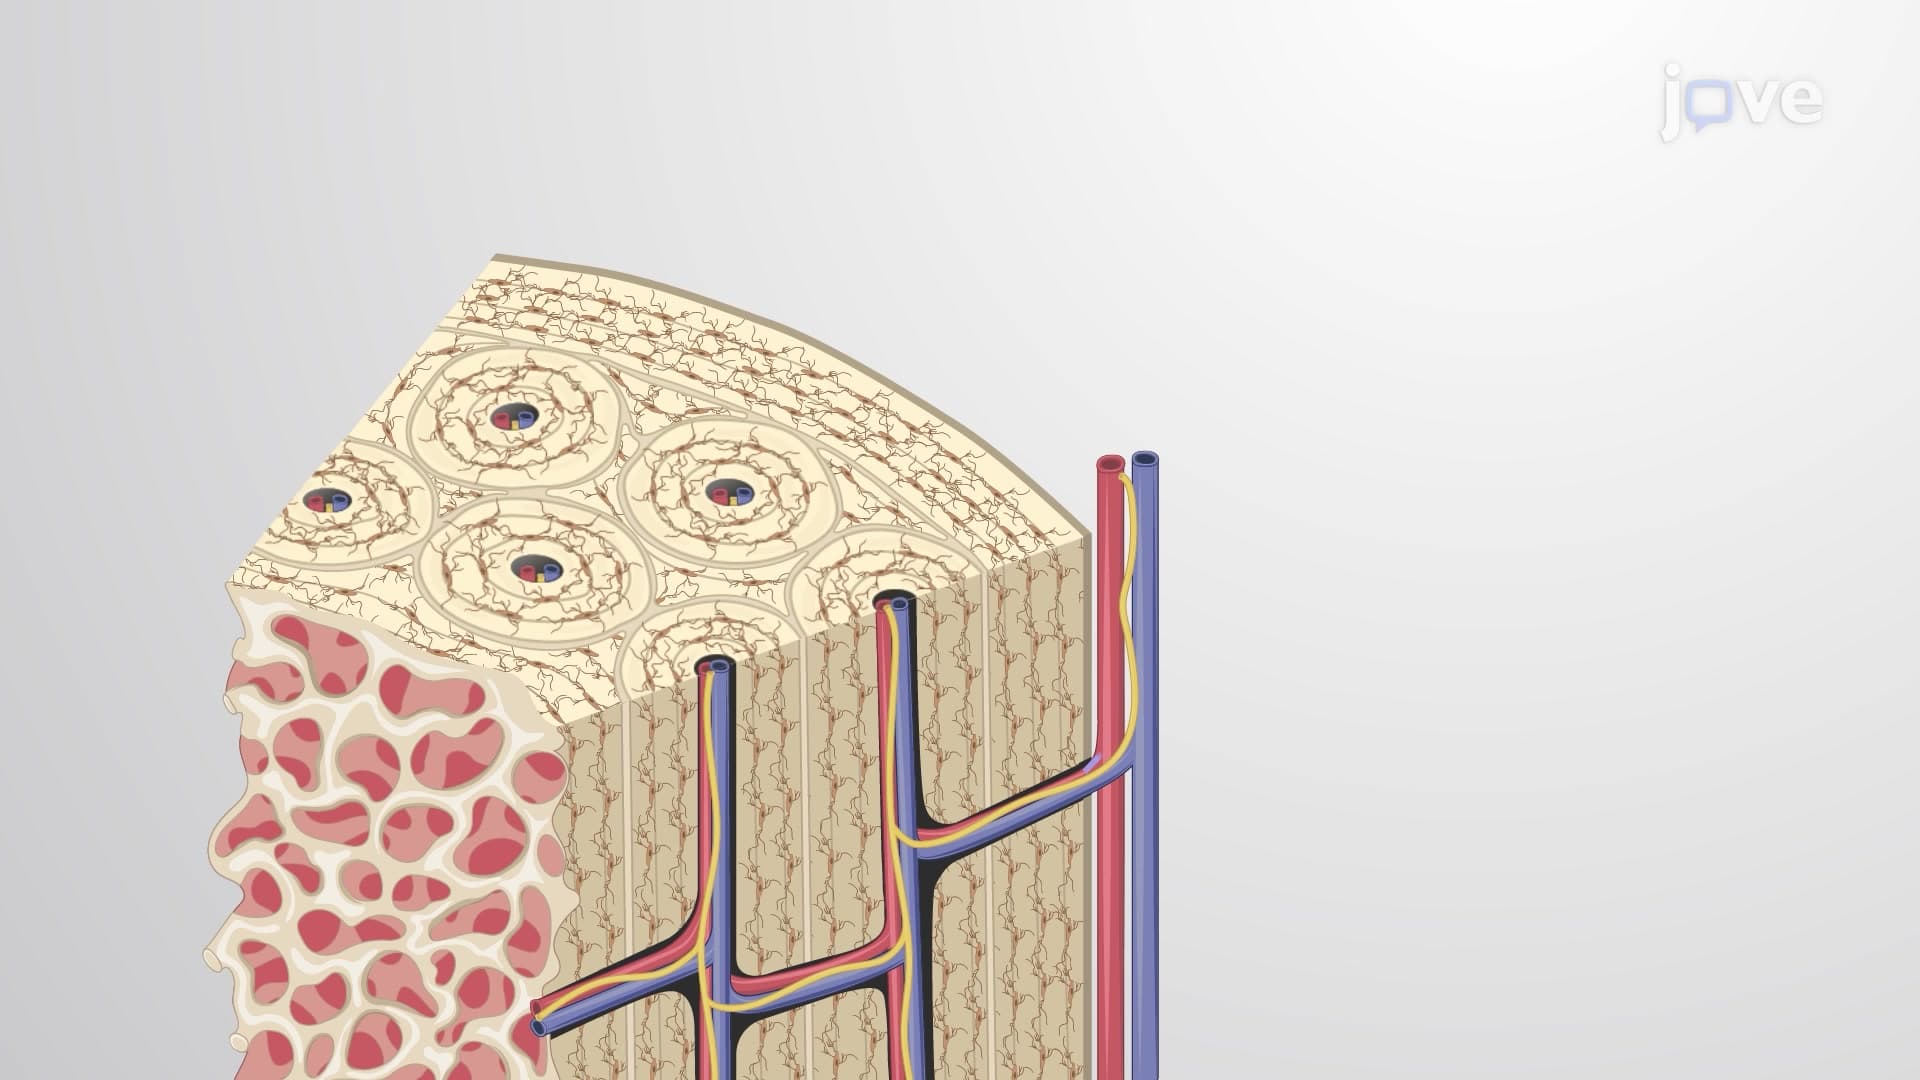
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:07
Development of the Limb Synovial Joints
The mesenchymal stem cells differentiate into chondrocytes that form the hyaline cartilage, and later the cartilaginous model of the bone. This model further transforms into a bone. This process is known as endochondral ossification.
During development, the limbs...