Related Experiment Video
Updated: Jun 20, 2026
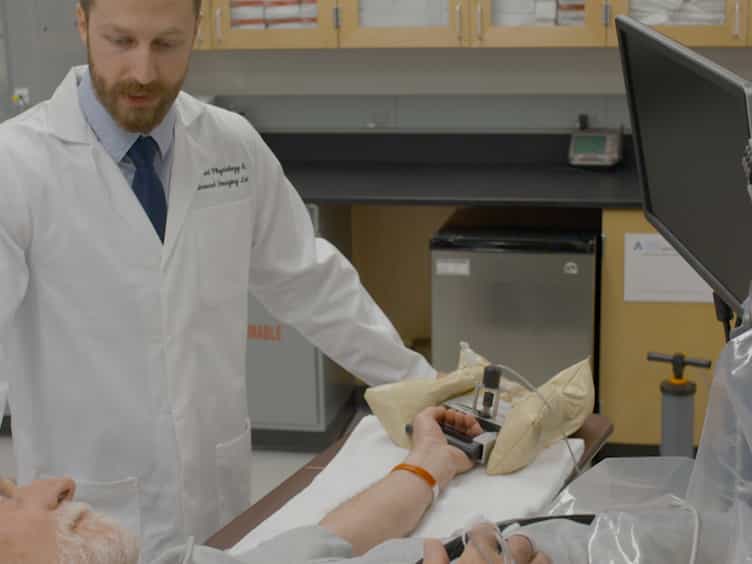

Skeletal Muscle Neurovascular Coupling, Oxidative Capacity, and Microvascular Function with 'One Stop Shop' Near-infrared Spectroscopy
Published on: February 20, 2018
NOS inhibition blunts and delays the compensatory dilation in hypoperfused contracting human muscles
Darren P Casey1, Michael J Joyner
1Department of Anesthesiology, Mayo Clinic, Rochester, Minnesota 55905, USA. casey.darren@mayo.edu

Abstract:
We previously demonstrated that skeletal muscle blood flow is restored in the exercising forearm during experimental hypoperfusion via local dilator and/or myogenic mechanisms. This study examined the role of nitric oxide (NO) in the restoration of blood flow to the active muscles during hypoperfusion. Eleven healthy subjects (10 men/1 woman; 25 +/- 1 yr of age) performed rhythmic forearm exercise (10% and 20% of maximum) while hypoperfusion was evoked by balloon inflation in the brachial artery above the elbow. Each trial included baseline, exercise, exercise with inflation, and exercise after deflation (3 min each). Forearm blood flow (FBF; ultrasound) and local (brachial artery catheter pressure, BAP) and systemic arterial pressure [mean arterial pressure (MAP); Finometer] were measured. The exercise bouts were repeated during N(G)-monomethyl-L-arginine (L-NMMA) infusion (NO synthase inhibition). Forearm vascular conductance (FVC; ml x min(-1) x 100 mmHg(-1)) was calculated from BF (ml/min) and BAP (mmHg). FBF and FVC fell acutely with balloon inflation during all trials (P < 0.01). Recovery of FBF and FVC [(inflation - nadir)/(steady-state exercise - nadir)] with L-NMMA administration was reduced during 20% exercise (FBF = 77 +/- 7% vs. 88 +/- 8%; FVC = 71 +/- 8% vs. 90 +/- 9%; P < 0.01) but not 10% exercise (FBF = 83 +/- 4% vs. 81 +/- 5%, P = 0.37; FVC = 75 +/- 10% vs. 76 +/- 7%; P = 0.44) compared with the respective control trial. The time to steady-state vasodilator response was substantially longer during the l-NMMA trials (10% = 74 +/- 4 s vs. 61 +/- 6 s; 20% = 53 +/- 4 s vs. 41 +/- 4 s; P < 0.05). Thus the magnitude and timing of the NO contribution to compensatory dilation during forearm exercise with hypoperfusion was dependent on exercise intensity. These observations suggest that NO is released by contracting muscles or that a portion of the dilation caused by ischemic metabolites is NO dependent.


Related Concept Videos
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:17
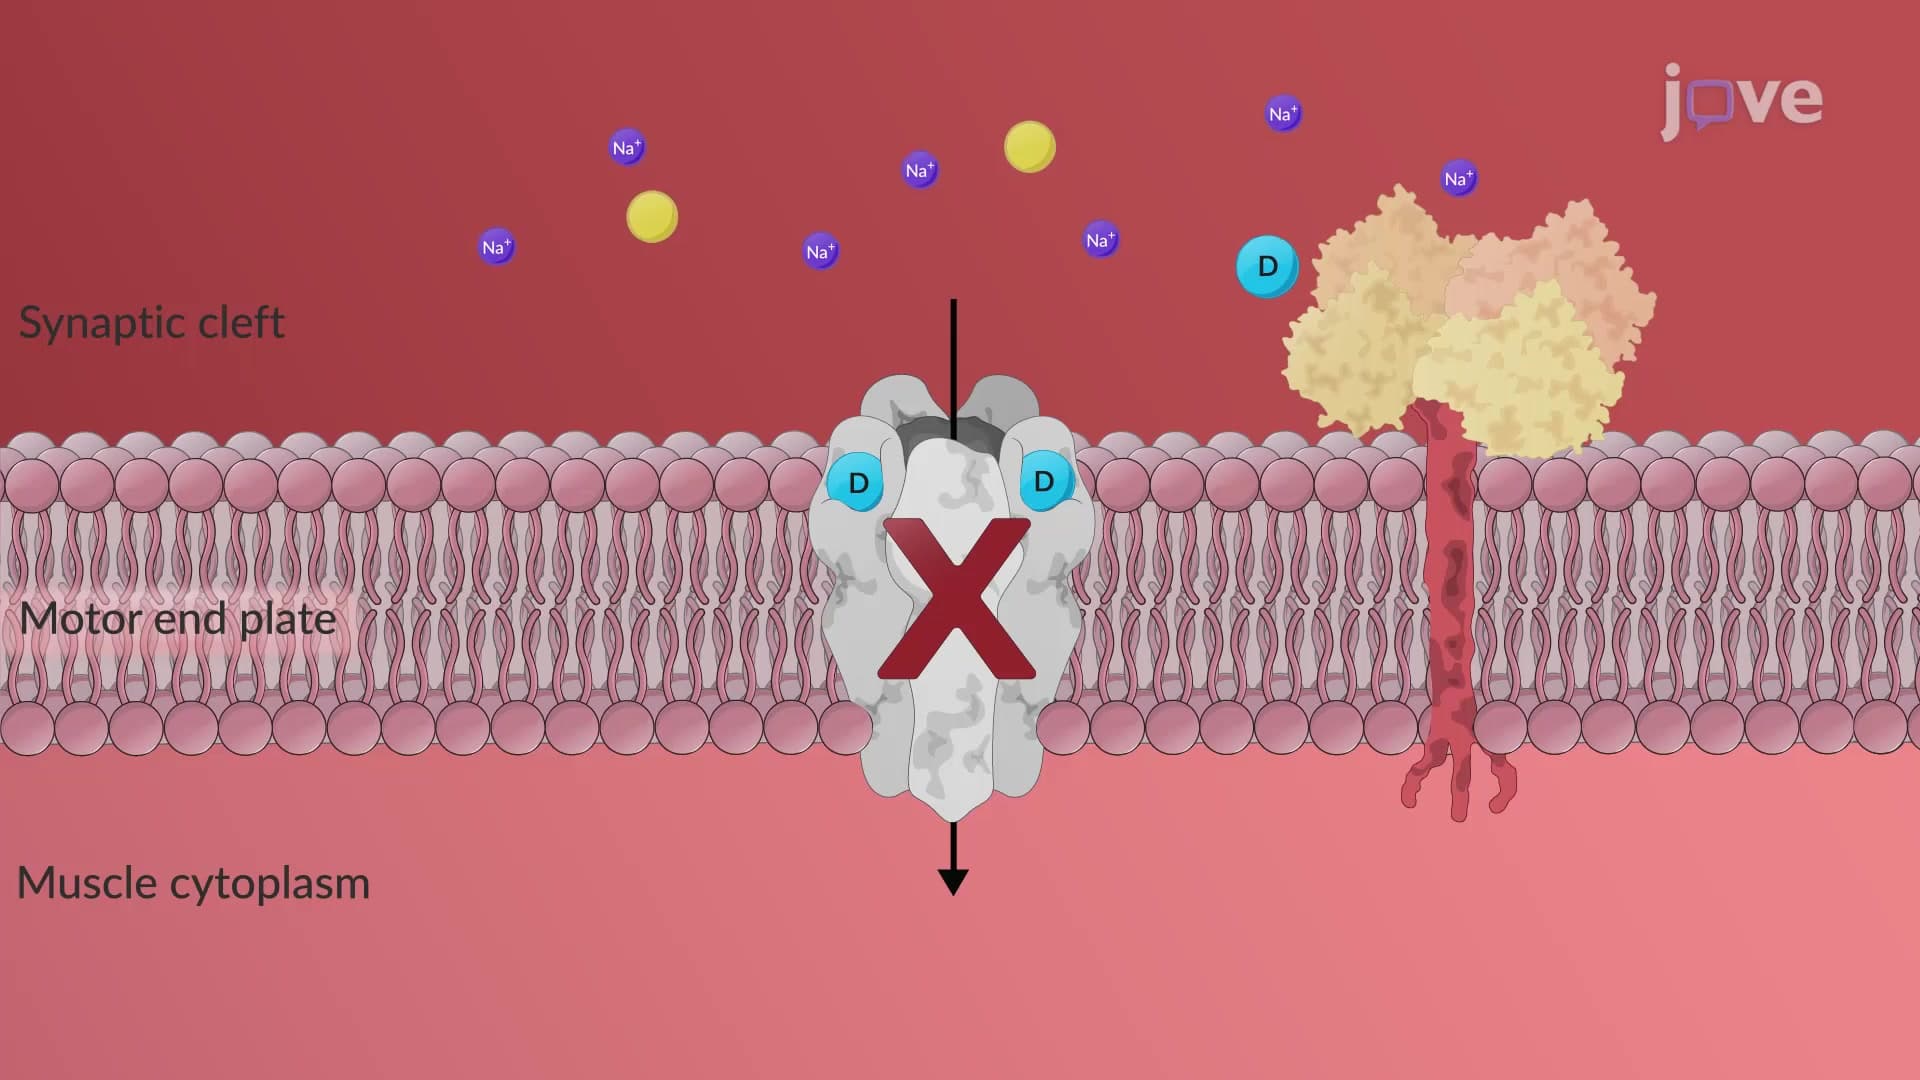
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:28
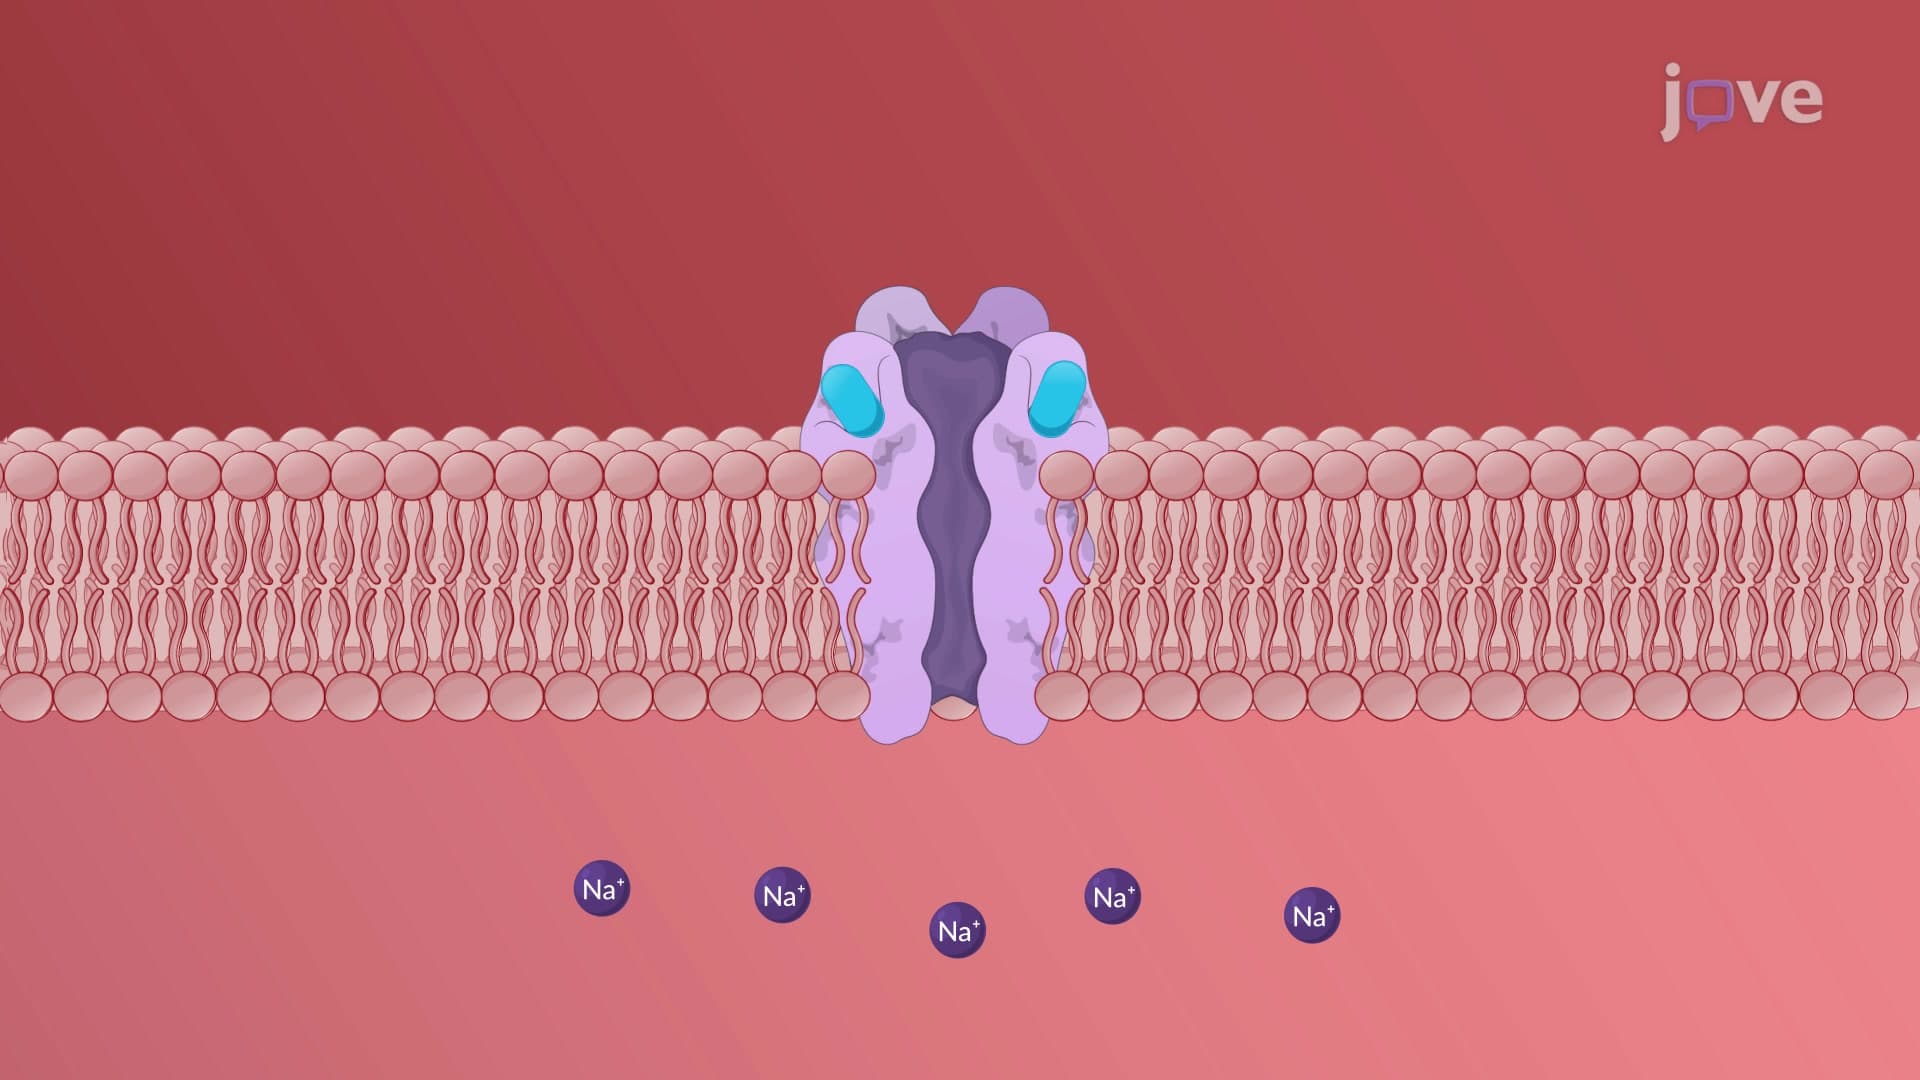
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:28
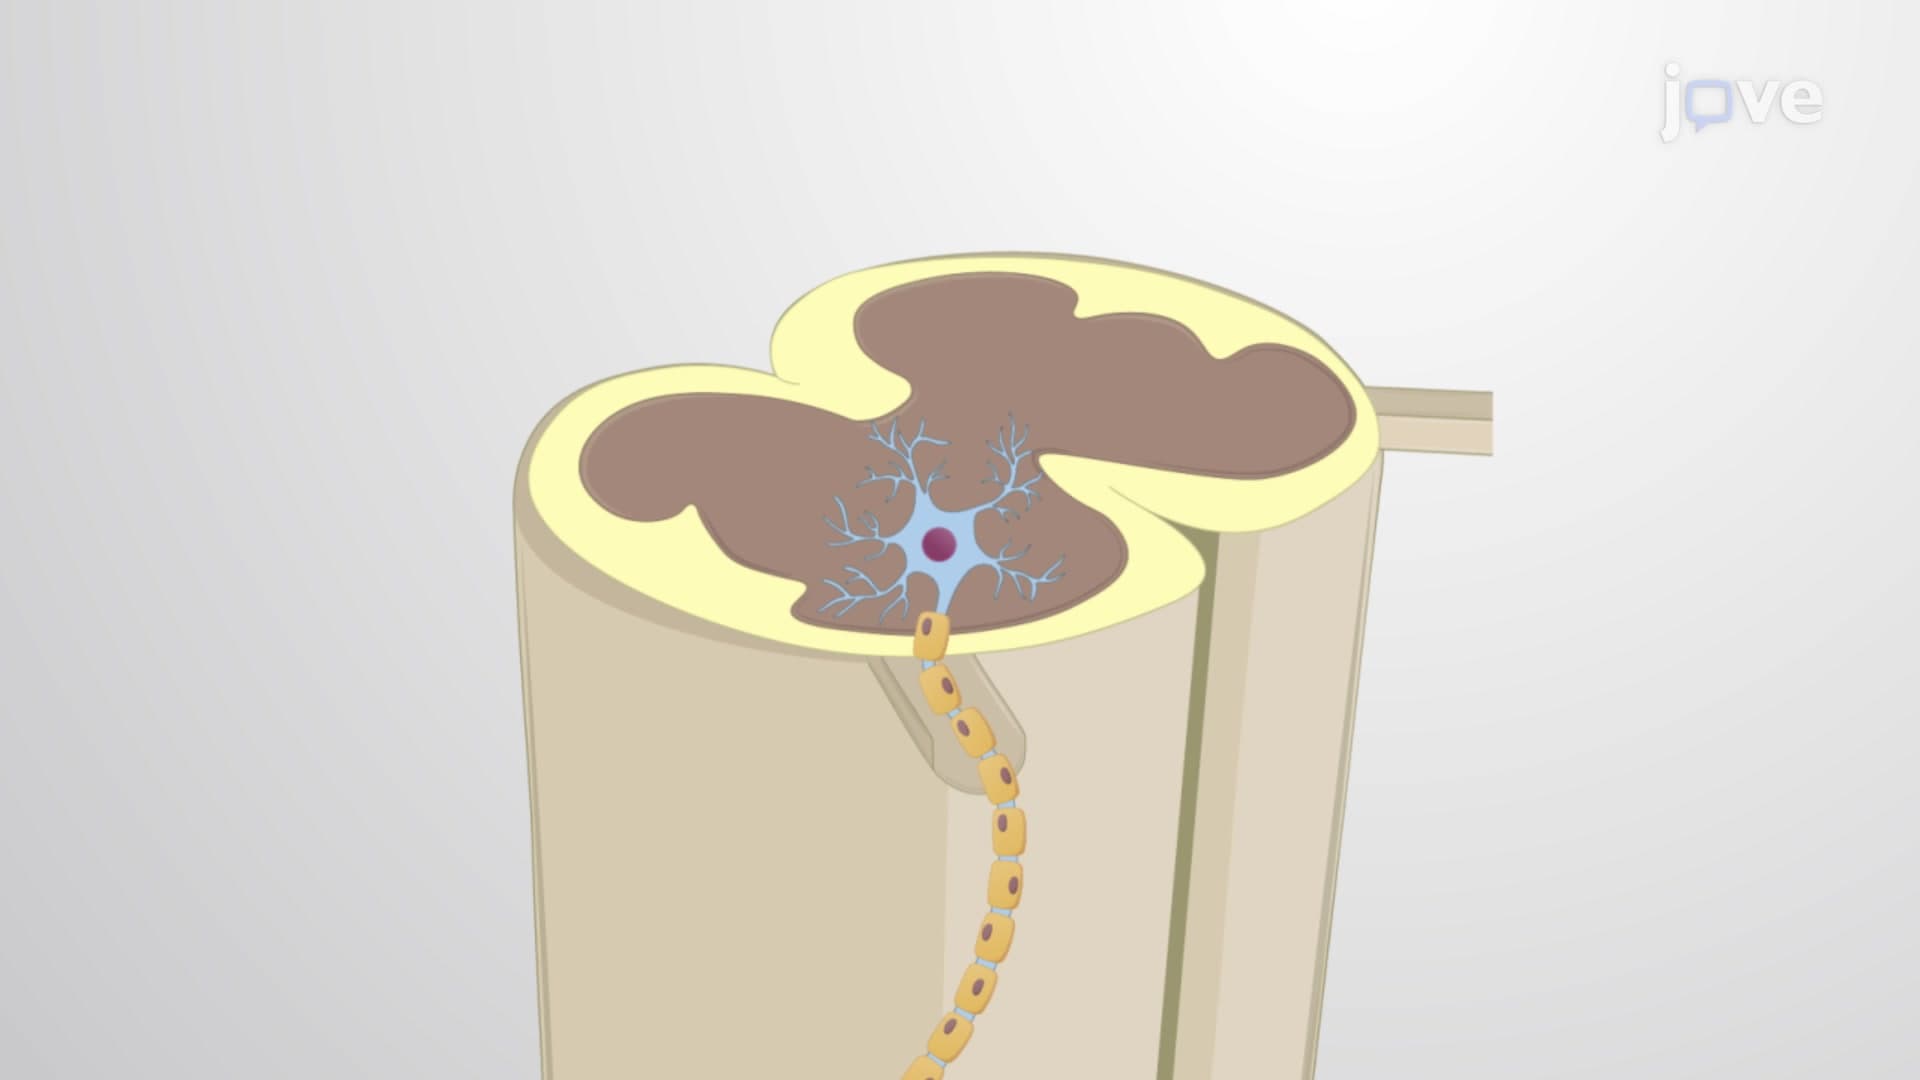
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...