Related Experiment Video
Updated: Jun 20, 2026

Ultrasonographic Evaluation of Salivary Glands for Sjogren's Syndrome: Diagnostic and Monitoring Insights
Published on: October 13, 2023
Hematologic manifestations and predictors of lymphoma development in primary Sjögren syndrome: clinical and
Evangelia Baimpa1, Issa J Dahabreh, Michael Voulgarelis
1From Department of Pathophysiology, Medical School of Athens, National University of Athens, Athens, Greece.

Abstract:
The diverse hematologic manifestations of primary Sjögren syndrome (pSS) have not been systematically investigated, and their prognostic relevance remains unclear. We conducted a retrospective study of 536 consecutive patients followed in our institution to assess the prevalence of hematologic abnormalities and their associations with various disease manifestations in pSS. We also aimed to identify risk factors for the development of non-Hodgkin lymphoma (NHL) overall and by subtype. Anemia of chronic disease and hypergammaglobulinemia were the most prevalent hematologic manifestations encountered at diagnosis and during the course of pSS. Univariate analysis between cytopenias and glandular manifestations revealed a statistically significant correlation between lymphocytopenia and parotid gland enlargement (p = 0.002), as well as between neutropenia and xerostomia (p = 0.019). Anemia, lymphocytopenia, thrombocytopenia, hypergammaglobulinemia, the presence of monoclonal serum proteins, and cryoglobulinemia correlated significantly with the presence of extraglandular symptoms such as palpable purpura, lymphadenopathy, and splenomegaly. Lymphoma was diagnosed in 7.5% (95% confidence interval [CI], 5.4%-10%) of patients. Marginal zone B-cell lymphomas (MZBCLs) were the predominant histologic type (65%; 95% CI, 48.3%-79.4%), while diffuse large B-cell lymphomas (DLBCLs) accounted for 17.5% (95% CI, 7.3%-32.8%) of all cases. The development of NHL in patients with pSS could be predicted by the presence of simple clinical and laboratory factors at diagnosis: neutropenia (p = 0.041), cryoglobulinemia (p = 0.008), splenomegaly (p = 0.006), lymphadenopathy (p = 0.021), and low C4 levels (p = 0.009). Patients carrying any of these factors had a more than 5-fold increased risk of NHL compared to patients with no risk factors at all. The above set of disease characteristics could predict subsequent development of MZBCL; the presence of lymphocytopenia (p = 0.044) at diagnosis served as a risk factor for the development of a non-MZBCL, most commonly DLBCL. Anemia of chronic disease and hypergammaglobulinemia are common hematologic manifestations at diagnosis and during the course of pSS. Neutropenia and cryoglobulinemia at diagnosis are significantly associated with an increased risk of lymphoma development.

Related Concept Videos
 01:16
Primary Lymphoid Organs
The red bone marrow is a soft, spongy tissue nestled in the interior of long bones such as the humerus and femur. It is the site...
 01:15
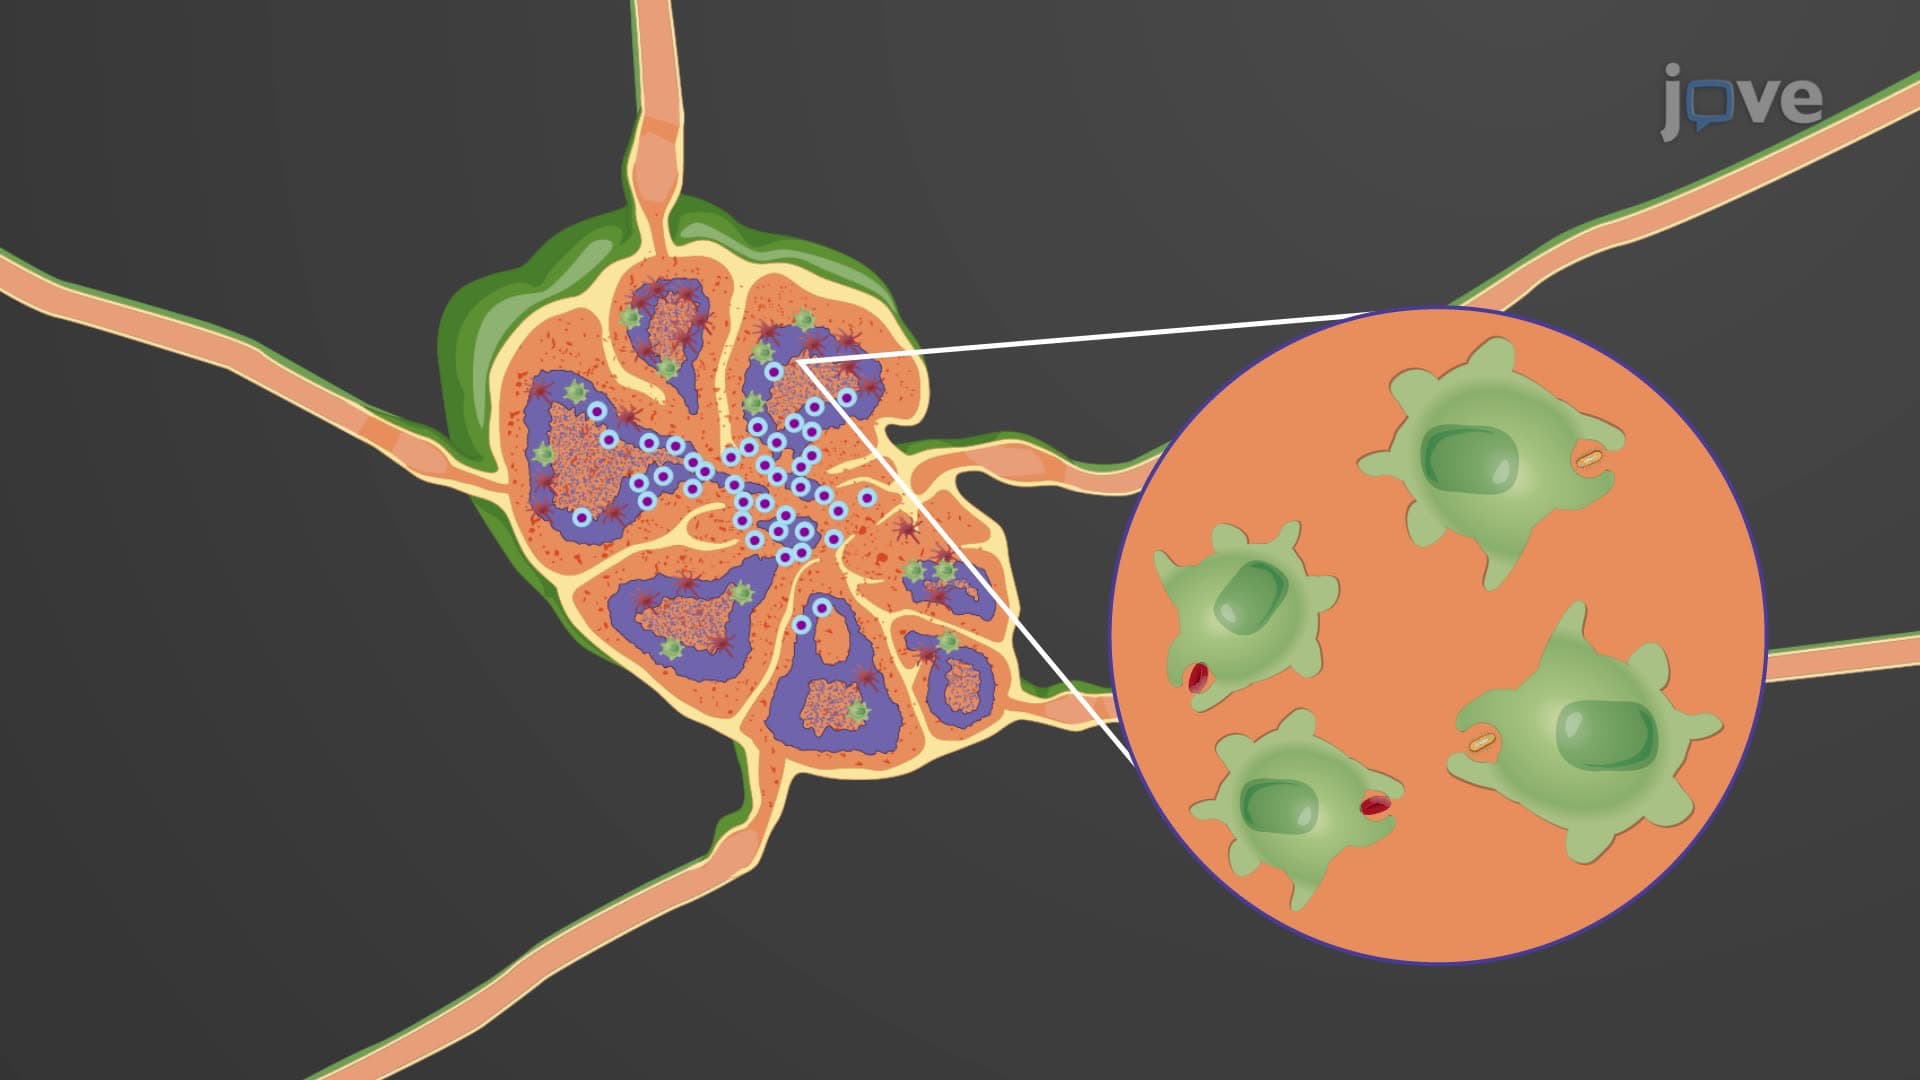
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
 01:24
Graves Disease II: Pathophysiology
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:18
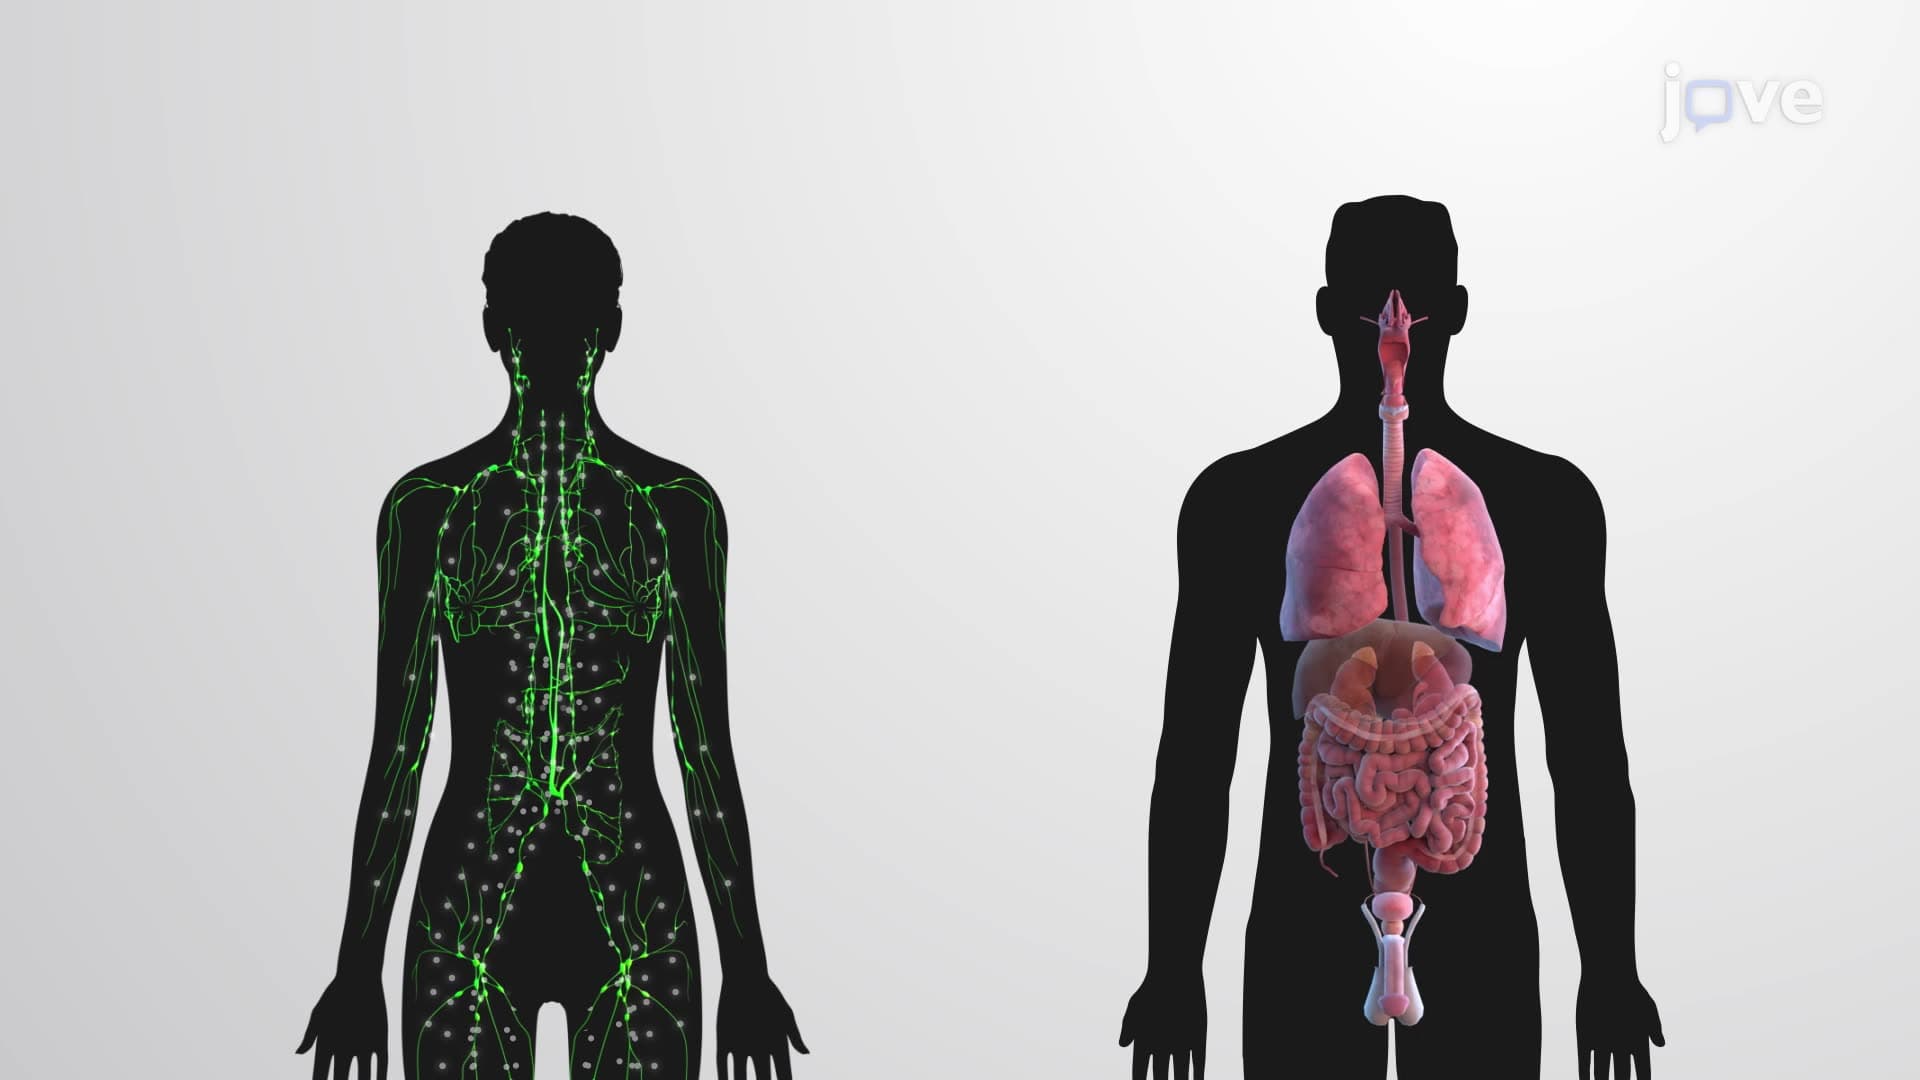
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...