Related Experiment Video
Updated: Jun 20, 2026
Disruption of the Mouse Blood-Brain Barrier by Small Extracellular Vesicles from Hypoxic Human Placentas
Published on: January 26, 2024
Prolactin fragmentation by trophoblastic matrix metalloproteinases as a possible contributor to peripartum
Anne Q Reuwer1, Paul J H M Reuwer, Joris A van der Post
1Department of Vascular Medicine of the Academic Medical Center Amsterdam, The Netherlands. A.Q.Reuwer@amc.uva.nl

Although peripartum cardiomyopathy (PPCM) is a rare disease, it has very serious consequences for both mother and child. No single cause has been held responsible for the pathogenesis. Recent studies have indicated that increased proteolytic cathepsin D activity in cardiomyocytes results in16kDa prolactin fragments with anti-angiogenic and apoptotic properties, which may contribute to the development of PPCM. In support of these findings, lowering full-length prolactin production by bromocriptine therapy has been reported to prevent impairment of cardiac function. PPCM is associated with an increased co-existence of pre-eclampsia, however, a causal relationship has been disputed. We hypothesize that the pathophysiology of PPCM and pre-eclampsia share the same molecular pathway: increased activity of trophoblastic matrix metalloproteinases at the feto-maternal interface may aggravate proteolysis of full-length prolactin, and subsequently the formed 16kDa prolactin fragments may contribute to deterioration of PPCM and pre-eclampsia. Therefore, we argue that it may be worthwhile to explore wether prolactin inhibition is not only beneficial for PPCM patients, but also for the much more prevalent pre-eclamptic women.
Although peripartum cardiomyopathy (PPCM) is a rare disease, it has very serious consequences for both mother and child. No single cause has been held responsible for the pathogenesis. Recent studies have indicated that increased proteolytic cathepsin D activity in cardiomyocytes results in16kDa prolactin fragments with anti-angiogenic and apoptotic properties, which may contribute to the development of PPCM. In support of these findings, lowering full-length prolactin production by bromocriptine therapy has been reported to prevent impairment of cardiac function. PPCM is associated with an increased co-existence of pre-eclampsia, however, a causal relationship has been disputed. We hypothesize that the pathophysiology of PPCM and pre-eclampsia share the same molecular pathway: increased activity of trophoblastic matrix metalloproteinases at the feto-maternal interface may aggravate proteolysis of full-length prolactin, and subsequently the formed 16kDa prolactin fragments may contribute to deterioration of PPCM and pre-eclampsia. Therefore, we argue that it may be worthwhile to explore wether prolactin inhibition is not only beneficial for PPCM patients, but also for the much more prevalent pre-eclamptic women.
More Related Videos
 12:02
Human Primary Trophoblast Cell Culture Model to Study the Protective Effects of Melatonin Against Hypoxia/reoxygenation-induced Disruption
Published on: July 30, 2016
 05:30
Trophoblast Cell Recovery from Angiogenesis-Tube Formation Assay for Differentiation Marker Expression Analysis
Published on: November 8, 2024
Related Concept Videos
 01:23
Role of Matrix Metalloproteases in Degradation of ECM
A...
 01:07
Teratogenicity
 01:27
Mitral Valve Prolapse I: Introduction
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:19
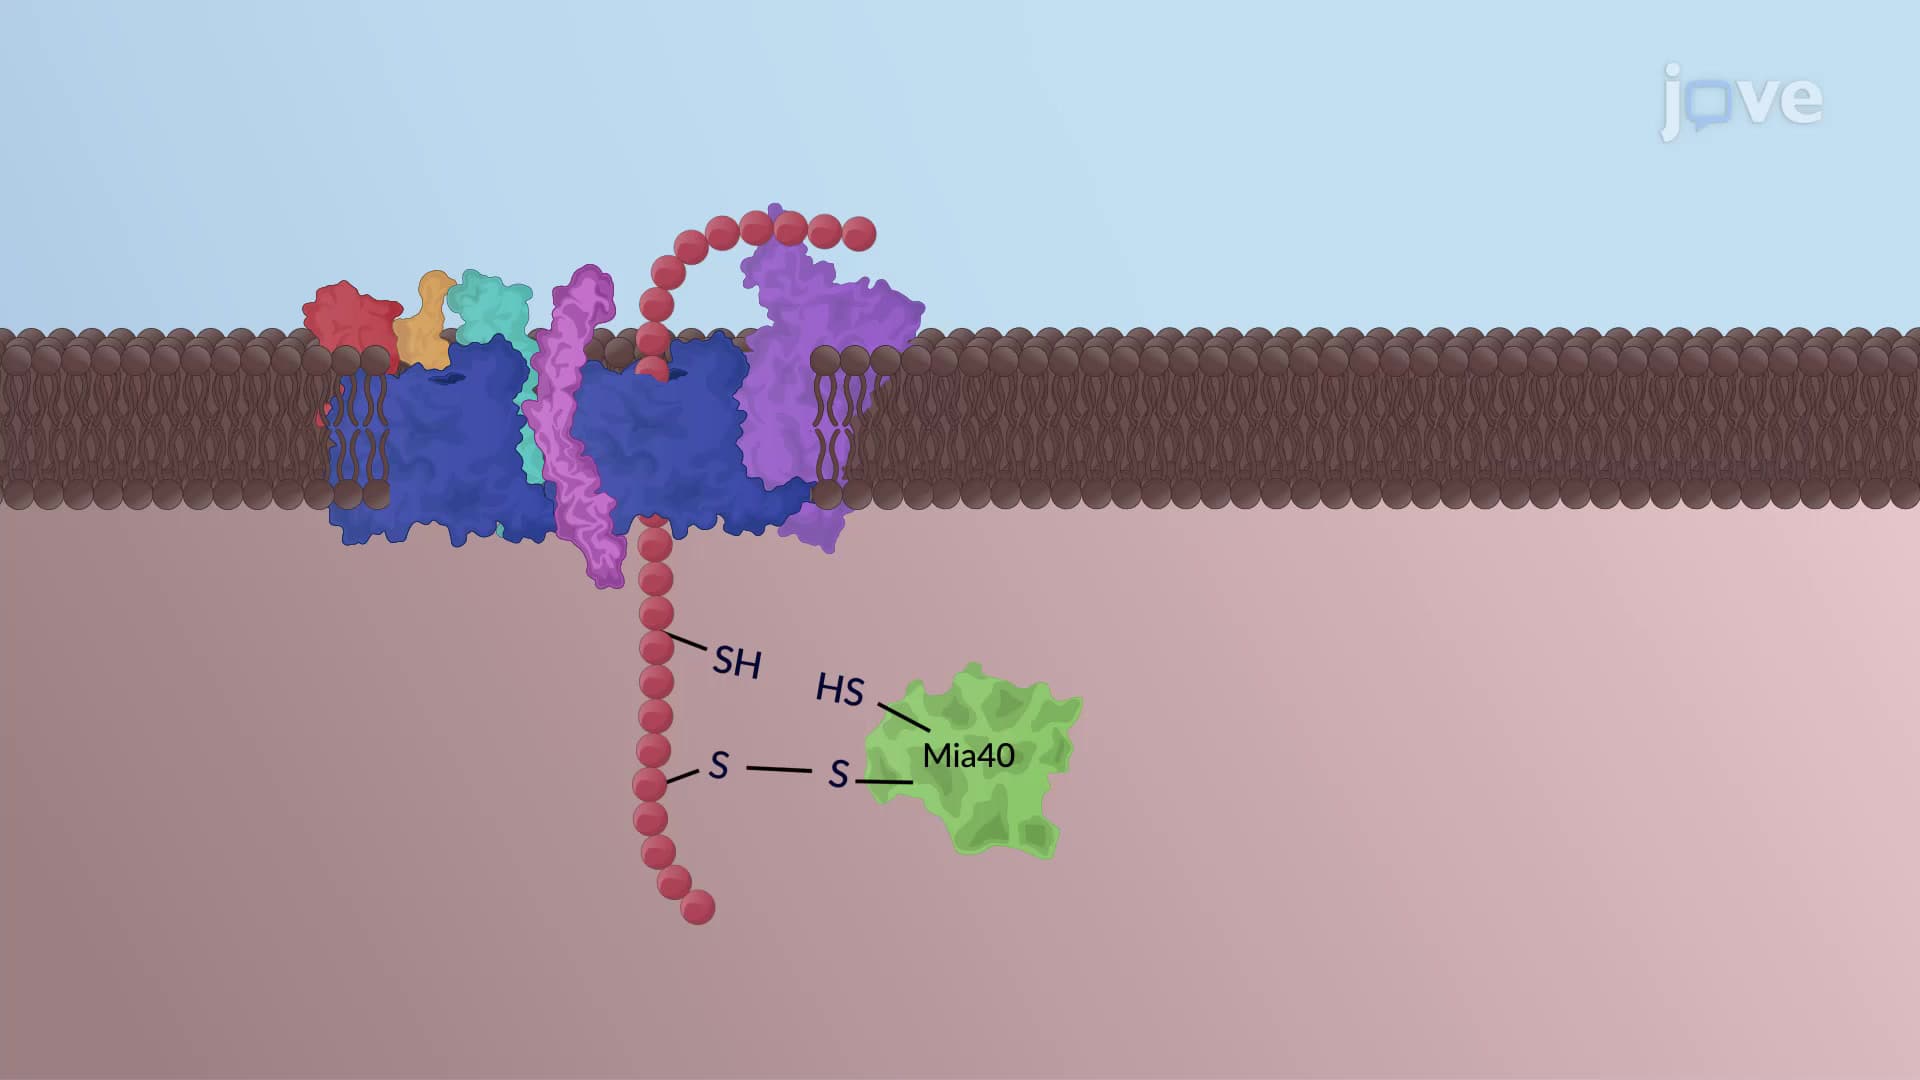
Translocation of Proteins into the Mitochondria
Sorting of outer membrane proteins:
Mitochondrial outer membrane proteins are of two types: the transmembrane, beta-barrel porins, and the membrane-anchored, alpha-helical proteins. Beta-barrel porin precursors are translocated by the TOM complex and inserted into the outer mitochondrial membrane by the SAM complex. In contrast,...
 01:27
Ovarian Cycle