Related Experiment Video
Updated: Jun 20, 2026

Intracellular Staining and Flow Cytometry to Identify Lymphocyte Subsets within Murine Aorta, Kidney and Lymph Nodes in a Model of Hypertension
Published on: January 28, 2017
Angiotensin type 1 receptor expression and interleukin-8 production in polymorphonuclear leukocytes of patients with
Franca Marino1, Luigina Guasti, Matteo Tozzi
1Department of Clinical Medicine, Section of Experimental and Clinical Pharmacology, University of Insubria, Varese VA, Italy. franca.marino@uninsubria.it

Abstract:
We investigated angiotensin type 1 receptor (AT1R) expression and interleukin-8 (IL-8) productions in polymorphonuclear leukocytes obtained from patients with peripheral arterial disease (PAD) undergoing femoral endarterectomy. Subjects at high cardiovascular risk (high-risk subjects, HRS) and healthy controls (HC) were also enrolled. To this end, patients with PAD were studied 1 month before surgery, at the time of surgery, and 3 and 6 months after surgery. Polymorphonuclear leukocytes were obtained from venous blood and evaluated for AT1R expression at messenger RNA (mRNA) and protein level and IL-8 production (by means of enzyme-linked immunosorbent assay). At baseline, AT1R membrane expression was similar in cells from patients with PAD, HRS, and HC, whereas AT1R mRNA was similar in patients with PAD and HC and higher in HRS. During the follow-up period, AT1R expression progressively decreased both on the cell membrane and at the mRNA level. Both resting and stimulated production of IL-8 was lower in patients with PAD in comparison to HC and HRS and did not change during the follow up period. In PAD patients, femoral endarterectomy is associated with reduction of AT1R expression however with no apparent effect on IL-8 production. The relevance of such effects for cardiovascular protection deserves consideration.

Related Concept Videos
 01:30
Antihypertensive Drugs: Angiotensin II Receptor Blockers
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:30
Peripheral Artery Disease I: Introduction
 01:25
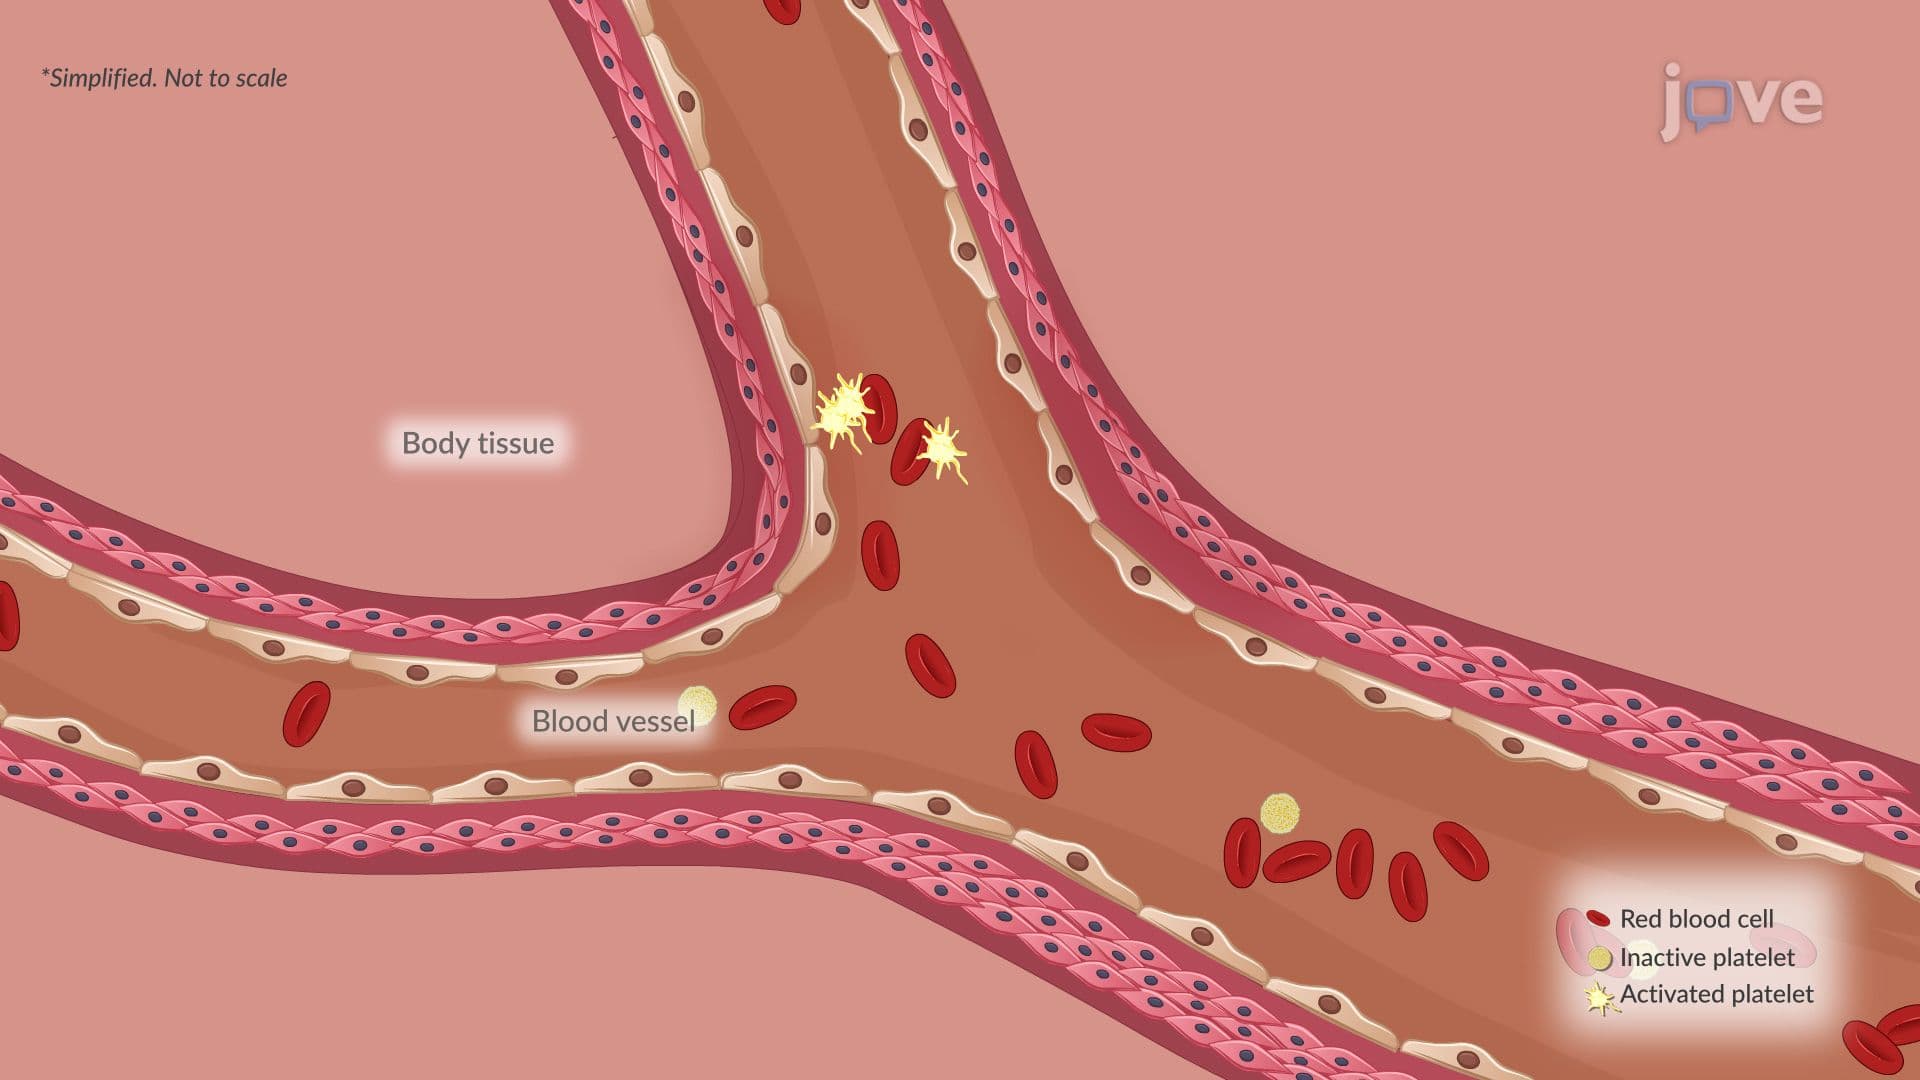
Acute Inflammation III: Local and Systemic Effects
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:24
T Cell Types and Functions
Th1 cells stimulate dendritic cells to express necessary co-stimulatory molecules on their surfaces for...