Related Experiment Video
Updated: Jun 20, 2026
The 4-vessel Sampling Approach to Integrative Studies of Human Placental Physiology In Vivo
Published on: August 2, 2017
Bartter's syndrome in pregnancy: review of potassium homeostasis in gestation
Ashar Luqman1, Asif Kazmi, Barry M Wall
1University of Tennessee Health Science Center, Memphis, Tennessee, USA.

A 26-year-old G3P2 Hispanic female presented with acute urinary retention and profound hypokalemia (serum potassium 1.6 mEq/L) during her 13th week of pregnancy. Placement of an indwelling bladder catheter resulted in immediate urine output of 1700 mL. Potassium was administered aggressively and urinary retention resolved. She reported the use of herbal products containing licorice and corn silk tea (zea maize extract). She was taking no medication other than prenatal vitamins and had no known prior medical problems. Despite discontinuance of the herbal supplement and tea and aggressive oral potassium replacement, severe asymptomatic hypokalemia persisted. Twenty-four-hour urine studies and blood chemistry determinations, subsequently, were consistent with Bartter's syndrome. At the time of hospital discharge, she was receiving 480 mEq of oral potassium daily. Potassium-sparing diuretics were not prescribed, because successful pregnancy outcomes have been reported in patients with Bartter's syndrome and Gitelman syndrome without normalization of potassium levels. Hypokalemia (2.5-3.0 mEq/L) persisted throughout an otherwise uncomplicated pregnancy with delivery of a healthy child at 35 weeks of gestation.
A 26-year-old G3P2 Hispanic female presented with acute urinary retention and profound hypokalemia (serum potassium 1.6 mEq/L) during her 13th week of pregnancy. Placement of an indwelling bladder catheter resulted in immediate urine output of 1700 mL. Potassium was administered aggressively and urinary retention resolved. She reported the use of herbal products containing licorice and corn silk tea (zea maize extract). She was taking no medication other than prenatal vitamins and had no known prior medical problems. Despite discontinuance of the herbal supplement and tea and aggressive oral potassium replacement, severe asymptomatic hypokalemia persisted. Twenty-four-hour urine studies and blood chemistry determinations, subsequently, were consistent with Bartter's syndrome. At the time of hospital discharge, she was receiving 480 mEq of oral potassium daily. Potassium-sparing diuretics were not prescribed, because successful pregnancy outcomes have been reported in patients with Bartter's syndrome and Gitelman syndrome without normalization of potassium levels. Hypokalemia (2.5-3.0 mEq/L) persisted throughout an otherwise uncomplicated pregnancy with delivery of a healthy child at 35 weeks of gestation.

Related Concept Videos
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:33
Hormonal Regulation
 01:26
Regulation of Sodium and Potassium
Sodium Regulation
Sodium ions make up approximately 90% of extracellular cations, with a normal blood plasma concentration of 136–148 mEq/L. A decrease in blood volume and pressure triggers the release of renin from granular cells in the juxtaglomerular complex (JGC), primarily in...
 01:22
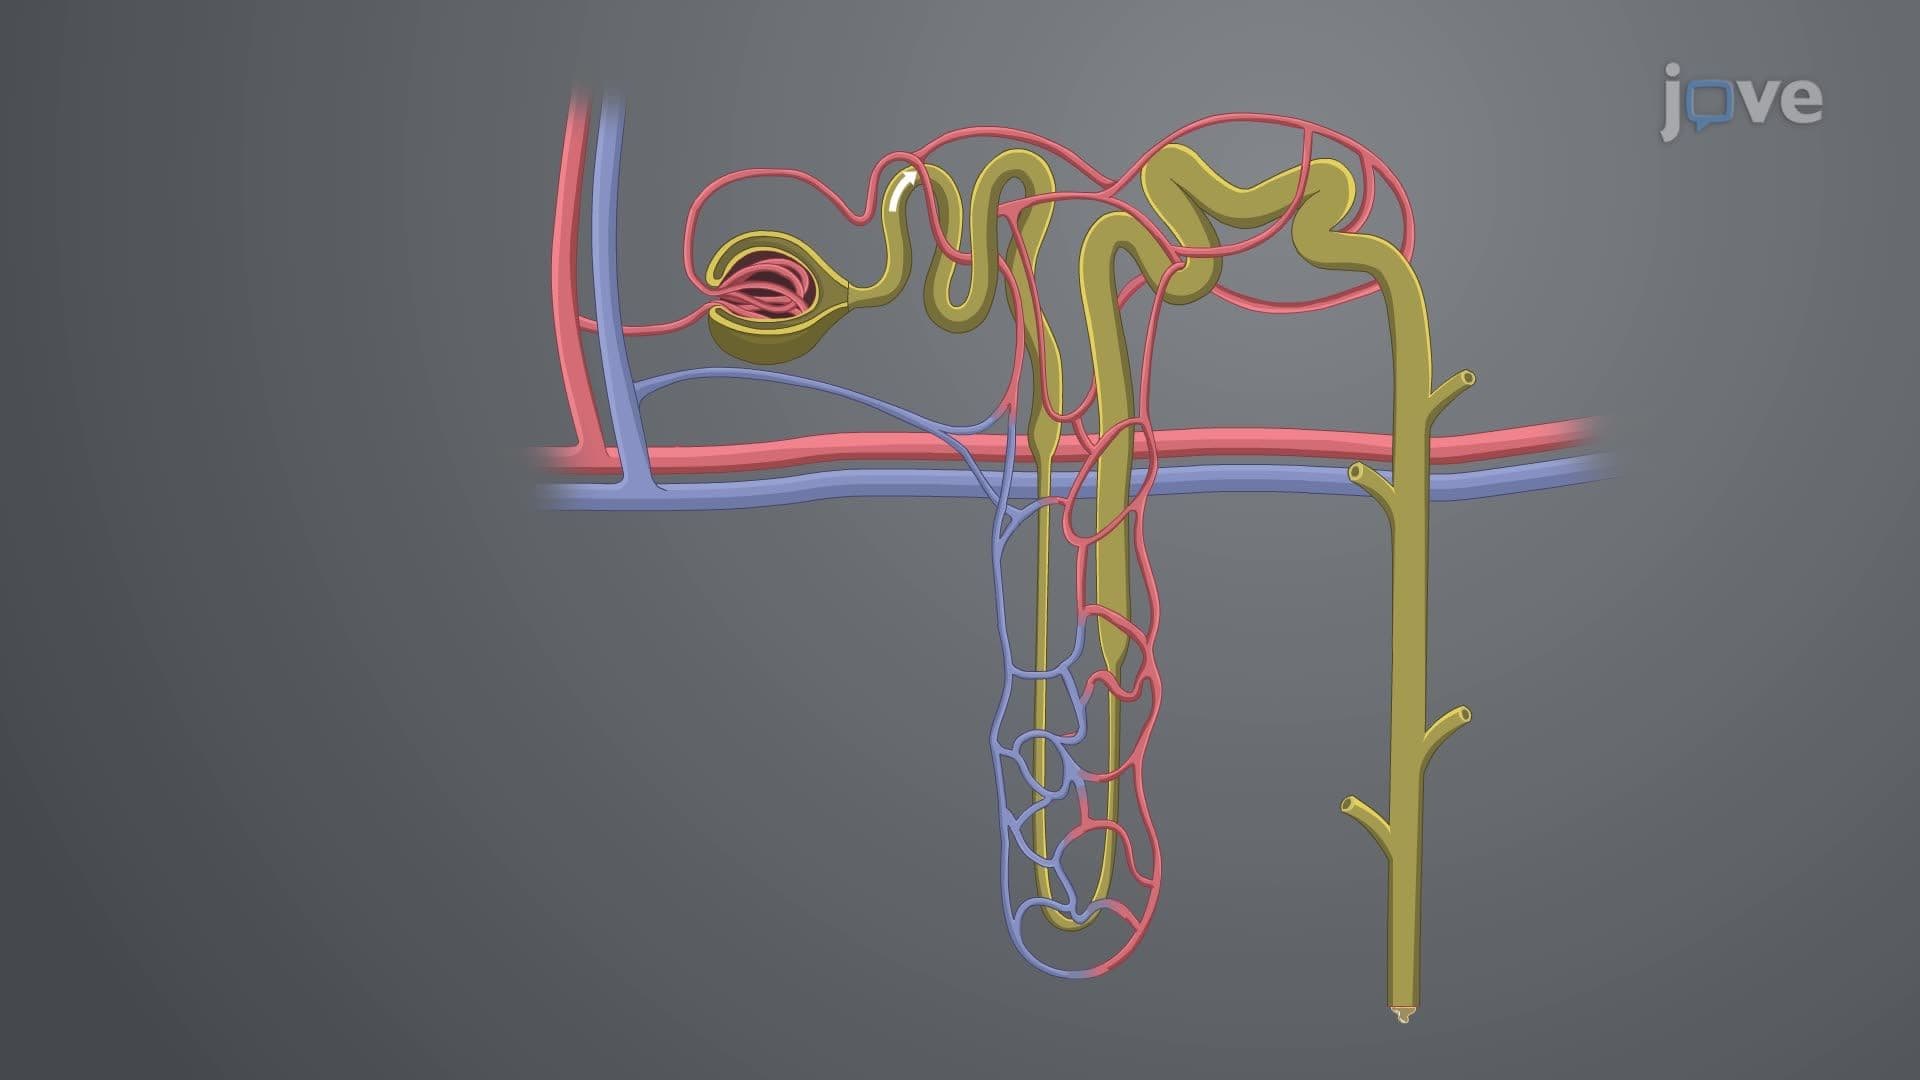
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:07
Teratogenicity