Related Experiment Video
Updated: Jun 20, 2026
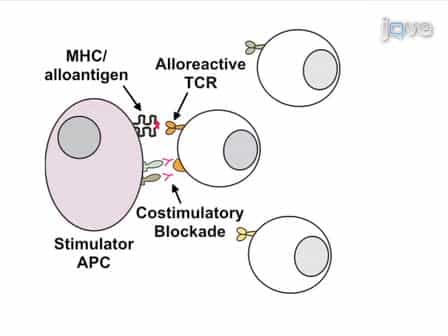

Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
Management of allosensitized cardiac transplant candidates
Mauricio Velez1, Maryl R Johnson
1Department of Medicine, University of Wisconsin School of Medicine and Public Health, Madison, WI 53792, USA. mxv@medicine.wisc.edu

Insights
Cardiac transplant candidates with ventricular assist devices (VADs) face increased allosensitization. Managing anti-HLA antibodies is crucial to reduce transplant wait times and improve outcomes, preventing rejection and vasculopathy.
Area of Science:
- Cardiology
- Immunology
- Transplantation Science
Background:
- Cardiac transplantation is the optimal treatment for end-stage heart failure.
- Ventricular assist devices (VADs) are increasingly used as a bridge to transplantation.
- VAD use is associated with rising rates of allosensitization in transplant candidates.
Purpose of the Study:
- To review the impact of allosensitization on cardiac transplant candidates.
- To discuss methods for detecting and managing anti-human leukocyte antigen (HLA) antibodies.
- To explore post-transplantation complications in sensitized recipients.
Main Methods:
- Review of current literature on allosensitization in cardiac transplantation.
- Discussion of diagnostic techniques for anti-HLA antibodies, including panel-reactive antibody (PRA) assays and solid-phase techniques.
- Analysis of therapeutic strategies for reducing pre-transplant PRA and managing post-transplant complications.
Main Results:
- Allosensitization prolongs transplant waiting times and increases risks.
- Newer antibody detection assays offer improved specificity for donor-recipient matching.
- Treatments like plasmapheresis, IVIG, and rituximab show variable success in reducing PRA.
- Antibody-mediated rejection (AMR) and cardiac allograft vasculopathy (CAV) are significant post-transplantation complications in sensitized recipients.
- Sirolimus and everolimus may delay CAV progression.
Conclusions:
- Decreasing anti-HLA antibodies in sensitized candidates is vital.
- Effective management of allosensitization is critical for successful cardiac transplantation.
- Monitoring for de novo anti-HLA antibodies post-transplantation is advisable in high-risk patients.
Abstract:
Cardiac transplantation remains the best treatment in patients with advanced heart failure with a high risk of death. However, an inadequate supply of donor hearts decreases the likelihood of transplantation for many patients. Ventricular assist devices (VADs) are being increasingly used as a bridge to transplantation in patients who may not survive long enough to receive a heart. This expansion in VAD use has been associated with increasing rates of allosensitization in cardiac transplant candidates. Anti-HLA antibodies can be detected before transplantation using different techniques. Complement-dependent lymphocytotoxicity assays are widely used for measurement of panel-reactive antibody (PRA) and for crossmatch purposes. Newer assays using solid-phase flow techniques feature improved specificity and offer detailed information concerning antibody specificities, which may lead to improvements in donor-recipient matching. Allosensitization prolongs the wait time for transplantation and increases the risk of post-transplantation complications and death; therefore, decreasing anti-HLA antibodies in sensitized transplant candidates is of vital importance. Plasmapheresis, intravenous immunoglobulin, and rituximab have been used to decrease the PRA before transplantation, with varying degrees of success. The most significant post-transplantation complications seen in allosensitized recipients are antibody-mediated rejection (AMR) and cardiac allograft vasculopathy (CAV). Often, AMR manifests with severe allograft dysfunction and hemodynamic compromise. The underlying pathophysiology is not fully understood but appears to involve complement-mediated activation of endothelial cells resulting in ischemic injury. The treatment of AMR in cardiac recipients is largely empirical and includes high-dose corticosteroids, plasmapheresis, intravenous immunoglobulin, and rituximab. Diffuse concentric stenosis of allograft coronary arteries due to intimal expansion is a characteristic of CAV. Its pathophysiology is unclear but may involve chronic complement-mediated endothelial injury. Sirolimus and everolimus can delay the progression of CAV. In some nonsensitized cardiac transplant recipients, the de novo formation of anti-HLA antibodies after transplantation may increase the likelihood of adverse clinical outcomes. Serial post-transplantation PRAs may be advisable in patients at high risk of de novo allosensitization.

Related Concept Videos
 01:16
Kidney Transplant III: Nursing Management
 01:26
Kidney Transplant II: Surgical Procedure
 01:40
Cell-mediated Immune Responses
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:30
Drug Toxicity: Allergic Reactions
 01:28
Kidney Transplant I: Introduction