Related Experiment Video
Updated: Jun 19, 2026

Pressure Controlled Ventilation to Induce Acute Lung Injury in Mice
Published on: May 5, 2011
Role of extracellular adenosine in acute lung injury
Tobias Eckle1, Michael Koeppen, Holger K Eltzschig
1Department of Anesthesiology, Mucosal Inflammation Program, University of Colorado Denver, Aurora, Colorado, USA.

Abstract:
Acute lung injury (ALI) is a lung disease characterized by pulmonary edema and severe hypoxia. The past decade hosted a search for endogenous mechanisms controlling lung inflammation and pulmonary edema during ALI. As such, recent evidence indicates extracellular adenosine in orchestrating the resolution of pulmonary edema and inflammation during ALI.

Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:10
Atelectasis II: Pathophysiology
 01:31
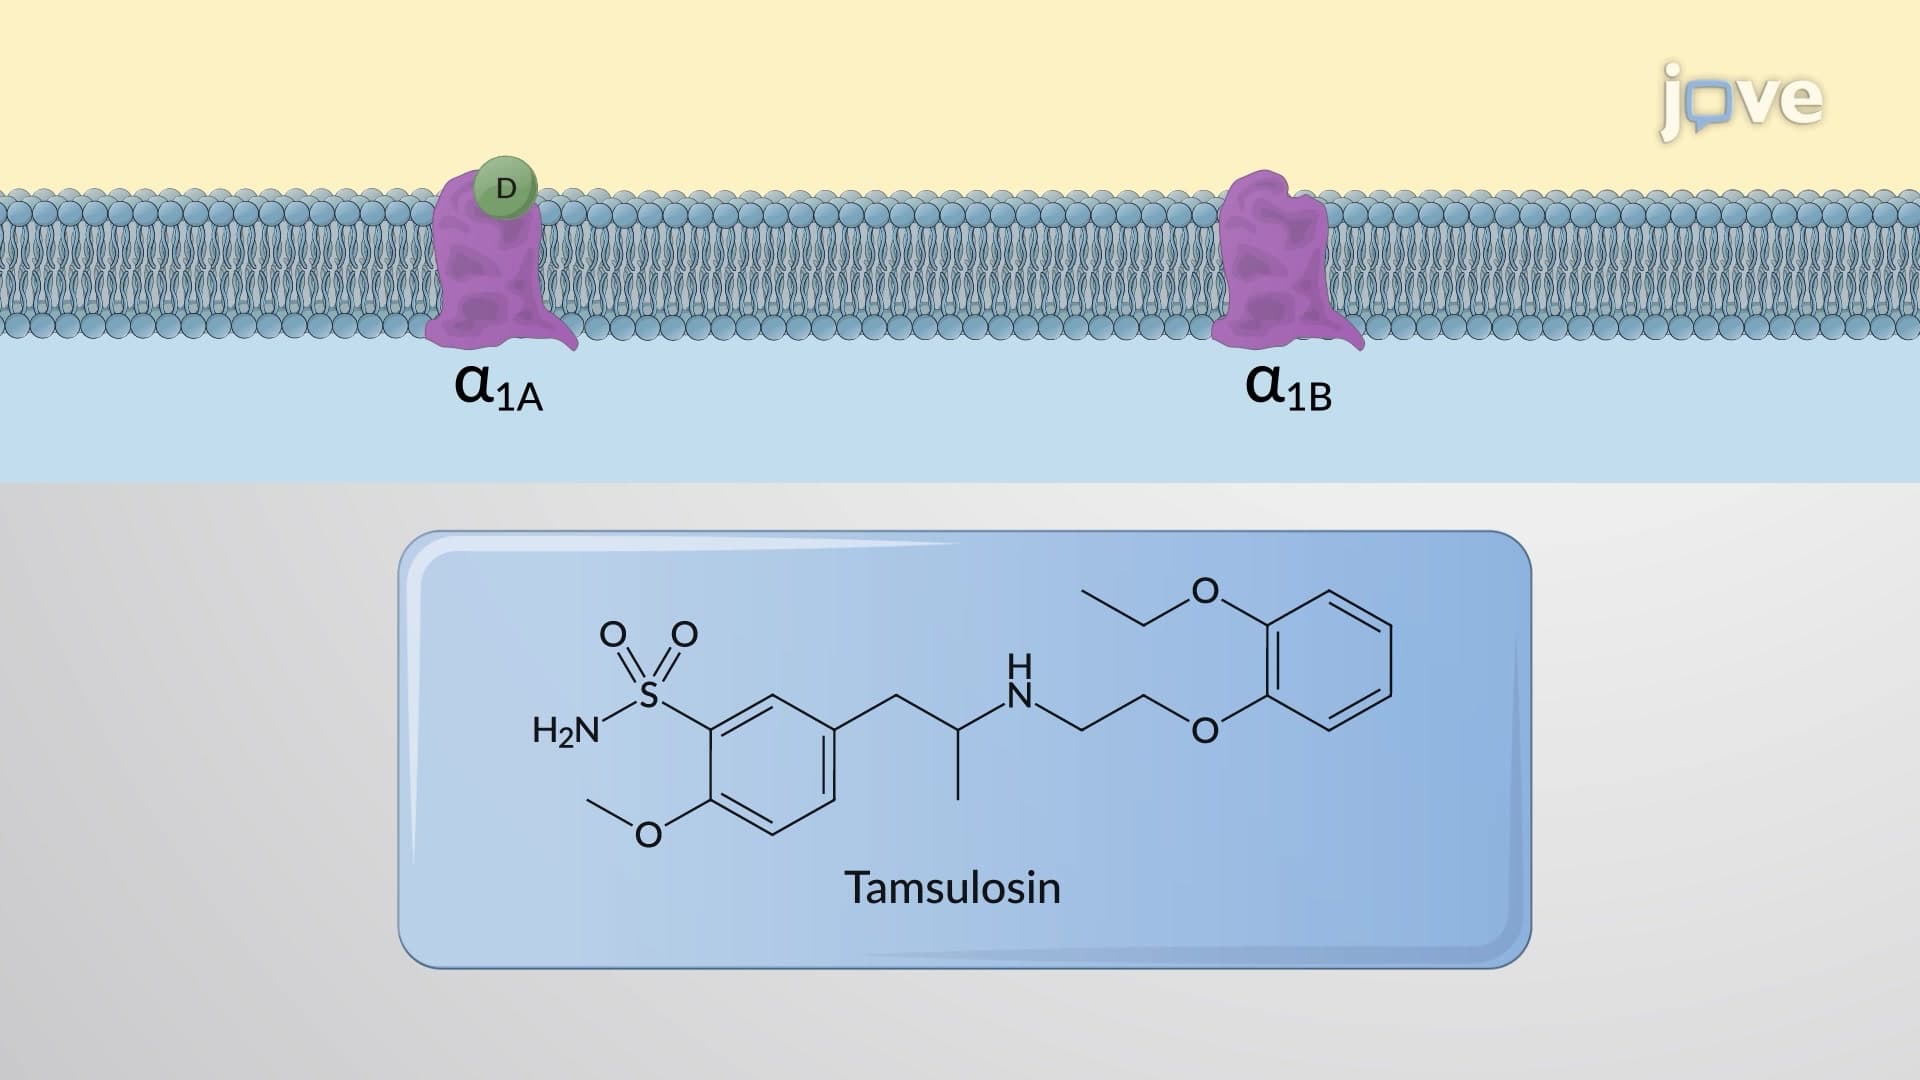
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
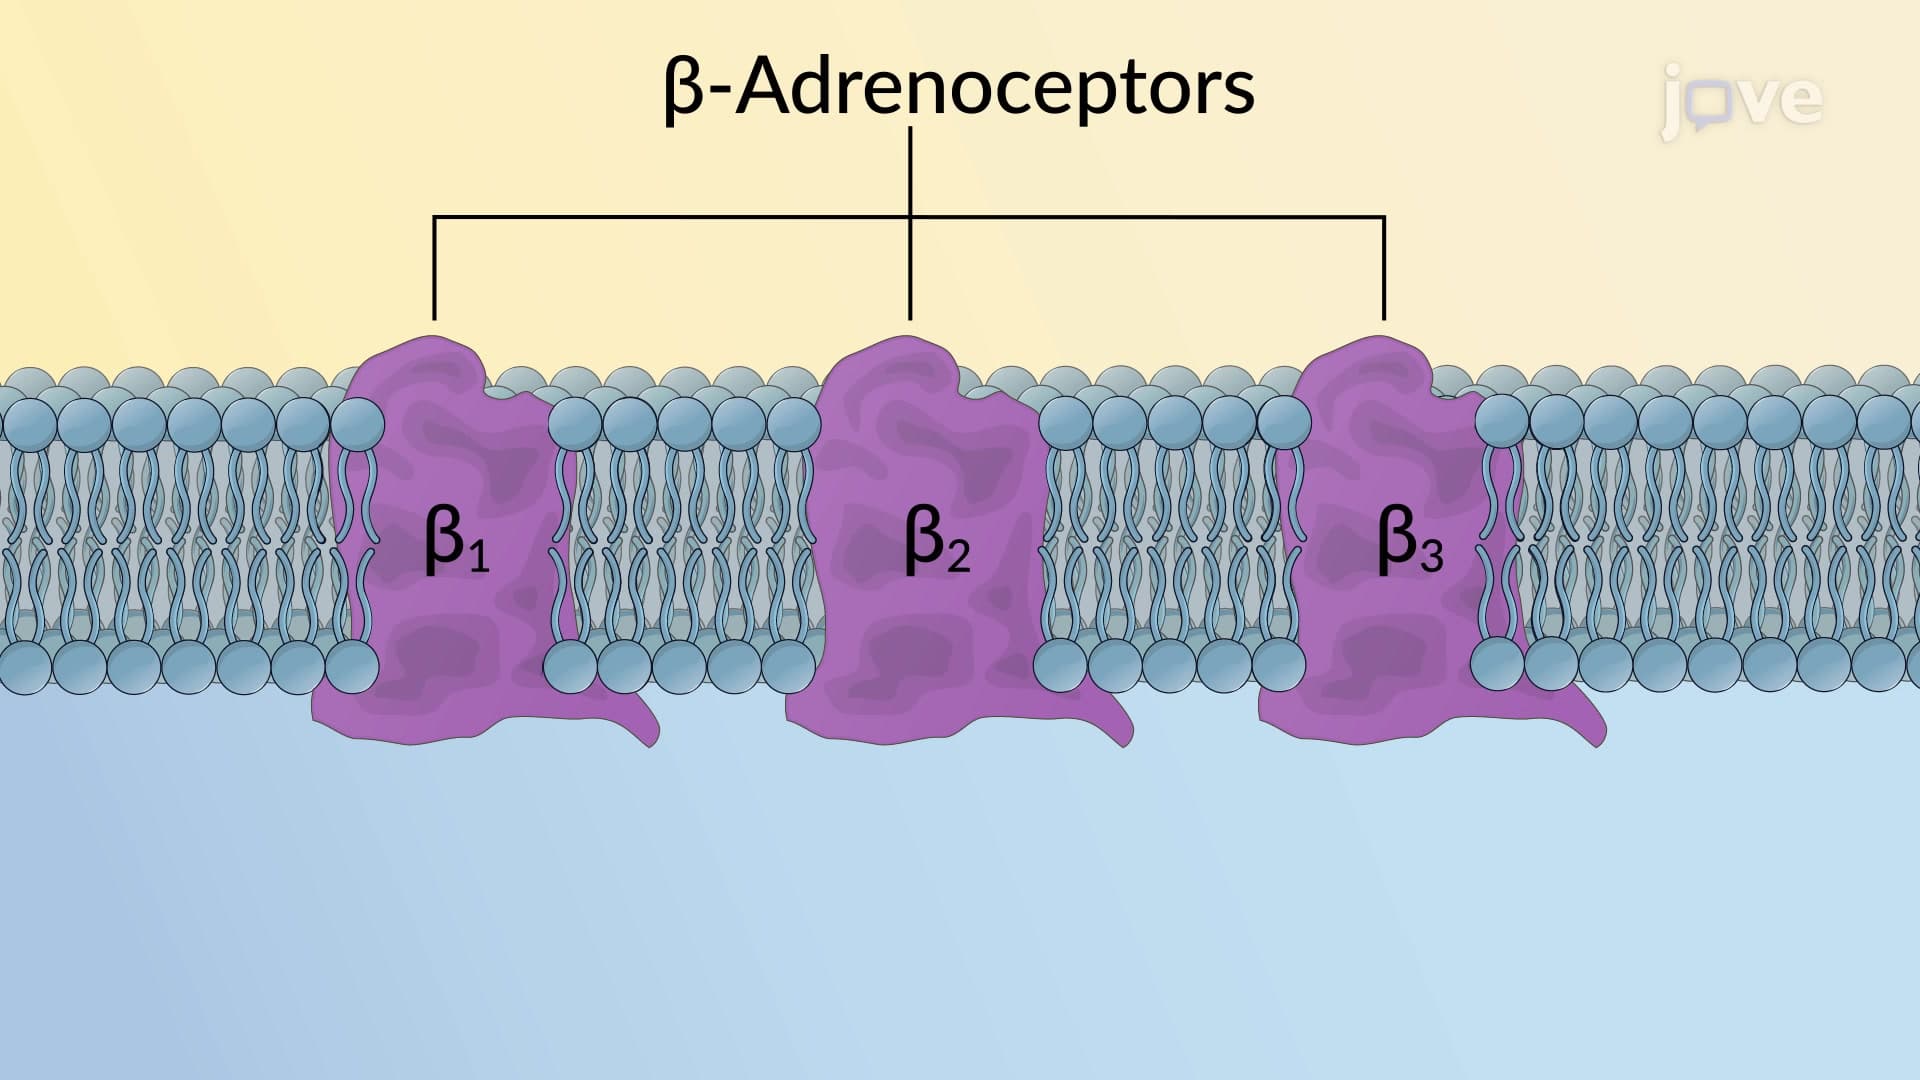
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...