[Treatment of spinal stenosis associated with lumbar degenerative kyphosis through posterior approach]
Related Experiment Video
Updated: Jun 19, 2026
Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Jingming Xie1, Ying Zhang, Yingsong Wang
1Department of Orthopaedics, 2nd Affiliated Hospital of Kunming Medical College, Kunming Yunnam, PR China. xiejingming@vip.163.com

Objective:
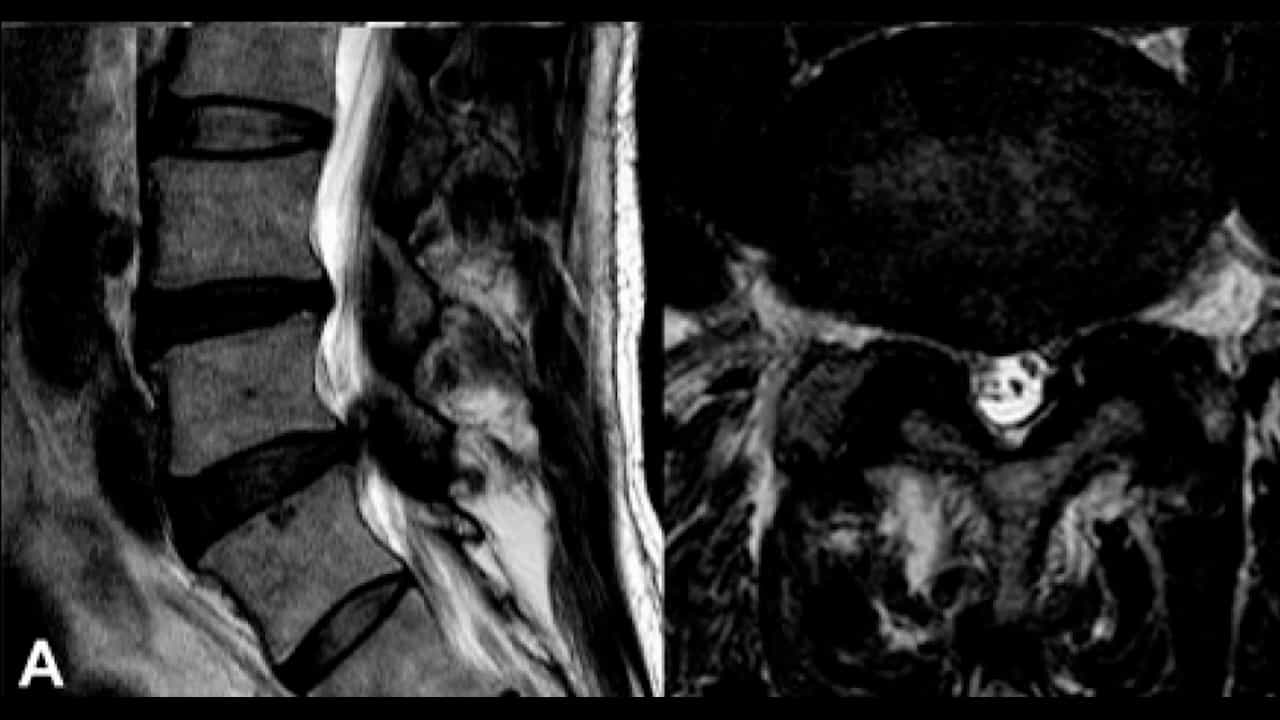
To discuss the main points of technique and the range of fusion in posterior operation of spinal stenosis associated with lumbar degenerative kyphosis (LDK).
Methods:
The clinical data were retrospectively analysed from 20 cases of spinal stenosis associated with LDK which were performed posterior operation from February 2001 to February 2008. There were 1 male and 19 females, aged 52-81 years old with an average of 64 years old. The course of disease was 6-10 years. All patients had severe low back pain. According to Frankel's neurologic function classification, there were 18 cases of grade E and 2 cases of grade D before operation. The apex of LDK included L1 in 3 cases, L2 in 10 and L3 in 7. The operational method was decided according to different characteristics of LDK. All patients were divided into three groups. Group 1 included 6 cases of sciatica and intermittent claudication with worse physical status, the segmental decompression of spinal canal, posterior intervertebral fusion and short transpedical instrument fixation were performed. Group 2 included 8 cases whose Cobb angle of LDK was less than 20 degrees, the segmental decompression of spinal canal, posterior intervertebral fusion and one-level or multi-level lamina osteotomy were performed, instrumentation-assisted correction was used. Group 3 included 6 cases whose Cobb angle of LDK was more than 20 degrees, the canal decompression and one-level transvertebral wedge osteotomy were performed, instrumentation-assisted correction, intervertebral fusion and posterior-lateral fusion were used.
Results:
Incision healed by first intention in all patients. One patient suffered from superior mesenteric artery syndrome at 6 hours after operation and healed after symptomatic management. The neurologic function was improved to grade E at 2 weeks after operation. All patients were followed-up 24-54 months (average 26 months). At last follow-up, the Oswestry Disability Index of all patients was 30.5% +/- 9.6%; showing significant difference when compared with preoperation (55.9% +/- 11.8%, P < 0.05). The back pain scoring and leg pain scoring were 2.8 +/- 1.6 and 2.4 +/- 1.6, respectively according to the Numeric Rating Scale score; showing significant differences when compared with preoperation (7.5 +/- 0.5 and 7.3 +/- 0.7, P < 0.05). The Numeric Rating Scale score and Oswestry Disability Index in all patients were improved obviously when compared with before operation (P < 0.05). During the follow-up period, there was no instrumentation failure or correction loss and the fusion rate was up to 100%.
Conclusion:
For spinal stenosis associated with LDK patients, the most important therapic purpose is to improve clinical symptom through reconstruction lumbar stabilization and spinal biomechanics line in sagittal plane. Overall estimate of the clinical appearance and imagology character is necessary when making decision of which segments needed to be fixation and fusion. Individualized treatment strategy may be the best choice.