Related Experiment Video
Updated: Jun 19, 2026
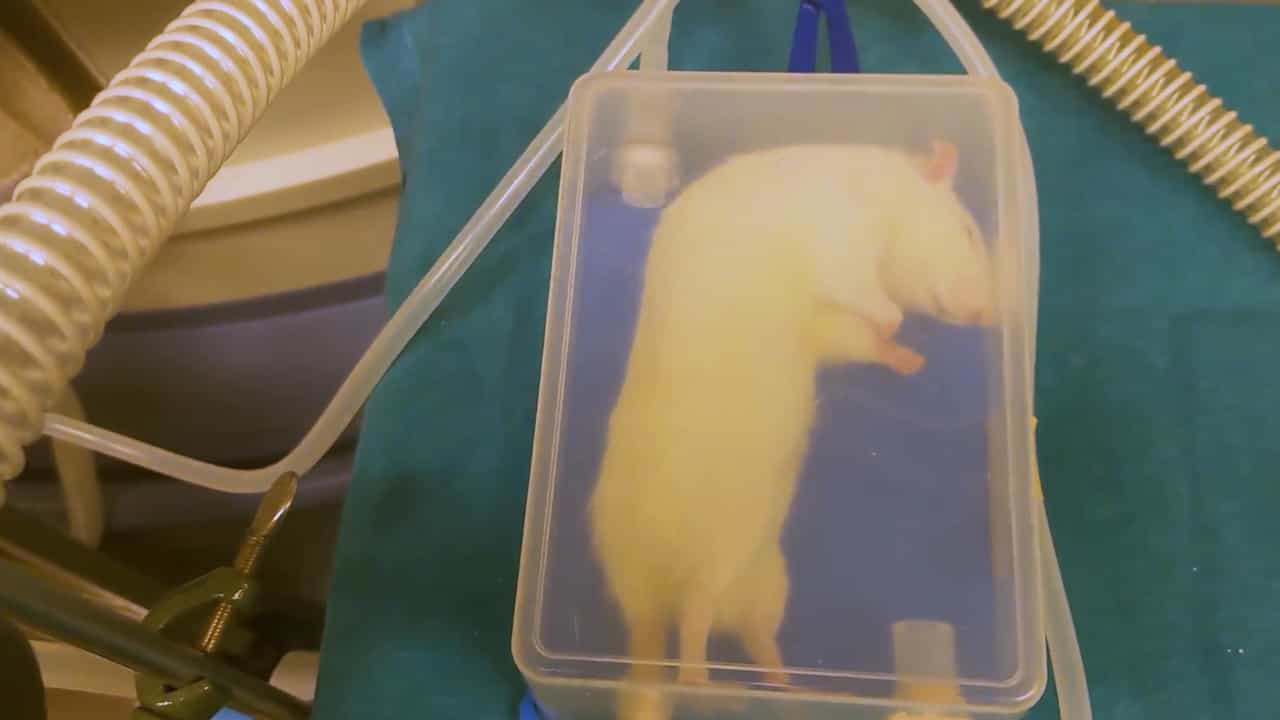

Application of Dixon's Up-and-Down Design to Estimate the Minimum Alveolar Concentration of Sevoflurane in Rats with Refined Movement Classification
Published on: July 25, 2025
An evaluation of remifentanil-sevoflurane response surface models in patients emerging from anesthesia: model
Ken B Johnson1, Noah D Syroid, Dhanesh K Gupta
1Department of Anesthesiology, University of Utah, 30 North, 1900 East, Room 3C444, Salt Lake City, UT 84132-2304, USA. ken.b.johnson@hsc.utah.ed

Introduction:
We previously reported models that characterized the synergistic interaction between remifentanil and sevoflurane in blunting responses to verbal and painful stimuli. This preliminary study evaluated the ability of these models to predict a return of responsiveness during emergence from anesthesia and a response to tibial pressure when patients required analgesics in the recovery room. We hypothesized that model predictions would be consistent with observed responses. We also hypothesized that under non-steady-state conditions, accounting for the lag time between sevoflurane effect-site concentration (Ce) and end-tidal (ET) concentration would improve predictions.
Methods:
Twenty patients received a sevoflurane, remifentanil, and fentanyl anesthetic. Two model predictions of responsiveness were recorded at emergence: an ET-based and a Ce-based prediction. Similarly, 2 predictions of a response to noxious stimuli were recorded when patients first required analgesics in the recovery room. Model predictions were compared with observations with graphical and temporal analyses.
Results:
While patients were anesthetized, model predictions indicated a high likelihood that patients would be unresponsive (> or = 99%). However, after termination of the anesthetic, models exhibited a wide range of predictions at emergence (1%-97%). Although wide, the Ce-based predictions of responsiveness were better distributed over a percentage ranking of observations than the ET-based predictions. For the ET-based model, 45% of the patients awoke within 2 min of the 50% model predicted probability of unresponsiveness and 65% awoke within 4 min. For the Ce-based model, 45% of the patients awoke within 1 min of the 50% model predicted probability of unresponsiveness and 85% awoke within 3.2 min. Predictions of a response to a painful stimulus in the recovery room were similar for the Ce- and ET-based models.
Discussion:
Results confirmed, in part, our study hypothesis; accounting for the lag time between Ce and ET sevoflurane concentrations improved model predictions of responsiveness but had no effect on predicting a response to a noxious stimulus in the recovery room. These models may be useful in predicting events of clinical interest but large-scale evaluations with numerous patients are needed to better characterize model performance.
More Related Videos


Related Concept Videos
 01:20
Inhalational Anesthetics: Overview
 01:22
Stages of General Anesthesia
 01:24
Parenteral Anesthetics: Overview
 01:24
General Anesthesia: Overview
General anesthesia induces unconsciousness in the whole body, while the others target specific areas or sensations. It is administered to minimize adverse effects, maintain...
 01:29
Pharmacodynamic Models: Direct Effect Model and Indirect Response Model
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions