Related Experiment Video
Updated: Jun 19, 2026
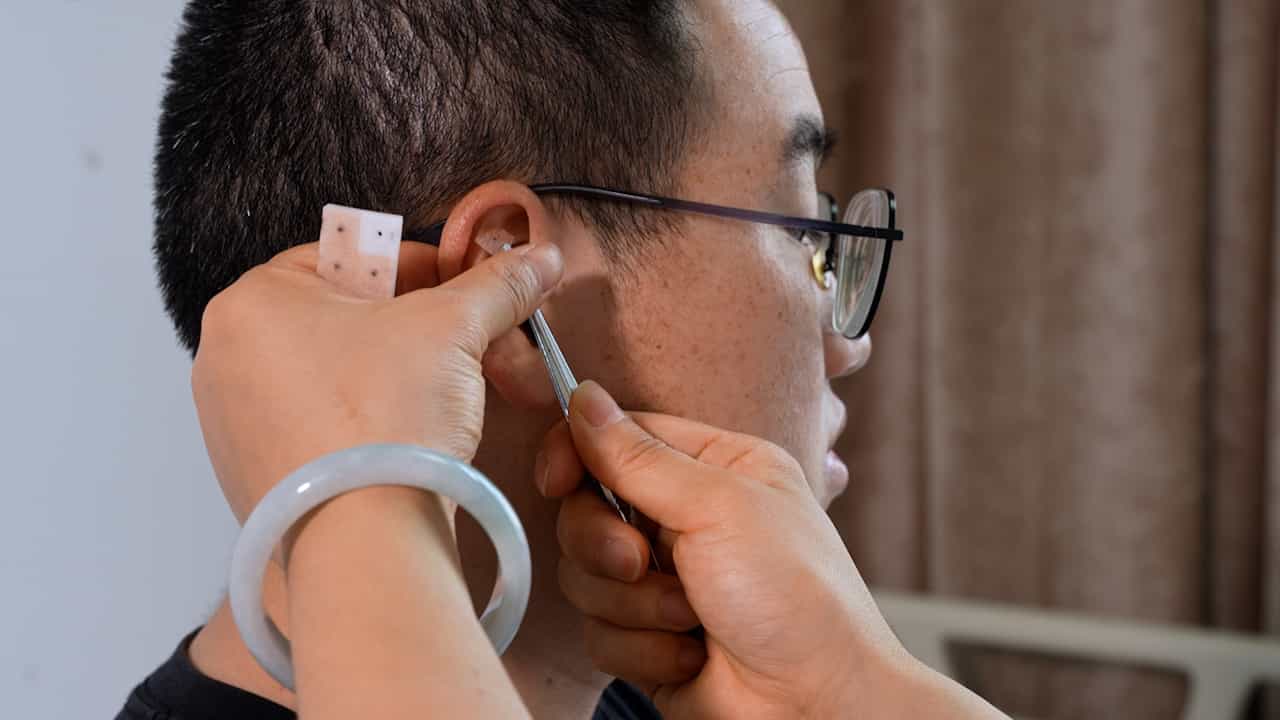
Auricular Acupressure as an Adjuvant Treatment for Wheezing in Stable Chronic Obstructive Pulmonary Disease
Published on: May 10, 2024
Recurrent wheezing illness in preschool-aged children: assessment and management in primary care practice
1Department of Pediatrics, St. Louis Children's Hospital, St. Louis, MO 63110, USA. bloomberg@kids.wustl.edu

Insights
Recurrent wheezing in young children needs careful monitoring. Using tools like the Asthma Predictive Index helps primary care physicians manage symptoms and address parental concerns about childhood asthma.
Area of Science:
- Pediatrics
- Respiratory Medicine
- Allergy & Immunology
Background:
- Recurrent wheezing affects one in three preschoolers, with varied long-term outcomes.
- Primary care physicians face challenges in diagnosing asthma and managing parental concerns.
- Distinguishing transient wheezing from early-stage asthma is crucial for appropriate intervention.
Observation:
- Children with recurrent wheezing present a diverse clinical picture.
- Some children outgrow wheezing, while others develop persistent asthma.
- Parental concerns about diagnosis and long-term medication are common.
Findings:
- A continuum of care approach is recommended for recurrent wheezing.
- Utilizing parental history, allergic disposition, and the Asthma Predictive Index aids management.
- Monitoring between acute episodes provides key insights for diagnosis and treatment.
Implications:
- Rational management of recurrent wheezing requires a proactive, monitoring-based plan.
- Early identification and intervention can improve outcomes for children at risk of asthma.
- Physicians can effectively guide parents by addressing concerns and implementing a structured monitoring approach.
Abstract:
Recurrent wheezing is common in preschool-aged children, with 1 in 3 children experiencing at least 1 acute wheezing illness before the age of 3 years. These children represent a diverse group, with some going on to present with asthma at school age and others experiencing complete resolution of symptoms. The primary care physician is faced with a dilemma of when to recommend daily therapy. He or she must also answer parents' concerns, often expressed as, "Does my child have asthma?" and "Will my child have to take medication the rest of his or her life?" This article presents recent studies and recommendations that can guide the physician in approaching the child and the parent with rational management. The emphasis is on viewing recurrent wheezing as a continuum requiring a plan of monitoring that starts with the very first episode. Using background information from the parents and a history of the child's allergic disposition, one can discuss with parents the risks of developing asthma and, together with planned monitoring, prescribe appropriate management. The primary care physician can plan management by using the Asthma Predictive Index and employing specific questions for features present during the intervals between acute episodes. Together with close monitoring, the physician will have a compass that effectively directs rational management.
Related Concept Videos
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:30
Asthma-IV: Nursing Management
First, in...
 01:28
Asthma I: Introduction
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:13
Asthma III: Clinical Manifestations
 01:29
Asthma-I: Introduction