Related Experiment Video
Updated: Jun 19, 2026


Bronchial Thermoplasty: A Novel Therapeutic Approach to Severe Asthma
Published on: November 4, 2010
Mometasone furoate vs fluticasone propionate with salmeterol: multivariate analysis of resource use and
Prakash Navaratnam1, Howard S Friedman, Eduardo Urdaneta
1Eympres Research, LLC, Hilliard, OH, USA. Eympres@gmail.com

Objective:
Although current National Asthma Education and Prevention Program (NAEPP) guidelines indicate low-dose inhaled corticosteroid (ICS) monotherapy as the preferred treatment for patients with mild persistent asthma, many patients receive ICS and long-acting beta(2)-agonist (LABA) combinations. The objective of the current study was to evaluate asthma-related charges in patients with mild asthma who began treatment with mometasone furoate (MF) versus those who began treatment with a fluticasone propionate/salmeterol (FPS) combination.
Research Design And Methods:
This retrospective administrative claims database analysis collected data from the 365-day periods before (preindex period) and after (postindex period) the study index date from patients with mild asthma aged 12 to 65 years who began treatment with MF or FPS. Asthma-related inpatient, outpatient, pharmaceutical, and total charges; exacerbations; short-acting beta(2)-agonist (SABA) canister claims; and adherence to therapy were assessed. Matched cohorts of MF and FPS patients were compared using multivariate generalized linear regression models.
Results:
Among matched MF (n = 4094) and FPS (n = 4094) cohorts, MF patients had significantly lower postindex asthma-related total charges ($2136 vs $2315, respectively; P = 0.0003), lower pharmaceutical charges ($727 vs $925, respectively; P < 0.0001), fewer exacerbations (0.14 vs 0.16, respectively; P = 0.0306), fewer SABA canister claims (0.9 vs 1.0, respectively; P < 0.0001), and greater adherence measured by prescription fills (3.0 vs 2.8, respectively; P < 0.0001). Asthma-related inpatient charges, outpatient charges, and adherence measured by percent of days covered were not significantly different between treatment cohorts. Limitations included a lack of additional ICS and ICS/LABA therapies, a lack of pediatric patients, and the general limitations associated with retrospective database analyses (e.g., no patient records).
Conclusions:
These data suggest that MF may be more cost-effective than FPS for the treatment of mild asthma. To effectively and efficiently manage asthma, it is important for clinicians to follow current NAEPP guidelines, which indicate ICS monotherapy as preferred treatment for mild persistent asthma.
Related Concept Videos
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
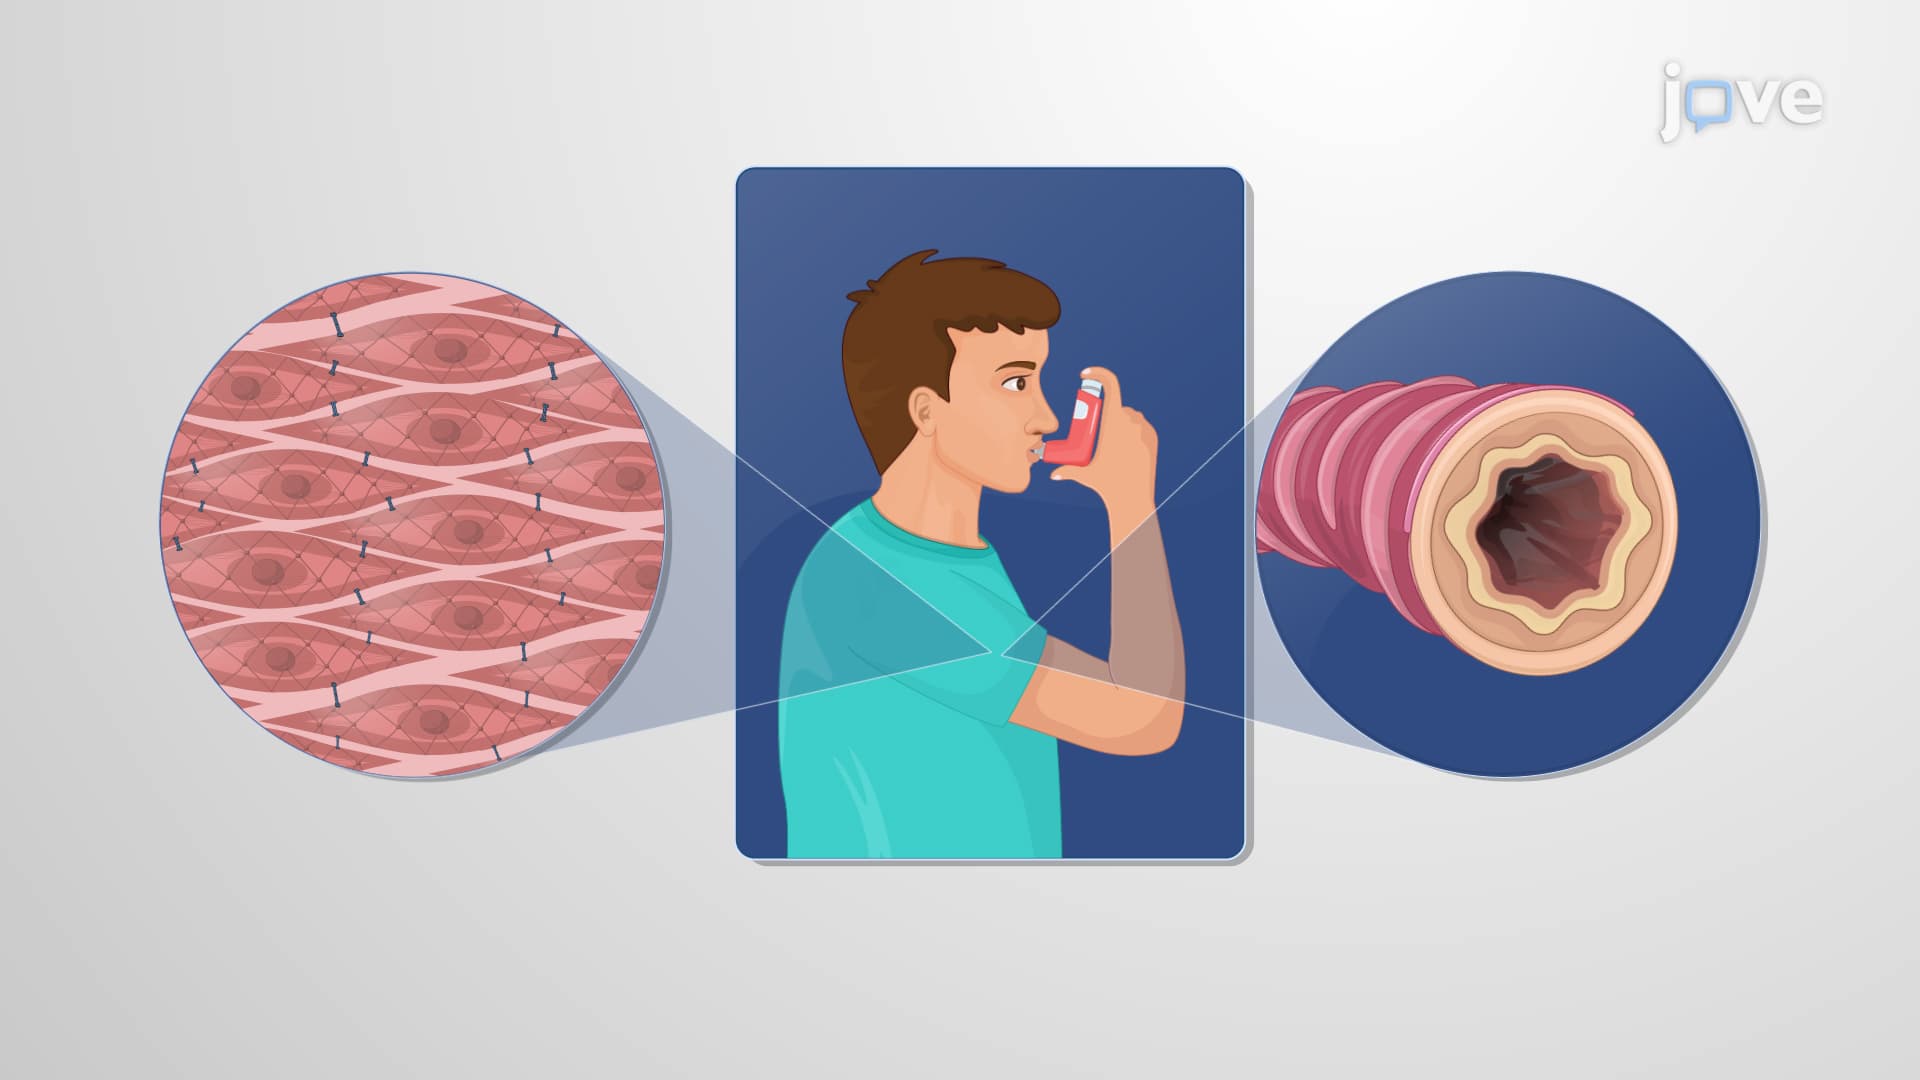
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids