Related Experiment Video
Updated: Jun 19, 2026
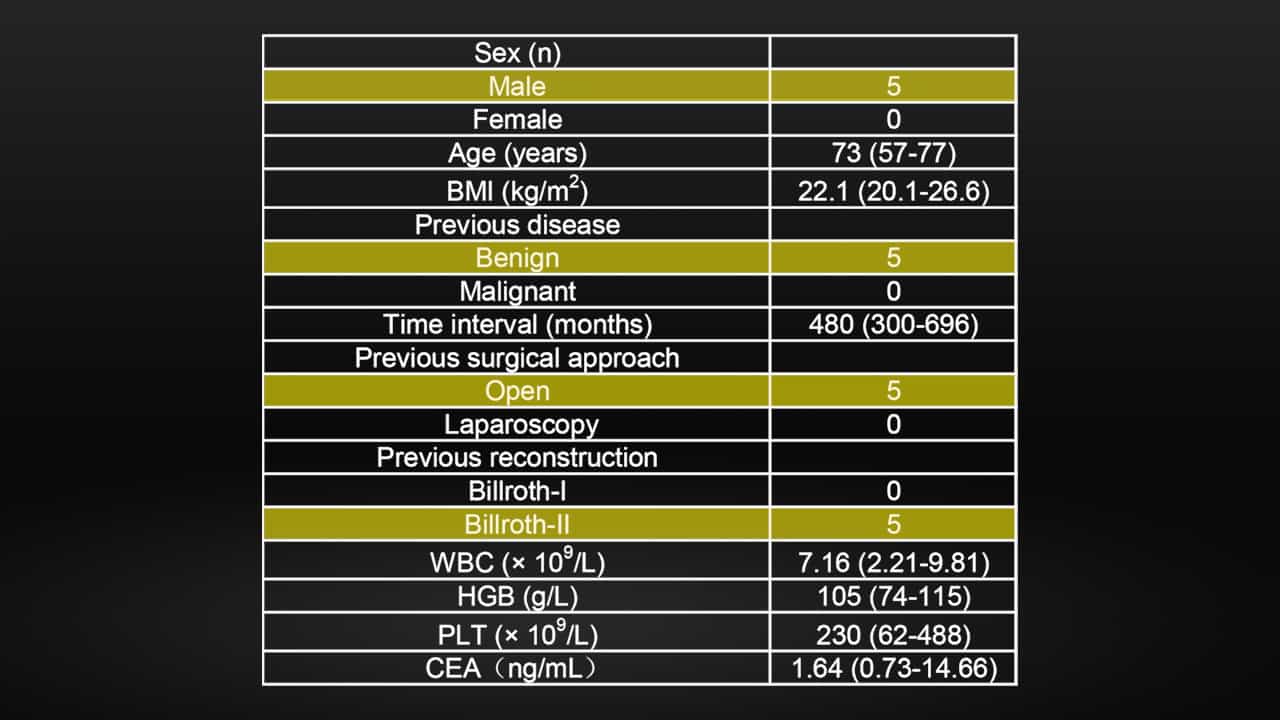
Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025
[Juvenile gastric polyposis: differential diagnosis for recurrent nausea, vomiting, upper abdominal pain and
M Stöwhas1, K Dommisch, J Sauer
1Klinik für Allgemein- und Viszeralchirurgie, HELIOS Kliniken Schwerin, 19055 Schwerin, Germany. mathias.stoewhas@helios-kliniken.de

History And Admission Findings:
A 46-year-old woman presented with nausea and vomiting, colics and localized pain in the upper abdomen. There was a family history of juvenile polyposis (3 of 4 siblings). Twelve years ago a colectomy had been performed in the patient for a gastric mucosal polyps.
Investigations:
The physical examination showed a nearly normal BMI of 20,9 kg/m2. Gastroscopy showed polyps prolapsed into the duodenum, some of them incarcerated causing the listed symptoms.
Diagnosis, Treatment And Course:
Because of progressing symptoms a total gastrectomy of a huge stomach was performed. Antral polyps were found to have prolapsed through the pylorus, causing gastric outlet obstruction. Histology confirmed juvenile polyposis. There was no evidence of a malignant process.
Conclusions:
Juvenile polyposis is a rare inherited disease. Polyps can affect the entire gastrointestinal tract but predominantive in the colon. The clinic course of the juvenile polyposis is highly variable, but generally benign. Although malignant degeneration has been reported. A cumulative risk of malignant degeneration for the entire gastrointestinal tract has been estimated as being between 10 and 50 %, but it is very rare in the upper gastrointestinal tract. People with juvenile polyposis should have regular endoscopic controls. But if endoscopic control are impossible, total gastrectomy with lymphadenectomy may sometimes be necessary. Even after such extensive resection the patient may remain without symptoms.
Related Concept Videos
 01:11
Pyloric Obstruction
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:07
Intestinal Obstruction II: Pathophysiology
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:22
Pathophysiology of Vomiting