Eight-year experience with minimally invasive cardiothoracic surgery
Related Experiment Video
Updated: Jun 19, 2026
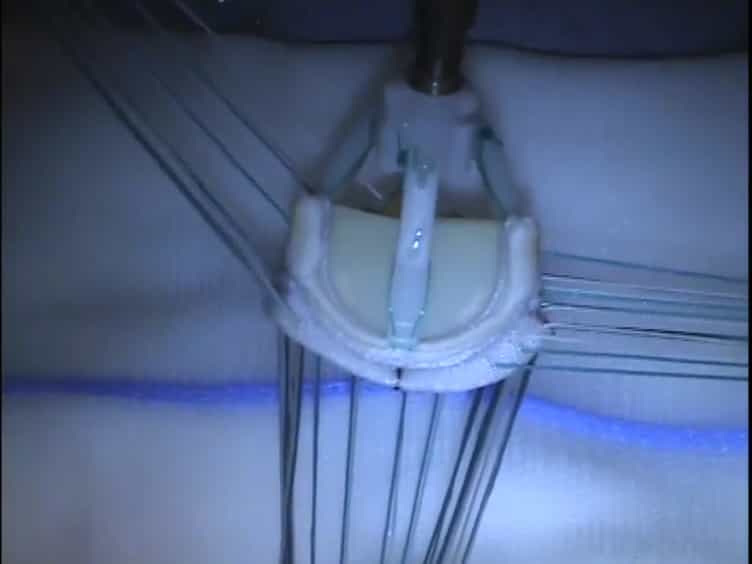
Technique and Patient Selection Criteria of Right Anterior Mini-Thoracotomy for Minimal Access Aortic Valve Replacement
Published on: March 26, 2018
Alexander Iribarne1, Anna Karpenko, Mark J Russo
1Division of Cardiothoracic Surgery, Department of Surgery, College of Physicians and Surgeons, Columbia University Medical Center, 77 Fort Washington Avenue, Milstein Hospital, Suite 7-435, New York, NY, 10032, USA. ai2141@columbia.edu

Background:
Over the past decade, minimally invasive cardiac surgery (MICS) has emerged as an accepted approach for the management of cardiac disease that requires a surgical solution. We report the results of an 8-year, single-institution experience with MICS.
Methods:
Between January 1, 2000 and December 31, 2007, a total of 910 patients underwent MICS. Major cases included aortic valve procedures (71, 7.8%), coronary artery bypass grafting (96, 10.5%), atrioseptal defect repair (103, 11.3%), and mitral valve procedures (507, 55.7%). Major outcomes of interest included the complication and mortality rates.
Results:
The mean age of the patients was 57 +/- 15 years; the mean ejection fraction was 55% +/- 11%; and the mean body mass index was 26.1 +/- 4.9. Overall, 782 cases (85.9%) were performed through a mini-thoracotomy. Most of the cases were accomplished through central cannulation (765, 84.0%), and venous drainage was most commonly performed in a bicaval fashion (percutaneous superior vena cava and percutaneous inferior vena cava). The mean aortic cross-clamp and cardiopulmonary bypass (CPB) times were 58.1 +/- 44.9 and 101.9 +/- 66.8 min, respectively. Conversion to full sternotomy occurred in 10 patients, and the median length of stay in hospital was 6 days. The overall complication rate was 8.8%, and the 30-day mortality rate was 2.9%. In the multivariate logistic regression analysis, risk factors associated with in-hospital complications included age, CPB time, arterial cannulation location, conversion from off-CPB to on-CPB, hepatic insufficiency, and diabetes. In the multivariate hazards regression analysis, risk factors associated with mortality included postoperative stroke, renal failure, and sternal wound infection; CPB time; and previous surgery.
Conclusions:
In our experience, minimally invasive approaches are effective and reproducible for a variety of cardiac operations, with acceptable operating time durations, morbidity, and mortality.
Related Concept Videos
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management