Related Experiment Video
Updated: Jun 19, 2026

Manufacture of a Multi-Purpose Low-Cost Animal Bench-Model for Teaching Tracheostomy
Published on: May 18, 2019
Pediatric tracheostomy: complications and role of home care in a developing country
Sadaf Zia1, Muhammad Arshad, Zafar Nazir
1Department of Otolaryngology Head and Neck Surgery, Aga Khan University Hospital, Karachi, Pakistan. Sadafzia979@yahoo.com

Insights
Pediatric tracheostomy is increasingly performed for congenital malformations, improving survival. Sending children home with tracheostomy tubes is feasible and beneficial for long-term recovery.
Area of Science:
- Pediatric Otolaryngology
- Pediatric Surgery
- Critical Care Medicine
Background:
- Tracheotomy indications in children have shifted from acute infections to congenital malformations.
- Increased survival rates for pediatric tracheostomy patients necessitate home care planning.
Purpose of the Study:
- To analyze tracheostomy indications and complications in pediatric patients.
- To determine the rate of ventilator weaning facilitated by tracheostomy.
- To assess the feasibility of home-based tracheostomy care for children.
Main Methods:
- Retrospective study of 127 pediatric patients undergoing tracheostomy.
- Chart review to analyze indications, outcomes, and complications.
- Evaluation of in-hospital and at-home complication rates.
Main Results:
- Prolonged ventilation (61%) was the primary indication for tracheostomy.
- Successful ventilator weaning occurred in 78.8% of patients (p=0.001).
- 48.8% of patients sent home with tracheostomy tubes were decannulated.
Conclusions:
- Tracheostomy in the prolonged ventilation group reduces intensive care unit (ICU) stay and prevents nosocomial infections.
- Home care for tracheostomy tubes is a viable option for children requiring extended recovery.
- Addressing the economic burden of prolonged ICU care supports home-based tracheostomy management.
Introduction:
Tracheotomy in its earlier days was most commonly performed for acute airway infection in children. Its indications are now changing; it is now most commonly performed for congenital malformations (McMurray and Prescott in Practical pediatric otolaryngology. W.B. Saunders Company, Philadelphia, pp 575-592, 1996). This shift in indication has increased the rate of survival of such patients, and therefore the number of children going home after tracheostomy has also increased.
Objective:
This study was conducted (1) to observe the pattern of indication and complications for tracheostomy, in our part of the world, (2) the rate at which tracheostomy can help wean patients off the ventilator, and (3) the feasibility of sending these children home with tracheostomy.
Materials And Methods:
A retrospective study was done on 127 patients. The indications, final outcome and the complications encountered in and outside the hospital were studied through review of charts.
Results:
Based on the main indications, patients were grouped into: prolonged ventilation group (PV) 61%, followed by mechanical obstruction group (MO) 22%, and the last being adjunct to surgery group (AS) 17%. The in-hospital complication rate was 30% and that at home was 18.11%. The most common complications included upper respiratory tract infections, and blockage or displacement of tubes. The late complication rate was 4%. Hundred (78.8%) patients on the ventilator could be successfully weaned off, with a p value of 0.001; 81 were sent home with the tracheostomy tube (TT). Forty of these were successfully decannulated and the overall decannulation rate was 48.8%.
Conclusion:
A large number of tracheostomies have been performed in the PV group to reduce the intensive care unit (ICU) stay and to prevent nosocomial infections. The need arises from the high cost of prolonged stay in an ICU setup, which is a cause of major economic burden, and lack of financial assistance for these patients worsens the scenario. Home care of the tracheostomy tubes remains a good option for patients requiring long periods of time to overcome their primary pathology.


Related Concept Videos
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask and...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
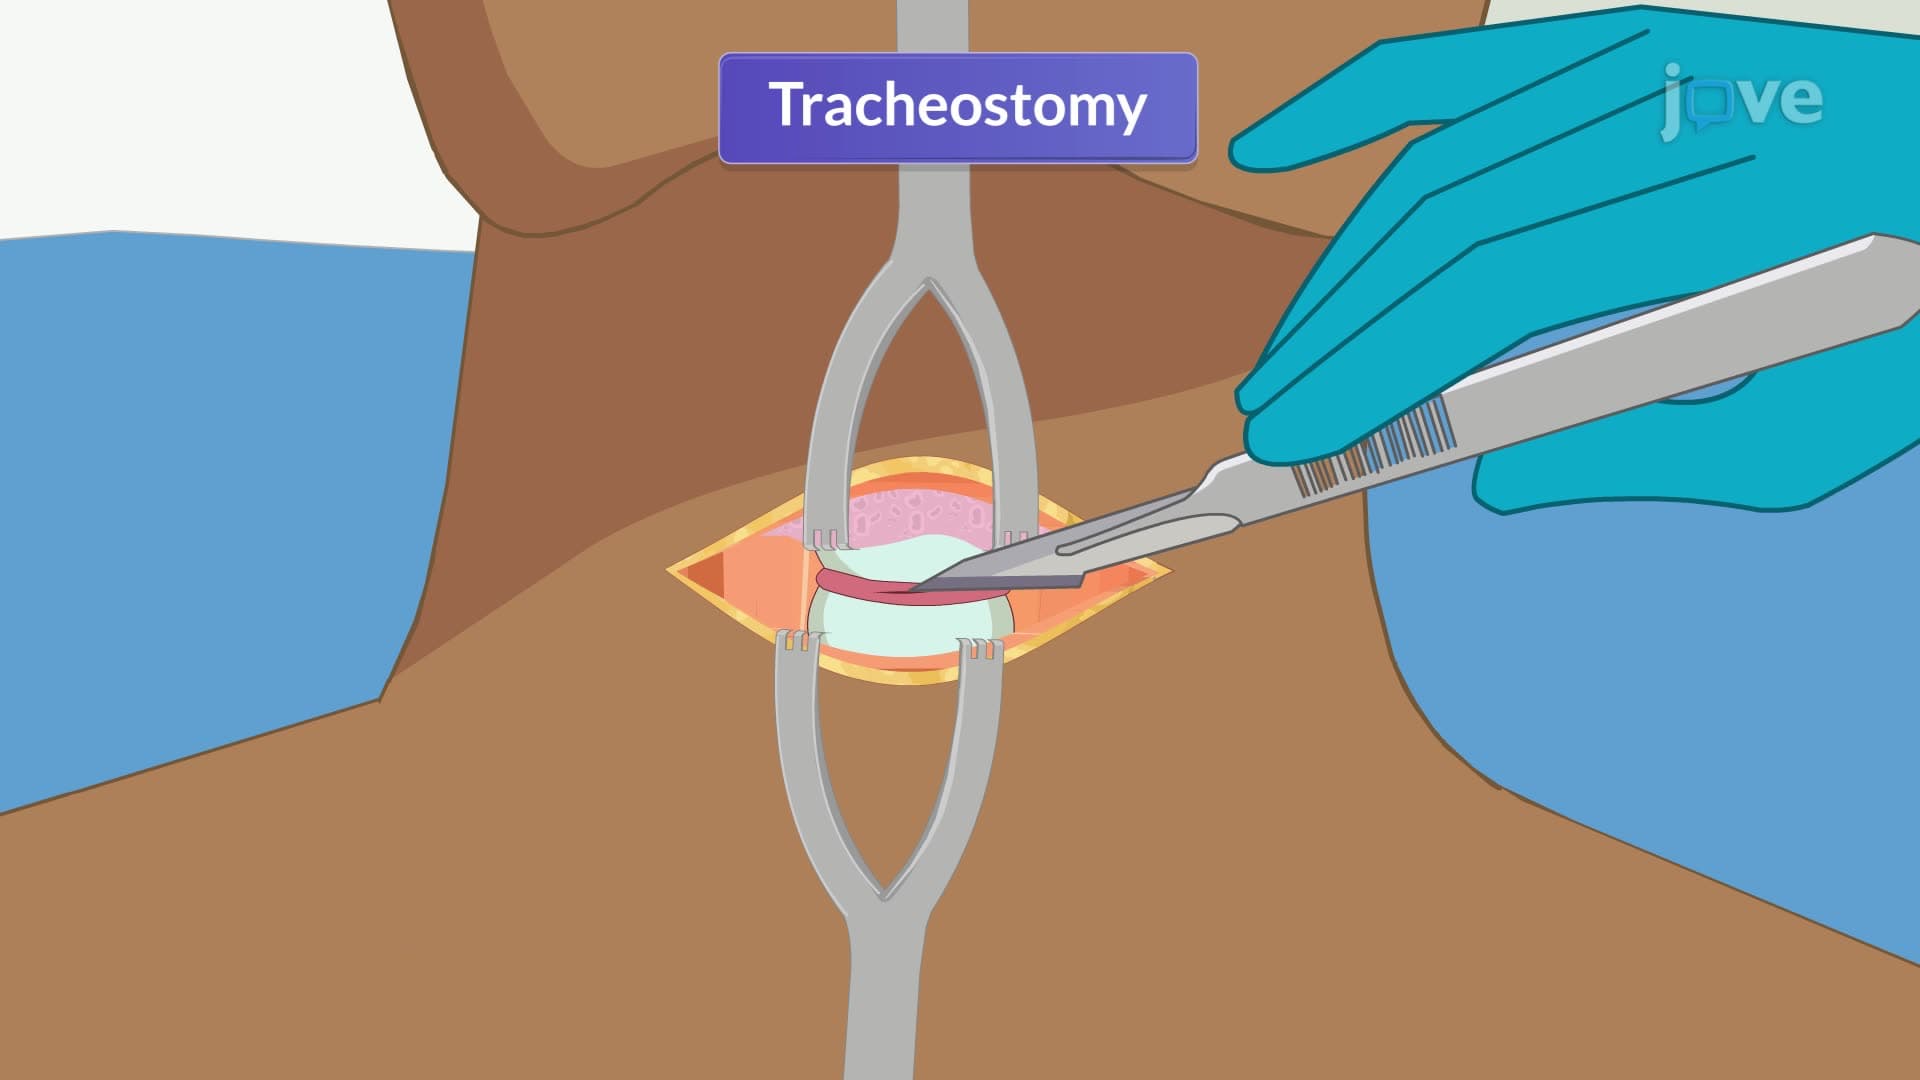
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...