Related Experiment Video
Updated: Jun 19, 2026
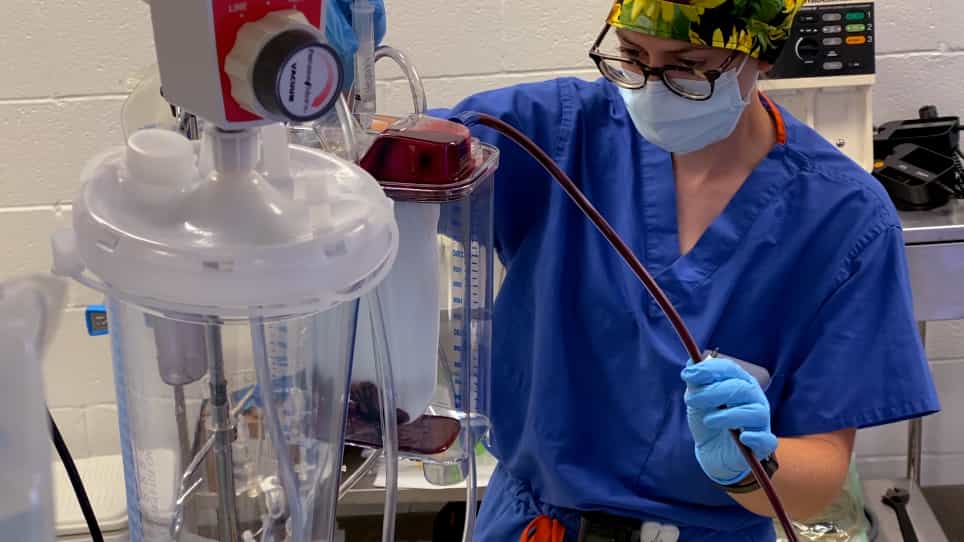

A Porcine Heterotopic Heart Transplantation Protocol for Delivery of Therapeutics to a Cardiac Allograft
Published on: February 14, 2022
Chylopericardium in a child with impaired venous access following small bowel transplantation

Insights
A child with impaired venous access after a small bowel transplant developed chylopericardium. Treatment involved pericardiocentesis and a specialized diet, with venous occlusion identified as the likely cause.
Area of Science:
- Pediatric surgery
- Gastroenterology
- Cardiology
Background:
- A 10-year-old child with complex venous access issues (occluded jugular, subclavian, and innominate veins) underwent an isolated small bowel transplant.
- Post-transplant follow-up revealed the development of chylopericardium, presenting as lethargy and shortness of breath.
Observation:
- Diagnostic imaging, including MR venography and lymphangiography, failed to pinpoint the exact site of the lymphatic leak.
- The patient's chylopericardium was managed through pericardiocentesis and a medium-chain triglyceride (MCT) diet.
Findings:
- The primary finding suggests that venous occlusion in the subclavian veins, leading to increased backpressure, was the most probable cause of the lymphatic leak and subsequent chylopericardium.
- This case highlights a rare complication following intestinal transplantation in a pediatric patient with pre-existing venous anomalies.
Implications:
- Understanding the link between venous occlusion and lymphatic leaks is crucial for managing post-transplant complications.
- This case underscores the importance of considering venous hypertension in the etiology of chylopericardium in immunocompromised patients.
- Further research into diagnostic and therapeutic strategies for chylopericardium secondary to venous issues post-transplant is warranted.
Abstract:
A 10-yr-old child with impaired venous access (bilateral occlusion of internal jugular veins, subclavian veins, and inominate veins) underwent an isolated small bowel transplant. He presented with lethargy, shortness of breath 13 months into his follow-up and was diagnosed to have chylopericardium. MR venography and lymphangiography could not demonstrate the site of lymphatic leak. His chyloperciardium was treated with pericardiocentesis and MCT diet. The most likely cause for the chylopericardium was venous occlusion of the subclavian veins with backpressure resulting in a lymphatic leak. A brief review of literature along with treatment options is discussed.