Related Experiment Video
Updated: Jun 19, 2026
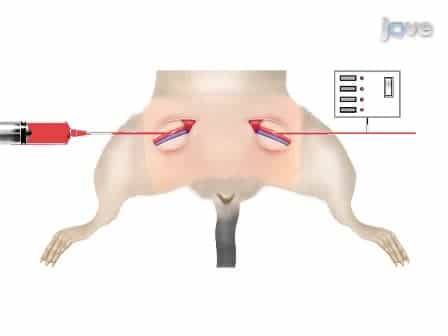
Fixed Volume or Fixed Pressure: A Murine Model of Hemorrhagic Shock
Published on: June 6, 2011
BLOOD VOLUME IN WOUNDED SOLDIERS : I. BLOOD VOLUME AND RELATED BLOOD CHANGES AFTER HEMORRHAGE
1Base Hospital No. 5, U. S. Army, France.

Blood volume tests made by the vital red method (Keith, Rowntree, and Geraghty) on patients after hemorrhage showed a marked reduction in the total blood bulk. Not uncommonly the blood volume was less than 60 per cent of the normal. The reduction after a certain point had been reached seemed to parallel the decrease in blood pressure. This relation of diminished blood volume to low pressure suggested a rough method of estimating blood volume from the change in blood pressure. By means of the blood volume and the hemoglobin per cent the actual amount of blood loss was determined. Cases of severe anemia showed a loss of as much as five-sixths of their total hemoglobin. Progressive changes in blood volume following hemorrhage were estimated in three ways: (1) repeated vital red tests; (2) calculation from changes in hemoglobin per cent produced by the injection of gum acacia; (3) calculation from changes in hemoglobin per cent following the dilution of the blood by the patient's own body fluids. The effects of the different methods of transfusion and of injection of gum acacia on blood volume were observed. No differences were apparent. It was found that transfusion and gum injections only partially restored the blood volume. Forced fluids by mouth were found to bring about its complete restoration in a comparatively short time. It was observed that the organism did not restore its blood volume beyond a certain point when a further increase in it would, by dilution, have brought the hemoglobin per cent to a very low figure. In such cases a further increase of the blood volume occurred only when the hemoglobin rose. In cases with a low hemoglobin per cent as the result of a restoration of the blood bulk an abnormally high blood pressure appeared, which continued until the hemoglobin per cent again increased. Accompanying the low blood pressure seen shortly after hemorrhage was a well marked difference in hemoglobin per cent between capillary and venous blood, with a relative concentration on the capillary side. As compensation occurred and blood pressure rose this difference lessened until the two readings were identical, indicating an even redistribution of the red blood cells. Reticulated red cell counts made in these cases showed that a marked bone marrow stimulation occurs after hemorrhage. However, except in the very anemic cases the degree of increased blood production seemed to depend largely on the restoration of the blood volume. The patients who were put on forced fluids, with consequent rapid restoration of blood volume, showed a much higher per cent of reticulated cells than those in whom no attempt was made to increase the amount of fluid in circulation.
Blood volume tests made by the vital red method (Keith, Rowntree, and Geraghty) on patients after hemorrhage showed a marked reduction in the total blood bulk. Not uncommonly the blood volume was less than 60 per cent of the normal. The reduction after a certain point had been reached seemed to parallel the decrease in blood pressure. This relation of diminished blood volume to low pressure suggested a rough method of estimating blood volume from the change in blood pressure. By means of the blood volume and the hemoglobin per cent the actual amount of blood loss was determined. Cases of severe anemia showed a loss of as much as five-sixths of their total hemoglobin. Progressive changes in blood volume following hemorrhage were estimated in three ways: (1) repeated vital red tests; (2) calculation from changes in hemoglobin per cent produced by the injection of gum acacia; (3) calculation from changes in hemoglobin per cent following the dilution of the blood by the patient's own body fluids. The effects of the different methods of transfusion and of injection of gum acacia on blood volume were observed. No differences were apparent. It was found that transfusion and gum injections only partially restored the blood volume. Forced fluids by mouth were found to bring about its complete restoration in a comparatively short time. It was observed that the organism did not restore its blood volume beyond a certain point when a further increase in it would, by dilution, have brought the hemoglobin per cent to a very low figure. In such cases a further increase of the blood volume occurred only when the hemoglobin rose. In cases with a low hemoglobin per cent as the result of a restoration of the blood bulk an abnormally high blood pressure appeared, which continued until the hemoglobin per cent again increased. Accompanying the low blood pressure seen shortly after hemorrhage was a well marked difference in hemoglobin per cent between capillary and venous blood, with a relative concentration on the capillary side. As compensation occurred and blood pressure rose this difference lessened until the two readings were identical, indicating an even redistribution of the red blood cells. Reticulated red cell counts made in these cases showed that a marked bone marrow stimulation occurs after hemorrhage. However, except in the very anemic cases the degree of increased blood production seemed to depend largely on the restoration of the blood volume. The patients who were put on forced fluids, with consequent rapid restoration of blood volume, showed a much higher per cent of reticulated cells than those in whom no attempt was made to increase the amount of fluid in circulation.

Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized, and...
 01:10
Veins as Blood Reservoirs
 01:22
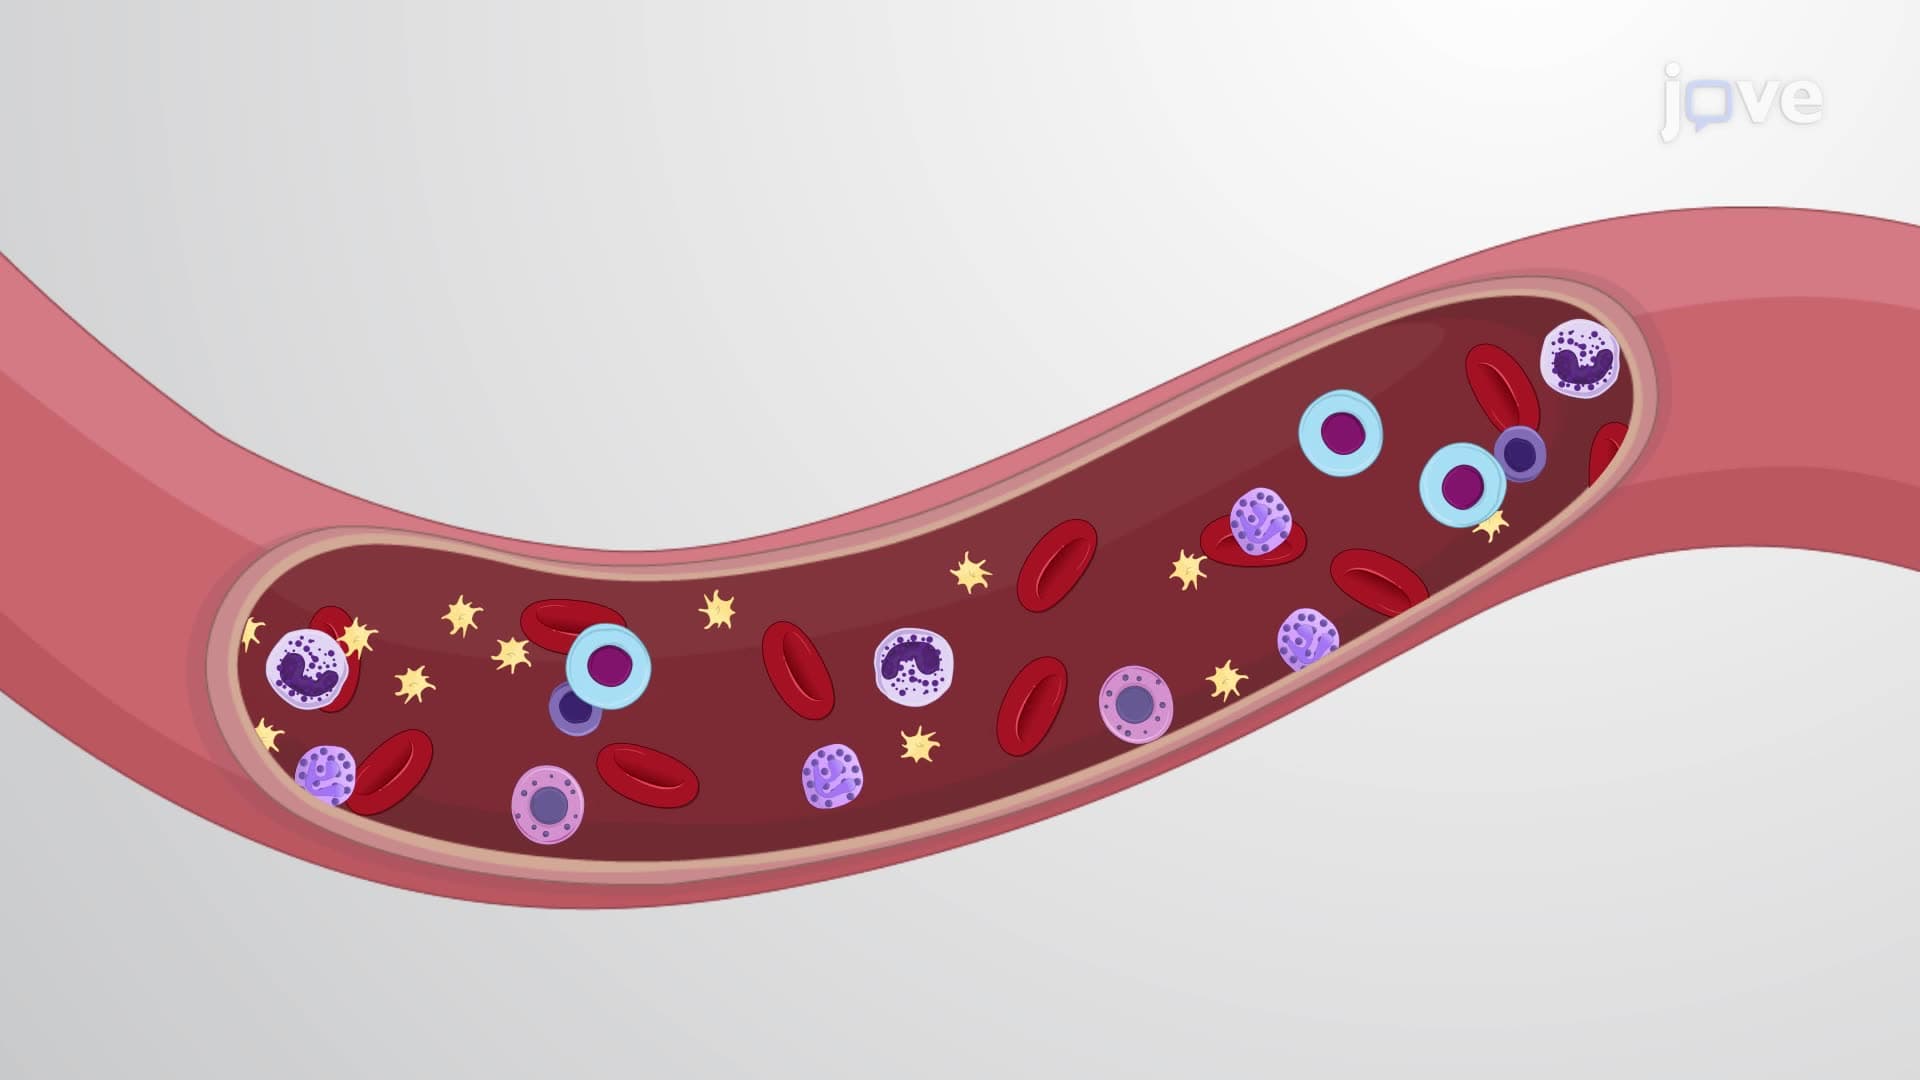
Composition of Blood
Formed elements constitute the remaining 45% of the blood volume. These...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...