Related Experiment Video
Updated: Apr 23, 2026


How to Administer Near-Infrared Spectroscopy in Critically ill Neonates, Infants, and Children
Published on: August 19, 2020
Incidence of propofol-related infusion syndrome in critically ill adults: a prospective, multicenter study
Russel J Roberts1, Jeffrey F Barletta, Jeffrey J Fong
1Department of Pharmacy, Tufts Medical Center, Boston, MA 02111, USA. rroberts@tuftsmedicalcenter.org

Introduction:
While propofol is associated with an infusion syndrome (PRIS) that may cause death, the incidence of PRIS is unknown. Determining the incidence of PRIS and the frequency of PRIS-related clinical manifestations are key steps prior to the completion of any controlled studies investigating PRIS. This prospective, multicenter study sought to determine the incidence of PRIS and PRIS-related clinical manifestations in a large cohort of critically ill adults prescribed propofol.
Methods:
Critically ill adults from 11 academic medical centers administered an infusion of propofol for [>or=] 24 hours were monitored at baseline and then on a daily basis until propofol was discontinued for the presence of 11 different PRIS-associated clinical manifestations and risk factors derived from 83 published case reports of PRIS.
Results:
Among 1017 patients [medical (35%), neurosurgical (25%)], PRIS (defined as metabolic acidosis plus cardiac dysfunction and [>or=] 1 of: rhabdomyolysis, hypertriglyceridemia or renal failure occurring after the start of propofol therapy) developed in 11 (1.1%) patients an average of 3 (1-6) [median (range)] days after the start of propofol. While most (91%) of the patients who developed PRIS were receiving a vasopressor (80% initiated after the start of propofol therapy), few received a propofol dose >83 mcg/kg/min (18%) or died (18%). Compared to the 1006 patients who did not develop PRIS, the APACHE II score (25 +/- 6 vs 20 +/- 7, P = 0.01) was greater in patients with PRIS but both the duration of propofol use (P = 0.43) and ICU length of stay (P = 0.82) were similar.
Conclusions:
Despite using a conservative definition for PRIS, and only considering new-onset PRIS clinical manifestations, the incidence of PRIS slightly exceeds 1%. Future controlled studies focusing on evaluating whether propofol manifests the derangements of critical illness more frequently than other sedatives will need to be large. These studies should also investigate the mechanism(s) and risk factors for PRIS.
More Related Videos
 09:36
Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
 07:15
Preoxygenation Techniques for Tracheal Intubation in Critically Ill Adults Utilizing Oxygen Mask and Noninvasive Ventilation
Published on: December 5, 2025
Related Concept Videos
 01:24
Parenteral Anesthetics: Overview
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:28
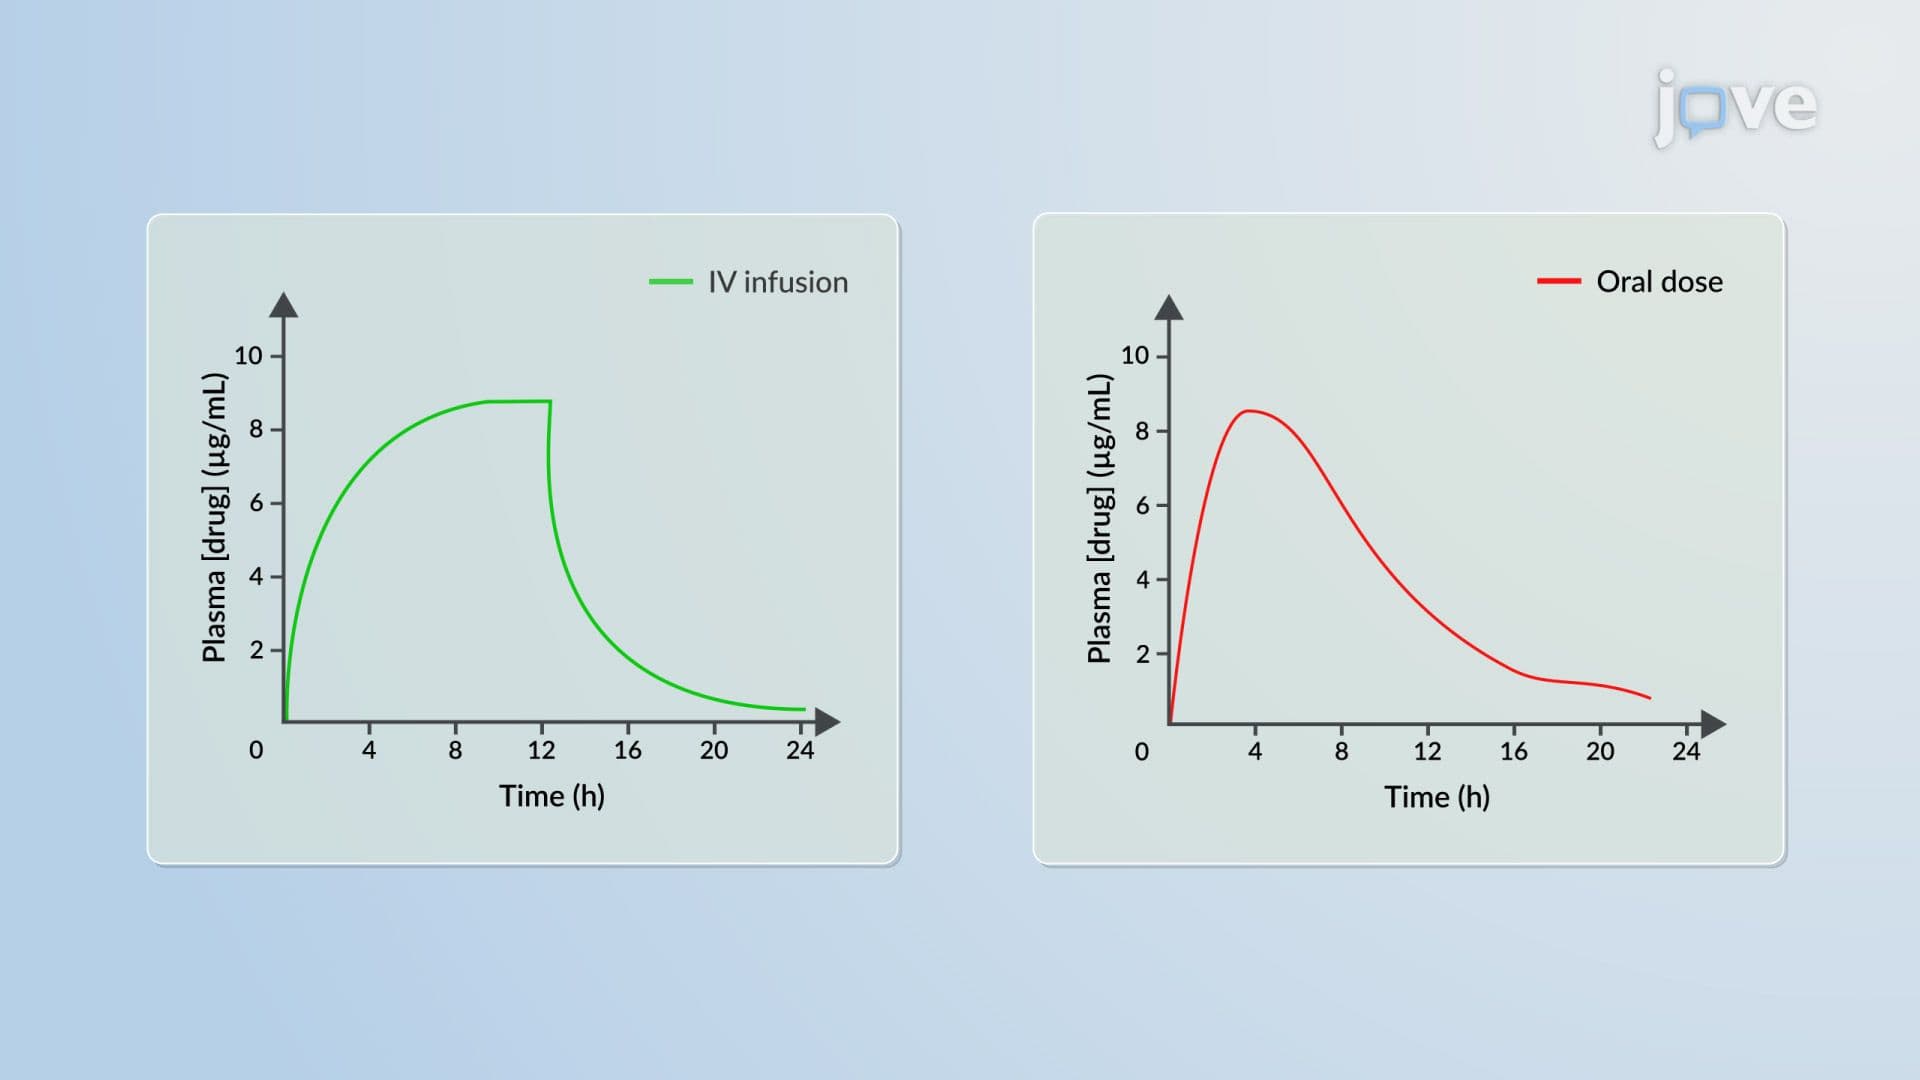
IV Infusion to Oral Dosing: Conversion Methods
 01:26
Pharmaceutical Poisoning: Potential Scenarios
 01:28
Acute Coronary Syndrome IV: Interprofessional Care