Related Experiment Video
Updated: Jun 19, 2026
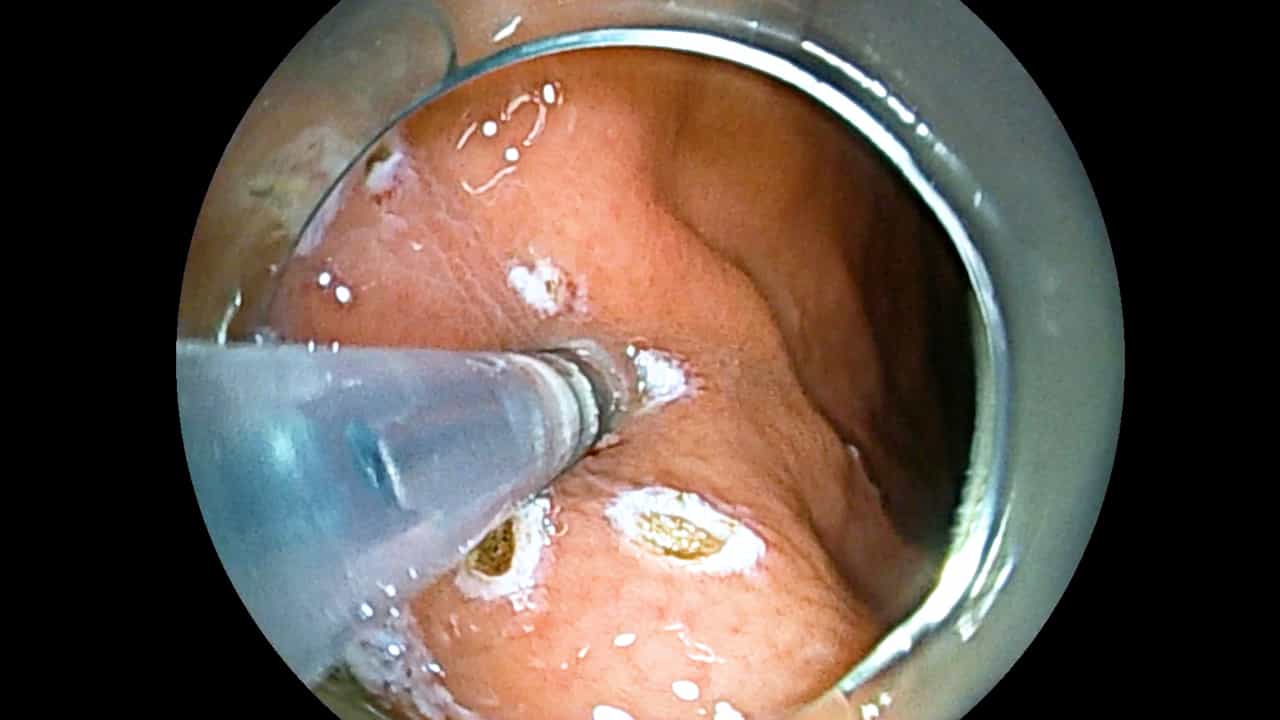
Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Risk factors for immediate and delayed bleeding associated with endoscopic submucosal dissection of gastric
Jin Seok Jang1, Seok Reyol Choi, David Y Graham
1Department of Internal Medicine, Dong-A Medical Center, University College of Medicine, Busan, Korea.

Abstract:
OBJECTIVE. Endoscopic submucosal dissection (ESD) of gastric neoplasia has been reported to have a higher bleeding rate than conventional endoscopic mucosal resection (EMR). The aim of this study was to identify the risk factors for bleeding associated with ESD. MATERIAL AND METHODS. The records of consecutive patients who underwent ESD for gastric adenoma/early gastric cancer were reviewed. Potential risk factors included patient age, lesion size, gross findings, location, and histology of the tumor. The primary end-point was the incidence of immediate or delayed bleeding related to ESD. RESULTS. A total of 144 patients were studied; bleeding occurred in 32 cases (22.2%) with immediate bleeding in 29 cases. Delayed bleeding (3 cases) occurred at day 2 (2 patients) and at day 7 in 1 patient. In all cases of immediate bleeding, immediate hemostatic therapy was successful. The histology of tumor was the only factor that was statistically significantly associated with bleeding (adjusted hazard ratio 6.770, 95% confidence interval 1.830-25.048, p=0.004). CONCLUSIONS. The only factor that correlated with an increased risk of bleeding with ESD was the presence of gastric malignancy. We found no factor that would, prospectively, be amenable to prevention of bleeding.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:25
Peptic Ulcer Disease I: Introduction