Recent changes in the landscape of combination RAS blockade
Related Experiment Video
Updated: Jun 18, 2026

Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
Benjamin J Epstein1, Steven M Smith, Rushab Choksi
1Department of Pharmacotherapy, University of Florida, FL, USA.

Abstract:
The renin-angiotensin system (RAS) is a prime target for cardiovascular drug therapy. Inhibition of the RAS lowers blood pressure and confers protection against cardiovascular and renal events. These latter benefits cannot be entirely attributed to blood pressure lowering. Angiotensin-converting enzyme (ACE)-inhibitors and angiotensin receptor blockers (ARBs) have been studied extensively and, while there is irrefutable evidence that these agents mitigate the risk for cardiovascular and renal events, their protection is incomplete. In outcomes studies that have employed ACE-inhibitors or ARBs there has been a relatively high residual event rate in the treatment arm and this has been ascribed, by some, to the fact that neither ACE-inhibitors nor ARBs completely repress RAS. For this reason, combined RAS blockade with an ACE-inhibitor and ARB has emerged as a therapeutic option. In hypertension, combined RAS blockade elicits only a marginal incremental drop in blood pressure and it does not further lower the risk for cardiovascular events. In chronic heart failure and proteinuric renal disease, combining these agents in carefully selected patients is associated with a reduction in clinical events. Irrespective of the setting, dual RAS blockade is associated with an increase in the risk for adverse events, primarily hyperkalemia and worsening renal function. The emergence of the direct renin inhibitor, aliskiren, has afforded clinicians a new strategy for RAS blockade. Renin system blockade with aliskiren plus another RAS agent is the subject of ongoing large-scale clinical trials and early studies suggest promise for this strategy. Currently, combined RAS blockade with an ACE-inhibitor and an ARB should not be routinely employed for hypertension; however, the combination of an ACE-inhibitor or ARB with aliskiren might be considered in some patients given the more formidable blood pressure-lowering profile of this regimen. In carefully selected patients with heart failure or kidney disease, combination therapy with two RAS inhibitors should be considered.
Related Concept Videos
 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:08
Antiepileptic Drugs: Sodium Channel Blockers
Sodium channel blockers modulate ion channels, particularly voltage-gated sodium channels. They block only sodium ion movement.
Among the most commonly prescribed antiepileptic drugs are...
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
 01:30
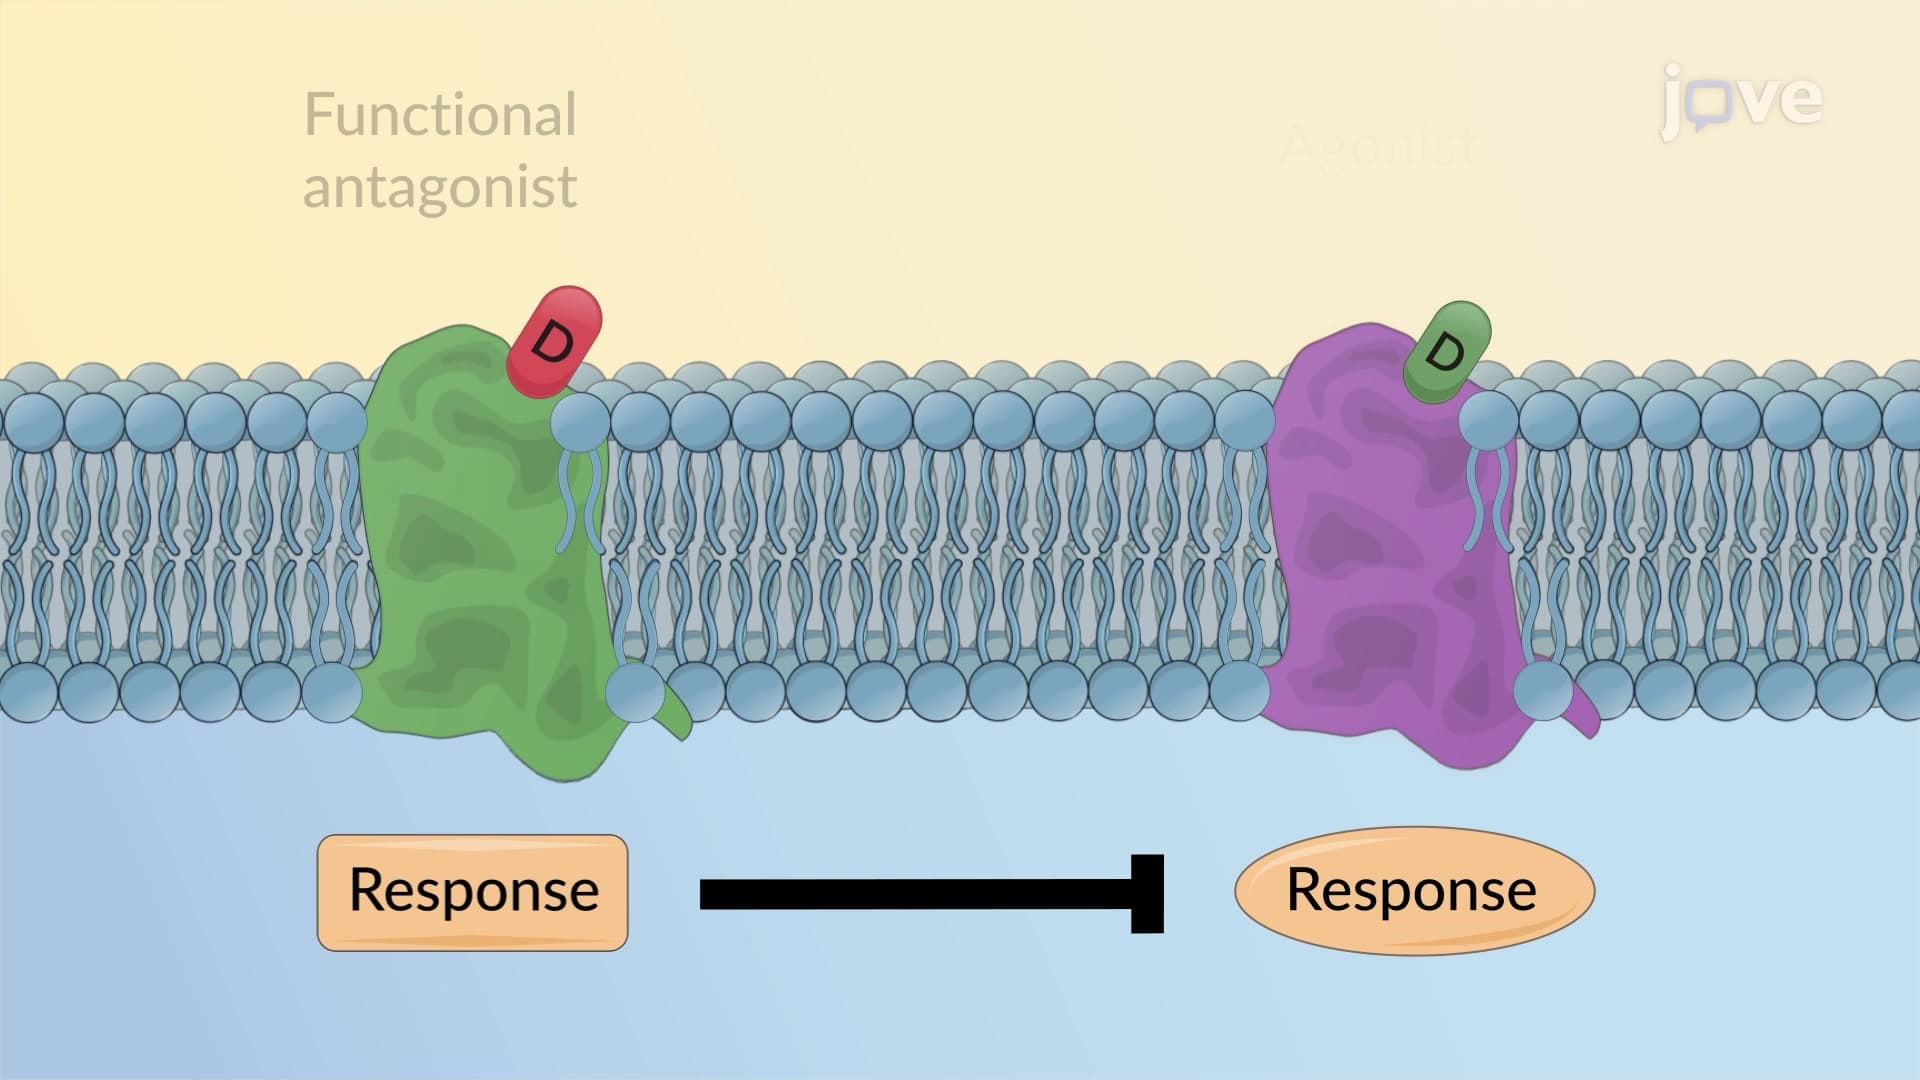
Combined Effects of Drugs: Antagonism
The most common type is receptor antagonism, where one drug acts as an antagonist to block the effects of another drug by...