Association of lower plasma fetuin-a levels with peripheral arterial disease in type 2 diabetes

Luis H Eraso1, Naeema Ginwala, Atif N Qasim

  • 1Cardiovascular Institute, University of Pennsylvania School of Medicine, Philadelphia, Pennsylvania, USA. muredach@mail.med.upenn.edu

Diabetes Care
|November 14, 2009
PubMed
Abstract

Related Concept Videos

Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation01:21

Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation

Clinical manifestationsPeripheral Arterial Disease (PAD) manifests through a range of symptoms, from the characteristic intermittent claudication to atypical presentations and severe complications in advanced stages. Intermittent claudication, a hallmark symptom of PAD, presents as exercise-induced muscle pain that typically resolves within minutes of rest. This pain is reproducible and stems from inadequate blood flow, leading to the accumulation of lactic acid produced during anaerobic...
Peripheral Artery Disease I: Introduction01:30

Peripheral Artery Disease I: Introduction

Peripheral artery disease (PAD) predominantly results from atherosclerosis, which involves the accumulation of fatty deposits, or plaques, within the walls of arteries. This causes them to narrow and harden, significantly reducing blood flow. PAD predominantly affects the legs, particularly the arteries supplying the thighs and calves. In rare cases, it may involve other arteries, including those in the arms.Etiology of PAD:The principal cause of PAD is atherosclerosis, which results from fatty...
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis01:25

Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis

Type 2 diabetes mellitus develops gradually and is often asymptomatic in early stages.Clinical ManifestationsWhen symptoms appear, they include fatigue, blurred vision, pruritus, delayed wound healing, and recurrent infections, particularly candidal infections. Peripheral neuropathy may present as numbness or tingling in the extremities. Classic hyperglycemia symptoms—polyuria, polydipsia, and polyphagia—are less common. Most patients are overweight and frequently have associated hypertension...
Type II Diabetes II: Pathophysiology01:24

Type II Diabetes II: Pathophysiology

PathophysiologyType 2 diabetes mellitus (T2DM ) is a chronic metabolic disorder characterized by insulin resistance and progressive pancreatic β-cell dysfunction, leading to impaired glucose homeostasis. It results from interactions among genetic predisposition, environmental factors, and metabolic stressors, such as overnutrition and a sedentary lifestyle.Insulin Resistance and Glucose DysregulationEarly T2DM involves insulin resistance in skeletal muscle, adipose tissue, and the liver.
Type I Diabetes II: Pathophysiology01:26

Type I Diabetes II: Pathophysiology
Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular uptake of...
Diabetic Foot Ulcer01:31

Diabetic Foot Ulcer

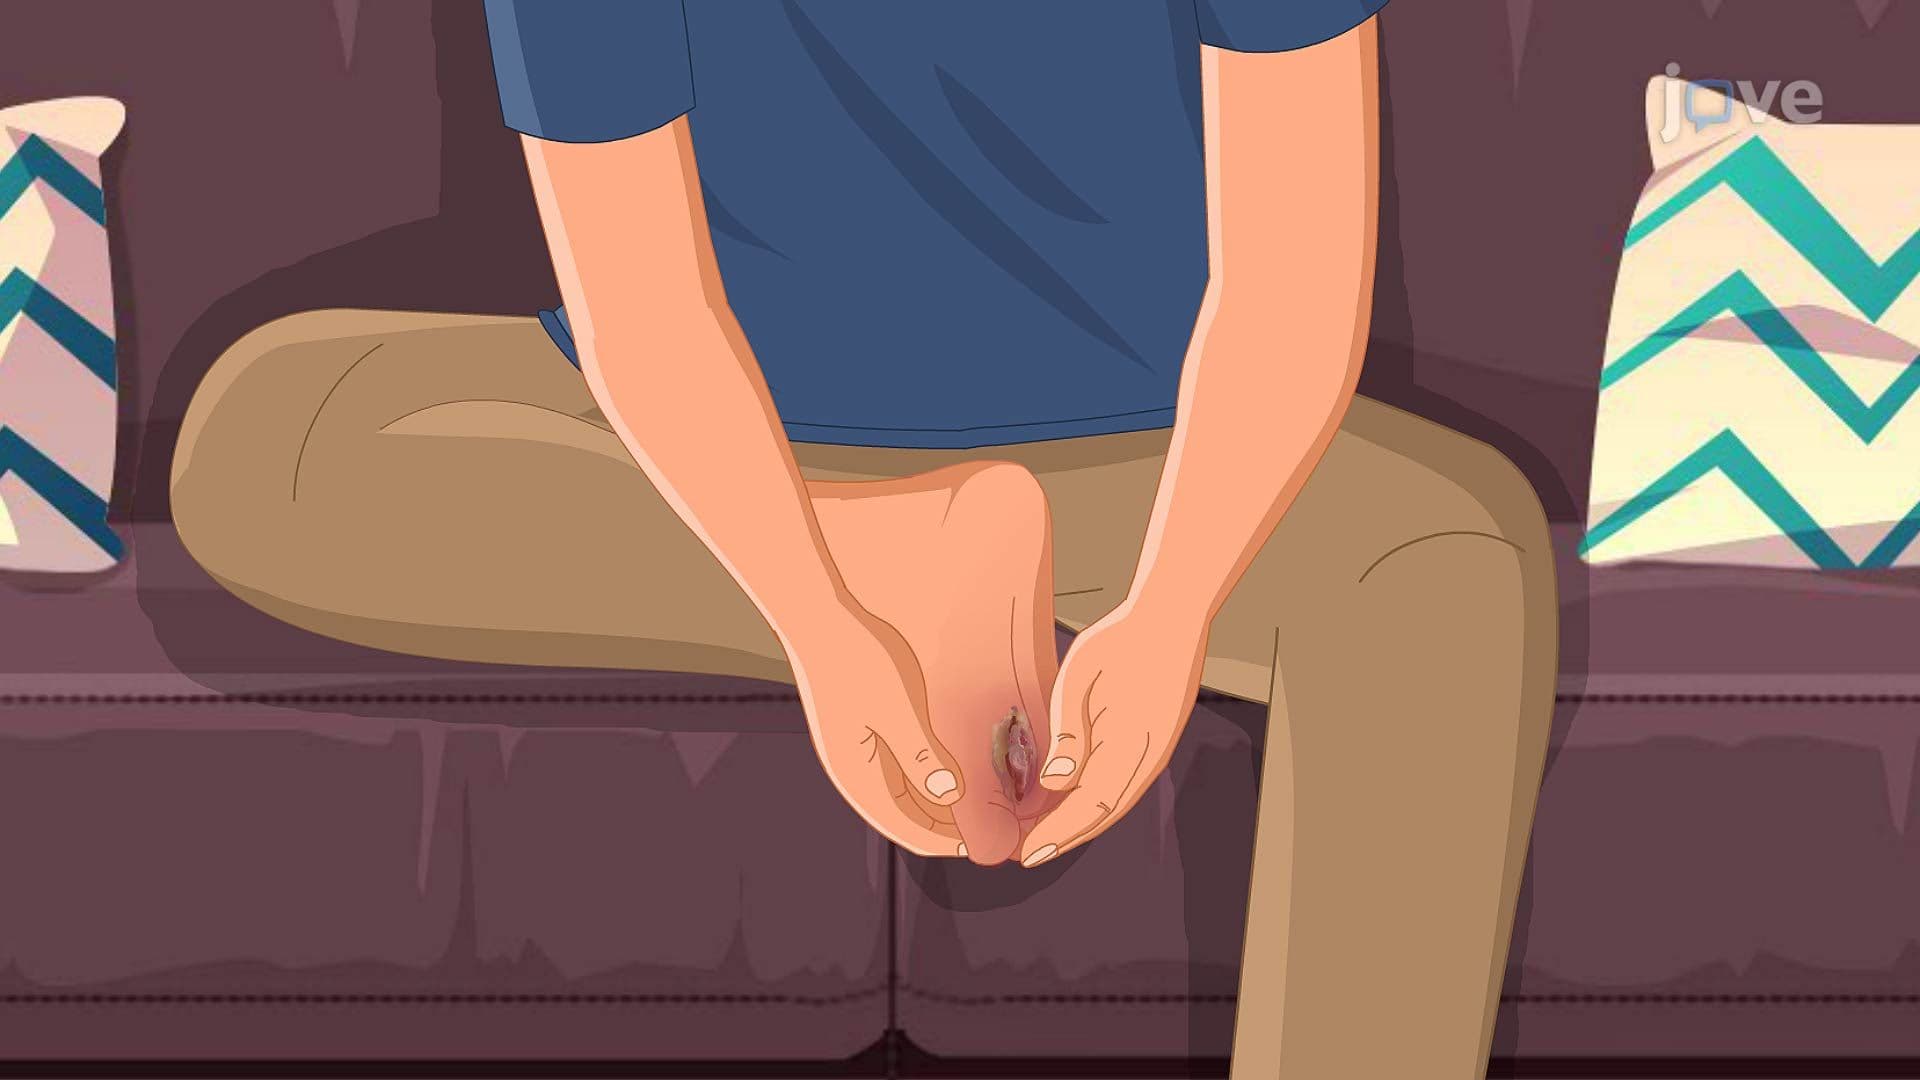
Definition A diabetic foot ulcer (DFU) is a chronic, non-healing wound that develops in individuals with diabetes. It typically occurs on pressure-bearing areas such as the heel, metatarsal heads, or hallux, and carries a high risk of infection and amputation.Pathophysiology • The development of DFUs can be explained by four interconnected mechanisms: neuropathy, ischemia, infection, and impaired wound healing. • Neuropathy is the most common factor. Sensory neuropathy reduces pain perception,...
