Related Experiment Video
Updated: Jun 18, 2026

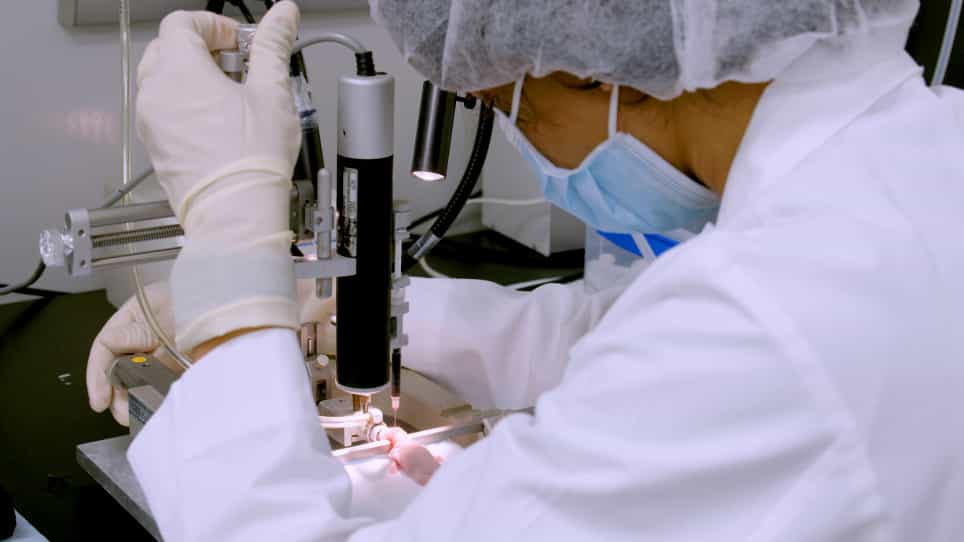
Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
Intracranial hemorrhage in the preterm infant: understanding it, preventing it
1Pediatric Neurology Unit, Neonatal Neurology Service, Dana Children's Hospital, Tel Aviv Sourasky Medical Center, Sackler Faculty of Medicine, Tel Aviv University, 6 Weizman Street, Tel Aviv 64239, Israel. bassan@post.tau.ac.il

Insights
New advances in neonatal imaging and understanding of inflammatory and genetic factors offer innovative ways to detect and prevent intracranial hemorrhage (ICH) in preterm infants. This review covers ICH mechanisms, diagnosis, outcomes, and management, including cerebellar hemorrhage.
Area of Science:
- Neonatal neurology
- Pediatric neurosurgery
- Perinatal medicine
Background:
- Intracranial hemorrhage (ICH) is a significant concern in preterm infants.
- Advances in neonatal imaging, cerebral monitoring, and hemodynamics are improving detection.
- Enhanced understanding of inflammatory and genetic factors is crucial for prevention.
Purpose of the Study:
- To review current knowledge on the mechanisms, diagnosis, outcome, and management of preterm ICH.
- To explore the origins and development of ICH in preterm infants.
- To discuss future directions and expectations in the field.
Main Methods:
- Comprehensive literature review of recent discoveries.
- Analysis of current diagnostic and monitoring techniques.
- Synthesis of information on inflammatory and genetic mechanisms.
Main Results:
- New discoveries facilitate innovative early detection and prevention strategies for preterm ICH.
- The spectrum of ICH, including germinal matrix intraventricular hemorrhage and cerebellar hemorrhage, is detailed.
- Complications and associated phenomena of preterm ICH are discussed.
Conclusions:
- Continued research into mechanisms and genetics is vital for improved outcomes.
- Multidisciplinary approaches are essential for managing preterm ICH effectively.
- Future expectations focus on enhanced prevention and treatment strategies.
Abstract:
New discoveries in neonatal imaging, cerebral monitoring, and hemodynamics, and greater understanding of inflammatory and genetic mechanisms involved in intracranial hemorrhage (ICH) in the preterm infant are creating opportunities for innovative early detection and prevention approaches. This article covers the spectrum of ICH in the preterm infant, including germinal matrix intraventricular hemorrhage, its complications, and associated phenomena, such as the emerging role of cerebellar hemorrhage. The overall aim of this article is to review the current knowledge of the mechanisms, diagnosis, outcome, and management of preterm ICH; to revisit the origins from which they develop; and to discuss future expectations.
More Related Videos

Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:14
Increased Intracranial Pressure l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:15
Ischemic Stroke ll: Pathophysiology