Related Experiment Video
Updated: Jun 18, 2026

Receptor Autoradiography Protocol for the Localized Visualization of Angiotensin II Receptors
Published on: June 7, 2016
[Expression of angiotensin II receptor subtypes in atrial fibrillation underlying rheumatic heart disease]
Hua Jiang1, Li-Jun Ma, Hong-Liang Cong
1Department of Cardiology, Tianjin Chest Hospital, Tianjin Cardiology Research Institute, Tianjin 300051, China.

Objective:
To examine the expression of angiotensin II (Ang II) receptor subtypes in human left and right atrial tissue in atrial fibrillation underlying rheumatic heart disease.
Methods:
Atrial tissue samples were obtained from 39 patients with rheumatic heart disease, 25 with atrial fibrillation (AF) and 14 with sinus rhythm(SR) during open heart surgery. AT1 and AT2 mRNA levels were measured with semi-quantitative reverse transcription polymerase chain reaction techniques. AT1 and AT2 protein levels were measured with immunohistochemical techniques.
Results:
Compared with that of the SR group, left atrial inner diameter was significantly increased in the patients of the AF group. The AT1 mRNA and protein levels in the LA significantly increased in patients with AF compared with those in patients with SR (P < 0.05), whereas AT2 mRNA and protein were not significantly altered. Investigations of Ang II receptor subtypes' mRNA and protein levels in the RA did not exhibit any significant changes either in AT1 or AT2 in patients with AF and SR.
Conclusions:
AF is associated with an up-regulation of AT1 in LA, but does not appear to influence the AT2 expression. This may indicate a possible pathophysiologic role for renin-angiotensin system in the development of AF. The series of effects mediated by AT1 activation may be one of the molecular mechanisms involved in the process of atrial remodeling.


Related Concept Videos
 01:23
Rheumatic Heart Disease I: Introduction
 01:30
Antihypertensive Drugs: Angiotensin II Receptor Blockers
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:31
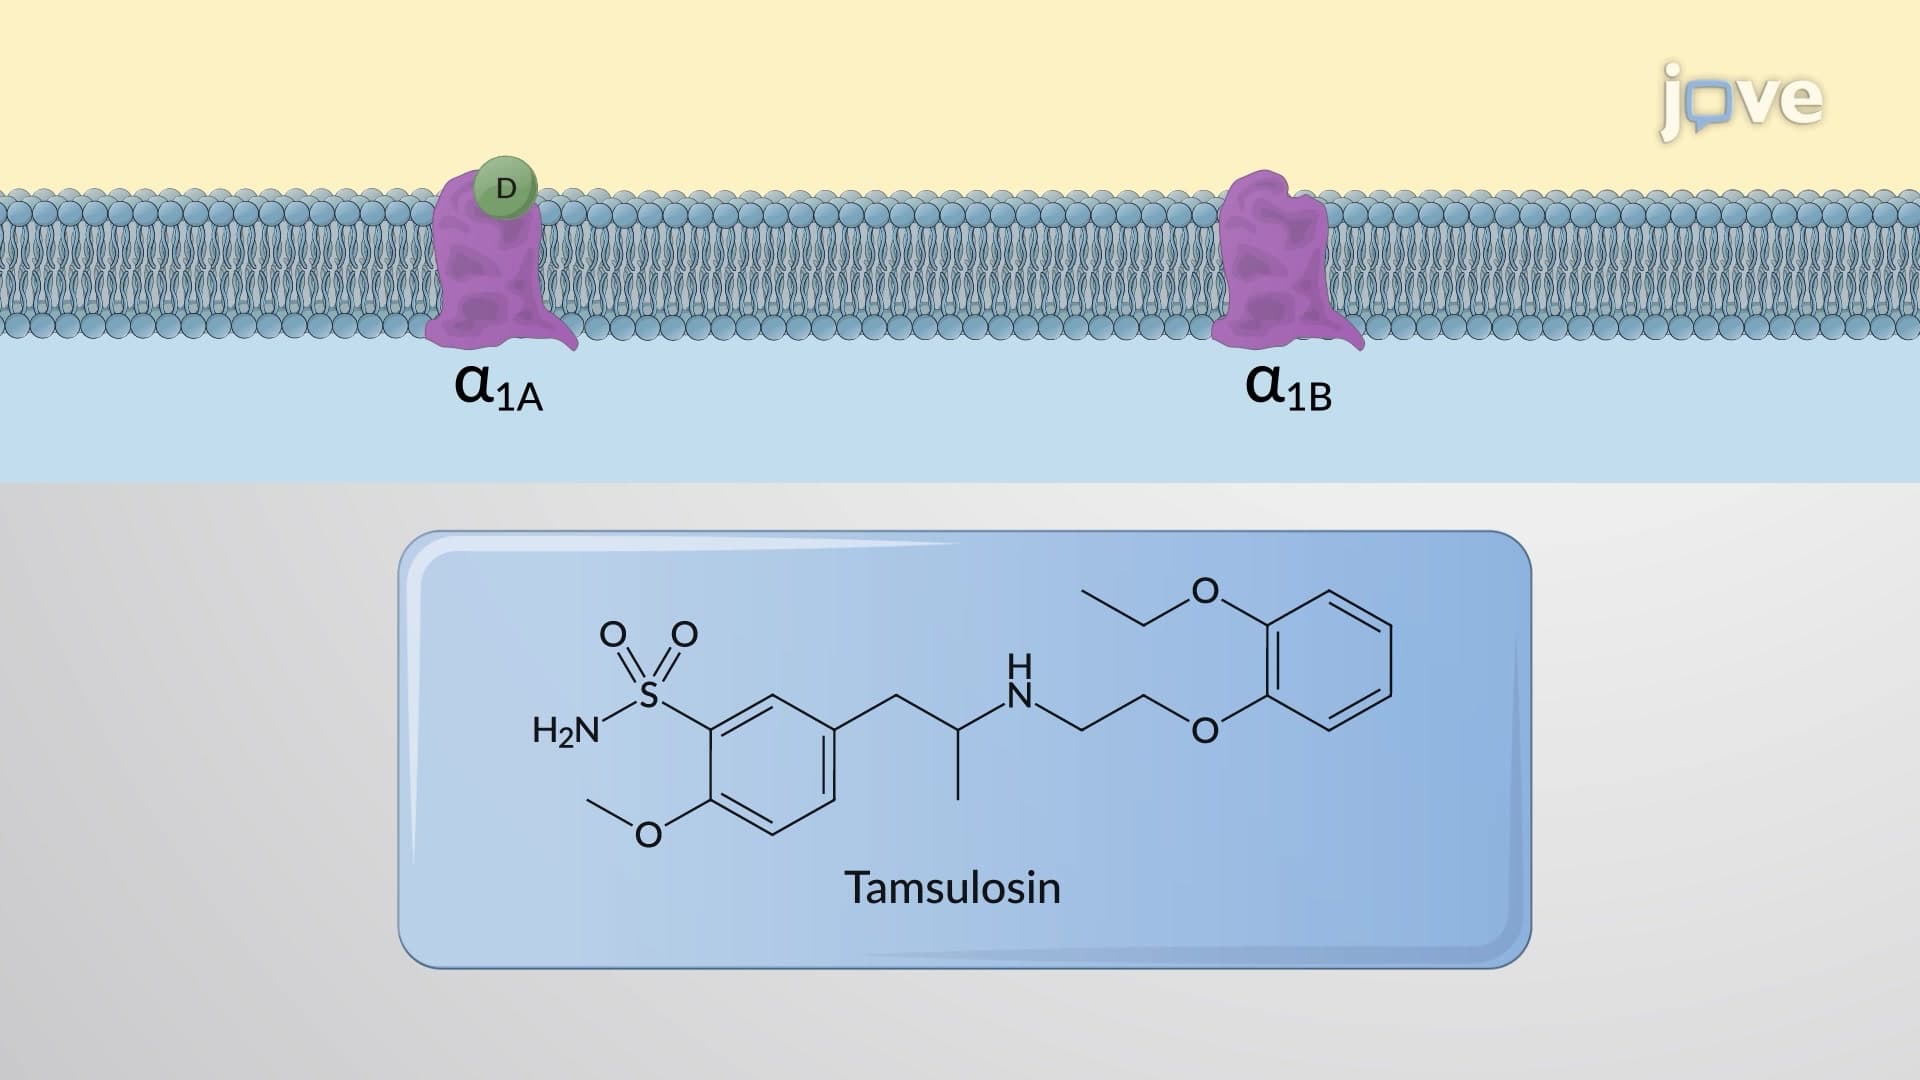
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:29
Heart Failure II: Pathophysiology