Related Experiment Video
Updated: Jun 18, 2026

Intraportal Transplantation of Pancreatic Islets in Mouse Model
Published on: May 5, 2018
Extreme subcutaneous, intramuscular and inhaled insulin resistance treated by pancreas transplantation alone
J R Sa1, M A Alvarenga, E B Rangel
1Endocrinology Division, Department of Medicine, Federal University of Sao Paulo, and Hospital Infantil Darcy Vargas, São Paulo, Brazil. jrsa@uol.com.br

Diabetes mellitus with resistance to insulin administered subcutaneously or intramuscularly (DRIASM) is a rare syndrome and is usually treated with continuous intravenous insulin infusion. We present here two cases of DRIASM in 16 and 18 years female patients that were submitted to pancreas transplantation alone (PTA). Both were diagnosed with type 1 diabetes as young children and had labile glycemic control with recurrent episodes of diabetic ketoacidosis. They had prolonged periods of hospitalization and complications related to their central venous access. Exocrine and endocrine drainages were in the bladder and systemic, respectively. Both presented immediate graft function. In patient 1, enteric conversion was necessary due to reflux pancreatitis. Patient 2 developed mild postoperative hyperglycemia in spite of having normal pancreas allograft biopsy and that was attributed to her immunosuppressive regimen. Patient 1 died 9 months after PTA from septic shock related to pneumonia. In 8 months of follow-up, Patient 2 presented optimal glycemic control without the use of antidiabetic agents. In conclusion, PTA may be an alternative treatment for DRIASM patients.
Diabetes mellitus with resistance to insulin administered subcutaneously or intramuscularly (DRIASM) is a rare syndrome and is usually treated with continuous intravenous insulin infusion. We present here two cases of DRIASM in 16 and 18 years female patients that were submitted to pancreas transplantation alone (PTA). Both were diagnosed with type 1 diabetes as young children and had labile glycemic control with recurrent episodes of diabetic ketoacidosis. They had prolonged periods of hospitalization and complications related to their central venous access. Exocrine and endocrine drainages were in the bladder and systemic, respectively. Both presented immediate graft function. In patient 1, enteric conversion was necessary due to reflux pancreatitis. Patient 2 developed mild postoperative hyperglycemia in spite of having normal pancreas allograft biopsy and that was attributed to her immunosuppressive regimen. Patient 1 died 9 months after PTA from septic shock related to pneumonia. In 8 months of follow-up, Patient 2 presented optimal glycemic control without the use of antidiabetic agents. In conclusion, PTA may be an alternative treatment for DRIASM patients.

Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:25
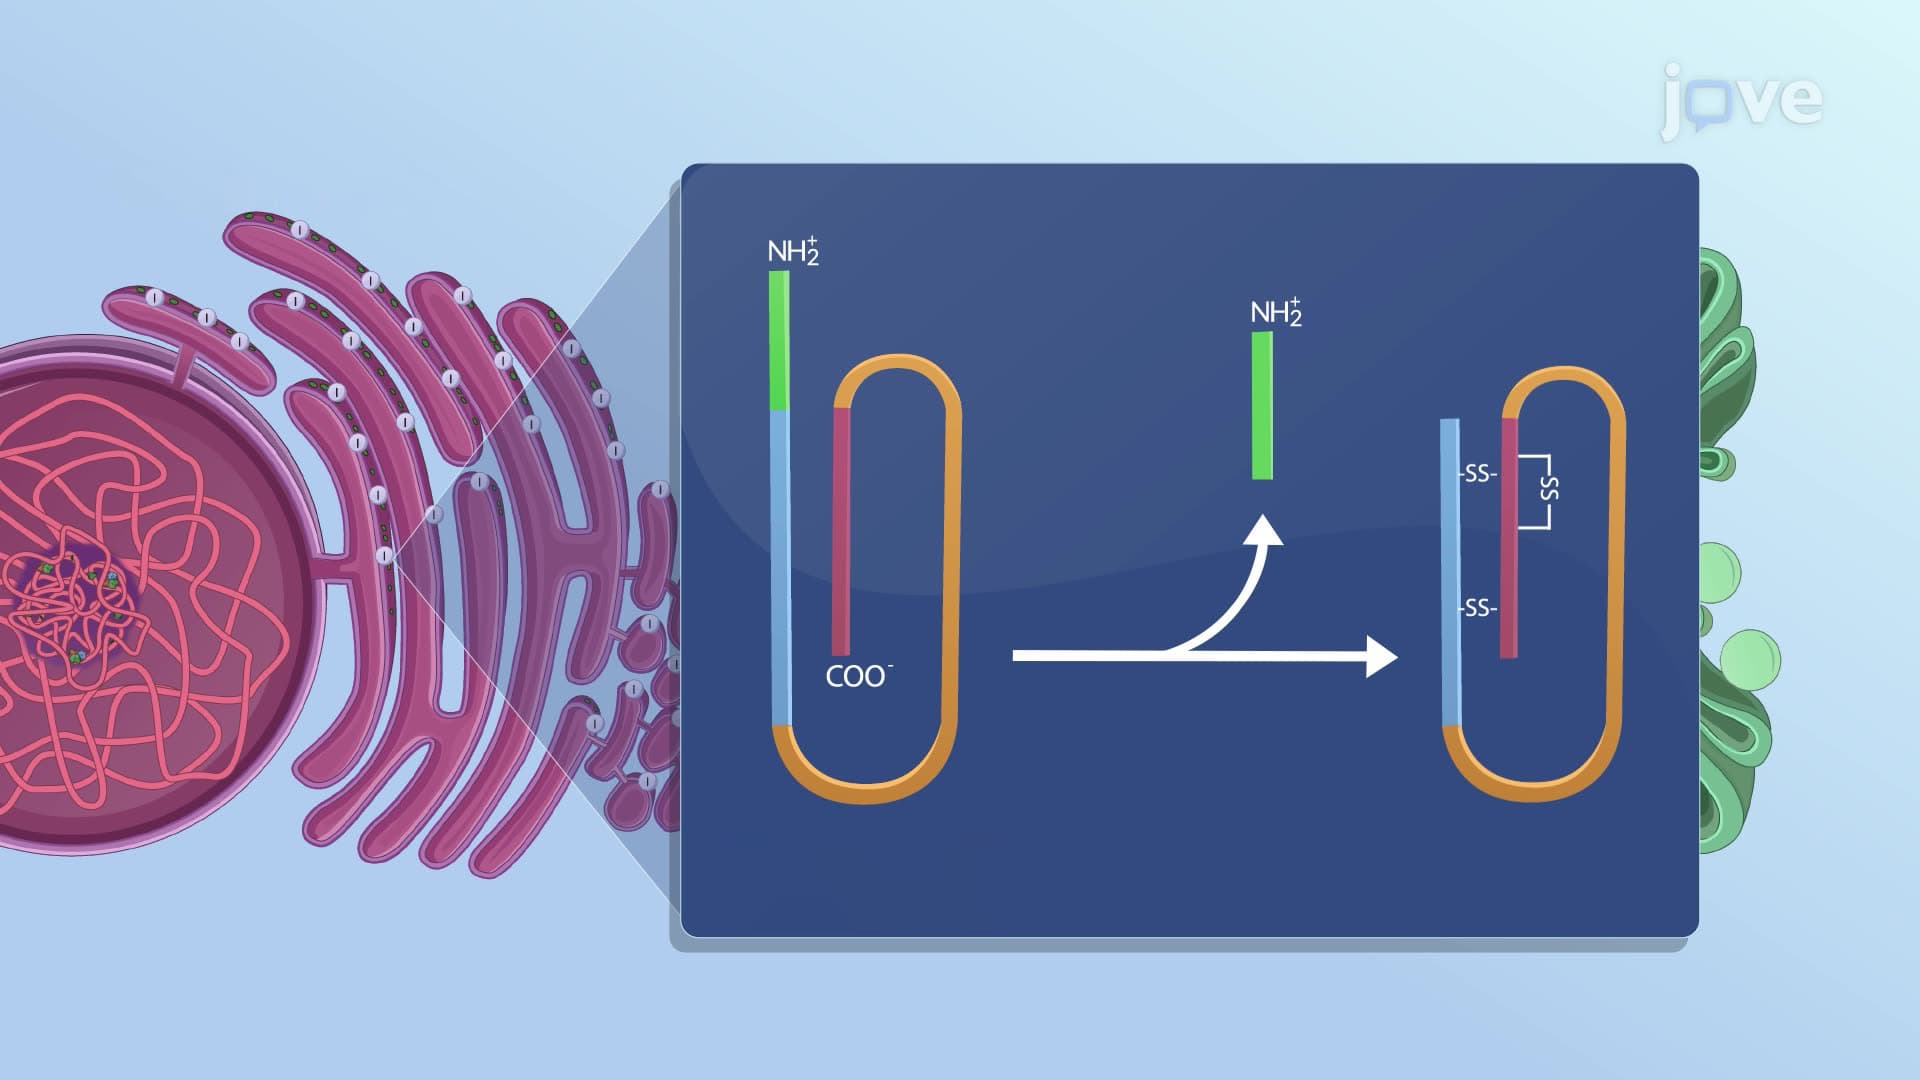
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:26
Type I Diabetes II: Pathophysiology
 01:12
Type I Diabetes I: Introduction
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...