Related Experiment Video
Updated: Jun 18, 2026
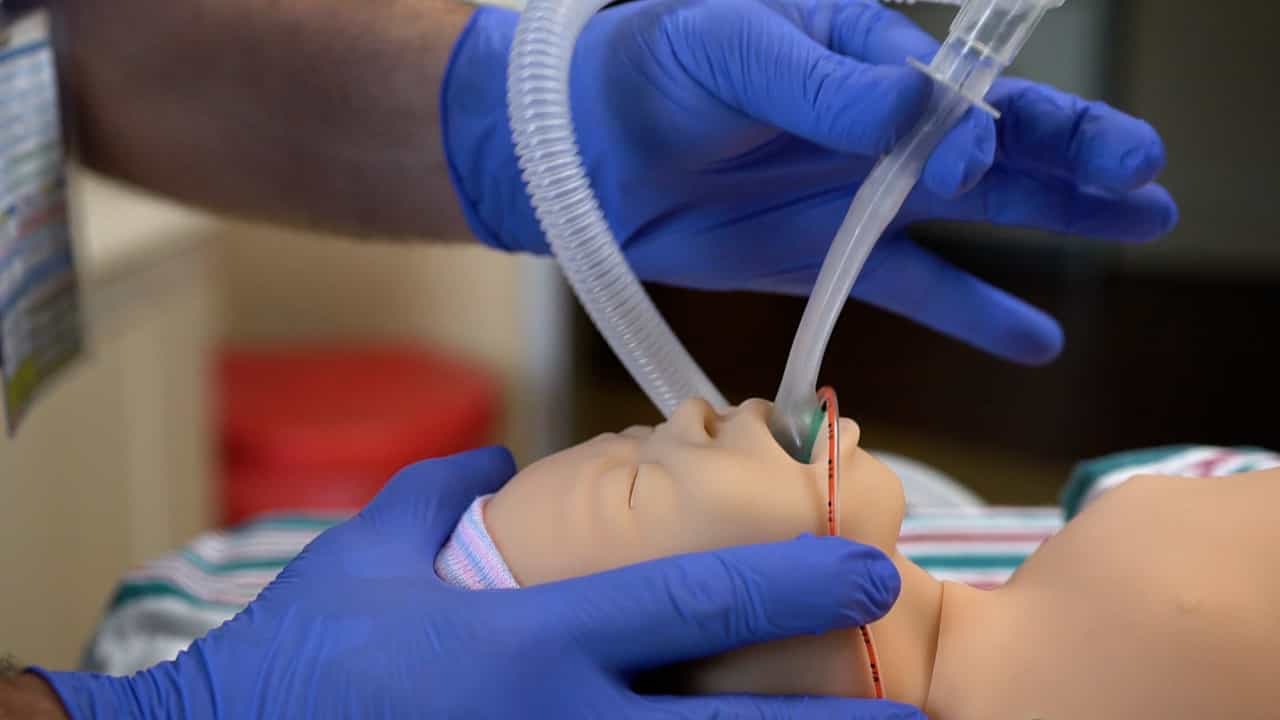
Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
Sleep disordered breathing in infants with Prader-Willi syndrome during the first 6 weeks of growth hormone therapy:
Jennifer L Miller1, Jonathan Shuster, Douglas Theriaque
1Department of Pediatrics, University of Florida, College of Medicine, Gainesville, FL 32610-0296, USA. millejl@peds.ufl.edu

Insights
Growth hormone therapy did not significantly impact sleep-related breathing in infants with Prader-Willi syndrome (PWS). However, infants with respiratory infections or reflux may experience more obstructive events during treatment.
Area of Science:
- Pediatric Endocrinology
- Sleep Medicine
- Genetics
Background:
- Sleep-related breathing disorders are prevalent in Prader-Willi syndrome (PWS).
- Growth hormone (GH) therapy is increasingly used in infants with PWS, but its respiratory effects are unknown.
- This study addresses the lack of data on GH's impact on infant PWS respiratory health.
Purpose of the Study:
- To evaluate the respiratory effects of growth hormone therapy in infants with Prader-Willi syndrome.
- To assess changes in sleep-related breathing using overnight polysomnography.
- To determine if GH impacts apnea and hypopnea events in this population.
Main Methods:
- A pilot study involving 20 infants (2-21 months) with genetically confirmed PWS.
- Overnight polysomnography was conducted before and 6 weeks after initiating GH therapy (1 mg/m²/day).
- Analysis focused on obstructive/central apnea, hypopnea events, and the apnea-hypopnea index.
Main Results:
- Overall, GH therapy showed no significant changes in sleep-related breathing disorders.
- A subset of 12 infants experienced increased obstructive events, linked to concurrent upper respiratory infections or gastroesophageal reflux.
- Resolution of these conditions led to normalized polysomnography findings.
Conclusions:
- Growth hormone therapy itself does not significantly affect sleep-related breathing in infants with PWS.
- Infants with PWS undergoing GH therapy are at increased risk for obstructive events if they have concurrent respiratory infections or reflux.
- Close monitoring is recommended for infants with PWS starting GH therapy, particularly those with infections.
Background:
Sleep-related breathing disorders are common in individuals with Prader-Willi syndrome (PWS). The US Food and Drug Administration approved the use of growth hormone in PWS in 2000. Many infants with PWS are being started on growth hormone therapy, but no data exist on the respiratory effects of growth hormone treatment in this age group.
Study Objectives:
To perform overnight polysomnographic studies to evaluate the effects of growth hormone on sleep-related breathing in infants with PWS.
Methods:
Pilot study evaluating overnight polysomnography before and 6 weeks after initiation of growth hormone therapy at a dose of 1 mg/m2 per day in 20 infants from 2 to 21 months of age with genetically confirmed PWS. Polysomnography results were analyzed for frequency and severity of obstructive and central apnea and hypopnea events and the overall apnea-hypopnea index.
Results:
When data were analyzed for the total group, there were no significant changes in sleep-related disorders before and after institution of growth hormone therapy. However, 12 infants had an increase in the frequency of obstructive events associated with either upper respiratory infections or a diagnosis of gastroesophageal reflux at the second sleep study (after institution of growth hormone therapy). Resolution of these conditions was associated with normalization of polysomnography results on follow-up studies.
Conclusions:
Overall, growth hormone therapy, per se, had no significant effect on sleep related-breathing disorders in infants with PWS. Infants with upper respiratory infections of gastroesophageal reflux may be at risk for developing more obstructive events after beginning growth hormone treatment. We recommend close monitoring of infants with PWS after they begin growth hormone therapy, especially when they have upper respiratory infections.