
Retrograde approach to chronic total occlusions: can septal vessels be used more than once?
Albert Alahmar1, Simon Redwood, Anthony Gershlick
1Cardiovascular Intervention Department, University Hospitals of Leicester, United Kingdom. ae.alahmar@gmail.com

Insights
Chronic total occlusions are a common challenge in cardiology. A new retrograde approach can be successful, but changes in septal collaterals may hinder repeat attempts.
Area of Science:
- Interventional Cardiology
- Vascular Biology
Background:
- Chronic total occlusions (CTO) represent a significant portion of coronary artery disease, posing challenges for interventional cardiologists.
- The retrograde approach has emerged as a valuable technique for CTO percutaneous coronary intervention (PCI), improving success rates in experienced hands.
Observation:
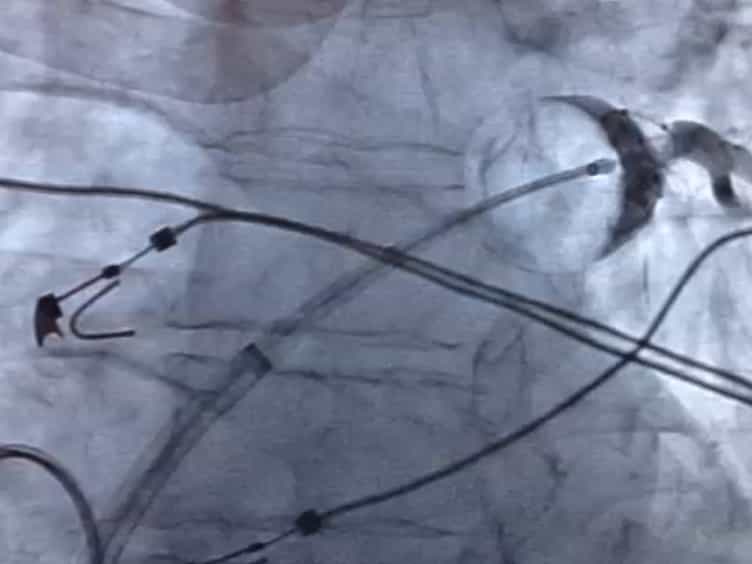
- The retrograde approach for CTO PCI may require multiple attempts and often utilizes septal collateral branches.
- Two cases are presented where a second retrograde attempt was unsuccessful due to altered septal collateral function.
Findings:
- Septal collateral pathways, previously patent for balloon passage, became impassable during a subsequent retrograde CTO PCI attempt.
- These changes in collateral anatomy or function can impede the feasibility of repeat retrograde interventions.
Implications:
- Clinicians should be aware of potential dynamic changes in collateral circulation during CTO interventions.
- Further research is needed to understand the mechanisms behind collateral alterations and to develop strategies to overcome such challenges in retrograde CTO PCI.
Abstract:
Chronic total occlusions constitute about one-third of all coronary artery lesions, and remains a significant challenge for the interventionist. Over the last few years, several new developments have emerged. The retrograde approach is one of those new developments and certainly, in experienced hands, has improved success rates significantly. This approach, however, often requires more than one attempt and potentially uses the same septal branch between the donor and the occluded artery. We present 2 cases where a second attempt at the retrograde approach was unsuccessful because of changes in the septal collateral, which having previously allowed passage of the balloon, failed to do so on the subsequent attempt.
