Related Experiment Video
Updated: Jun 17, 2026

An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
Review of clinical experience with estradiol in combined oral contraceptives
Franca Fruzzetti1, Johannes Bitzer
1Department of Obstetrics and Gynecology, Ospedale S. Chiara, 56100 Pisa, Italy. ffruzzi@tin.it

Abstract:
Previous attempts to replace ethinylestradiol (EE) with 17beta-estradiol (E2) in combined oral contraceptives (COCs) have proved unsatisfactory in terms of bleeding outcomes. A review of previous studies of E2-based COCs has shown that, despite good ovulation inhibition, bleeding irregularities affected up to 100% of women, often resulting in high rates of discontinuation (up to 42%). Suggested reasons for the bleeding irregularities observed with these predominantly monophasic estradiol-progestin preparations included suboptimal doses of E2 and an inappropriate estrogen/progestin ratio. The progestin used in the investigated formulations (e.g., norethisterone acetate, desogestrel and cyproterone acetate) may also have affected the overall bleeding profile. More recent studies of a multiphasic COC containing estradiol valerate (E2V) and dienogest (DNG) indicate efficient ovulation inhibition and acceptable cycle control. In a randomized, double-blind trial that compared E2V/DNG with a monophasic COC comprising EE/levonorgestrel (LNG), the occurrence of scheduled withdrawal bleeding per cycle with E2V/DNG and EE/LNG was 77.7-83.2% and 89.5-93.8%, respectively. The intensity and duration of withdrawal bleeding was reduced with E2V/DNG. The incidence of intracyclic bleeding was similar with E2V/DNG (10.5-18.6%) and EE/LNG (9.9-17.1%). This review shows that after several unsatisfactory attempts to develop E2-based COCs, more recent studies employing endometrial-focused progestins, e.g., DNG, and multiphasic dosing regimens appear to be a promising approach for an E2-based COC that provides efficient ovulation inhibition and acceptable cycle control.
Related Concept Videos
 01:22
Birth Control Methods
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:21
Intrauterine Drug Delivery Systems
 01:23
Oral Drug Delivery Systems: Introduction
 01:26
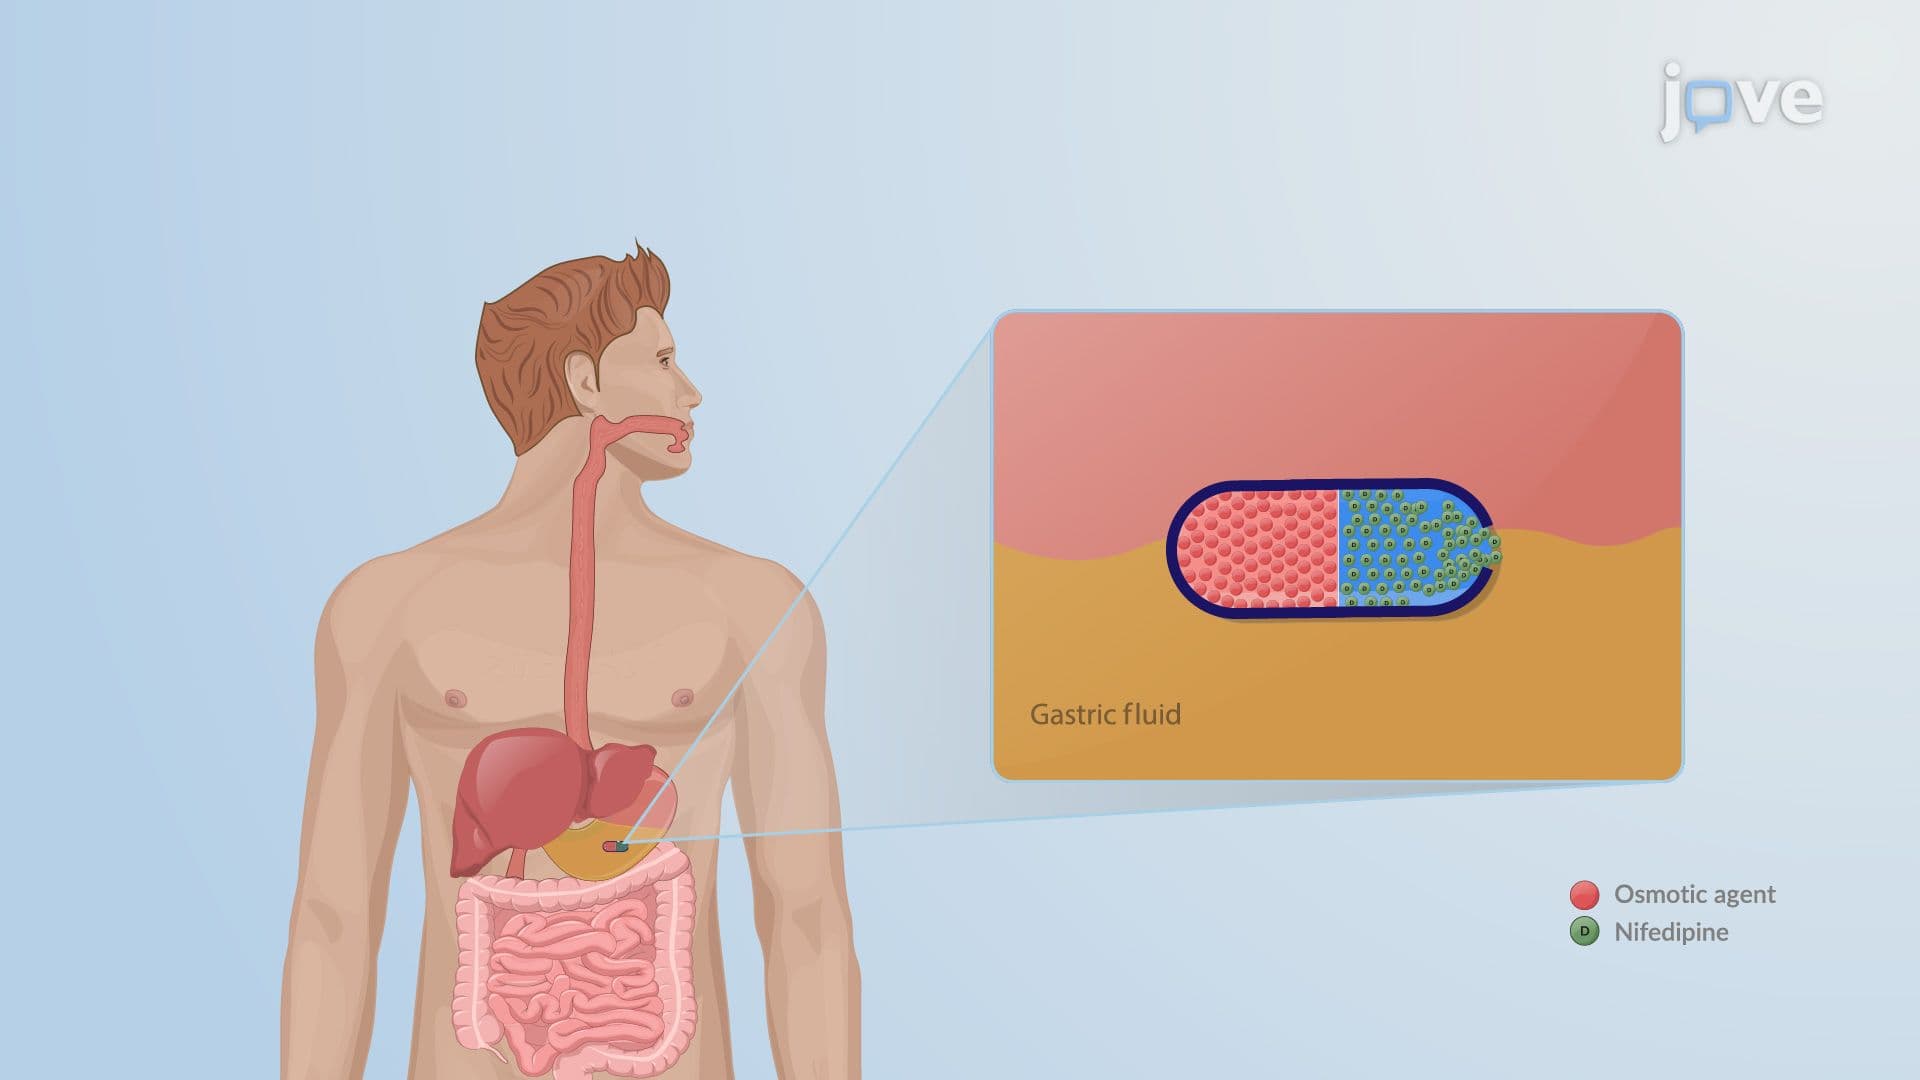
Oral Drug Delivery Systems: Continuous-Release Systems