Related Experiment Video
Updated: Jun 17, 2026
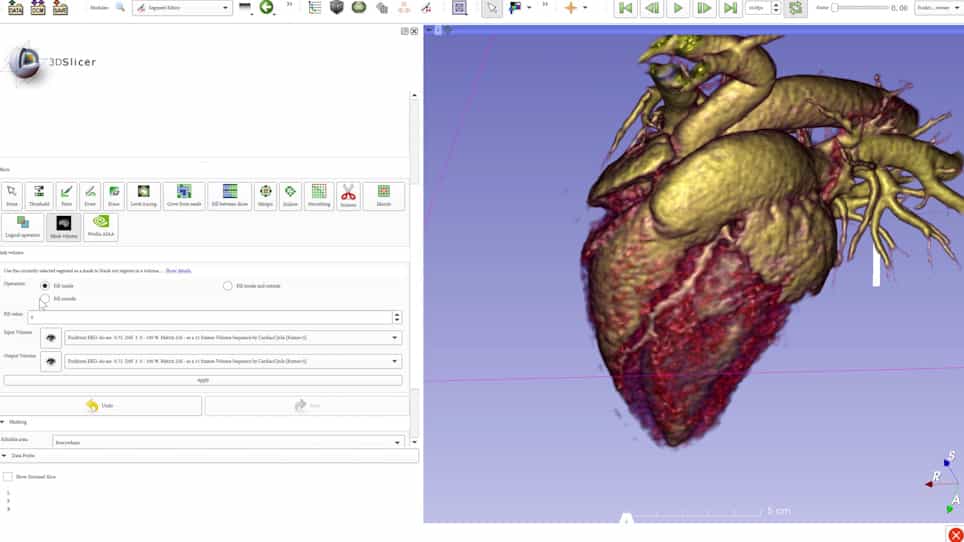
Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
Evaluation of anatomic valve opening and leaflet morphology in aortic valve bioprosthesis by using multidetector CT:
Fabien Chenot1, Patrick Montant, Céline Goffinet
1Divisions of Cardiology and Radiology; Cliniques Universitaires St-Luc, Université Catholique de Louvain, Avenue Hippocrate 10-2881, B-1200 Brussels, Belgium.

Purpose:
To prospectively determine whether cardiac-gated multidetector computed tomography (CT) allows visualization of aortic valve leaflets after bioprosthetic aortic valve replacement (AVR), to provide an accurate method for measuring the aortic valve opening, and to provide morphologic and functional information regarding the mechanism underlying poor function of the bioprosthetic valve.
Materials And Methods:
The institutional review board approved the study protocol; informed consent was given. Fifty-four patients (27 men; mean age, 75 years + or - 8 [standard deviation]) with bioprosthetic AVR implanted 2 years + or - 3 earlier underwent 64-section CT and transthoracic echocardiography (TTE). Two blinded observers manually planimetered the aortic valve area (AVA) by using a computer workstation on end-systolic short-axis CT images and measured opening angles (OAs) between the bioprosthesis annulus base and the free margin on long-axis images. These measurements were compared with those of the effective orifice area (EOA) of the valve at Doppler continuity-equation TTE by using regression and Bland-Altman methods. Morphology and mobility of leaflets in normally functioning (EOA indexed to body surface area [EOA(i)] > 0.65 cm(2)/m(2)) and dysfunctional (EOA(i)< 0.65 cm(2)/m(2)) AVRs were compared.
Results:
AVA at CT correlated highly to EOA at TTE (r = 0.93, P < .001) but was significantly larger (1.2 cm(2) + or - 0.4 vs 1.1 cm(2) + or - 0.3, P < .001) than EOA at TTE. In dysfunctional bioprostheses (n = 34), CT results showed a variety of morphologic abnormalities, such as leaflet thickening (n = 9), presumed thrombotic material (n = 6), and leaflet calcification (n = 1). Multidetector CT results demonstrated restriction of leaflet motion indicated by lower OA (64 degrees + or - 5 vs 79 degrees + or - 3, P < .0001) in dysfunctional AVRs than in normally functioning AVRs (n = 11).
Conclusion:
Sixty-four-section CT can help accurately measure AVA in bioprosthetic AVR compared with EOA at TTE. It can also show morphologic abnormalities and reduced leaflet motion in a dysfunctional bioprosthesis, thereby potentially unraveling the mechanism of dysfunction.
Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:20
Imaging Studies for Cardiovascular System II:Types of Echocardiography
Types of Echocardiography
Transthoracic Echocardiography (TTE)
TTE is the most common type of echocardiogram which involves placing a transducer on the patient's chest, emitting sound waves to create heart images. TTE is invaluable for evaluating the heart's size, structure, and motion, making it particularly useful for diagnosing...