Related Experiment Video
Updated: Jun 17, 2026


A Mouse 5/6th Nephrectomy Model That Induces Experimental Uremic Cardiomyopathy
Published on: November 7, 2017
Hemolytic uremic syndrome: Events of the past decade
1Department of Pediatrics, University of Ottawa; Children's Hospital of Eastern Ontario; Canadian Pediatric Kidney Disease Research Centre, Ottawa, Ontario.

Insights
The Canadian Pediatric Kidney Disease Research Centre (CPKDRC) was established in 1985. Collaborative research has focused on childhood Hemolytic Uremic Syndrome (HUS) and E. coli infections.
Area of Science:
- Pediatric Nephrology
- Infectious Diseases
- Epidemiology
Background:
- The Canadian Pediatric Kidney Disease Research Centre (CPKDRC) was founded in 1985.
- Collaborative research across Canadian pediatric centers has been central to its activities.
Purpose of the Study:
- To outline the establishment and research initiatives of the CPKDRC.
- To detail key studies on childhood Hemolytic Uremic Syndrome (HUS) and E. coli infections.
- To project future research directions for HUS prevention and management.
Main Methods:
- National Retrospective Study of Childhood Hemolytic Uremic Syndrome (HUS).
- National Prospective Study of Risk Factors for Developing Escherichia coli O157:H7 Infection.
- Intervention Studies for the Prevention of HUS.
Main Results:
- Established a national collaborative network for pediatric kidney disease research.
- Identified risk factors and intervention strategies for childhood HUS.
- Laid groundwork for future research into HUS etiology and long-term outcomes.
Conclusions:
- The CPKDRC has facilitated significant advancements in understanding and managing childhood HUS.
- Future research will focus on identifying at-risk children and improving long-term renal health post-HUS.
- Continued collaboration is essential for addressing pediatric kidney diseases.
Abstract:
This article describes the birth of the Canadian Pediatric Kidney Disease Research Centre (CPKDRC) in 1985 and the activities that have transpired as a result of collaborative research at paediatric centres across Canada. These include the National Retrospective Study of Childhood Hemolytic Uremic Syndrome (HUS), National Prospective Study of Risk Factors for Developing Escherichia coli O157:H7 Infection, and Intervention Studies for the Prevention of HUS. A look to the future describes possible studies to determine potential factors (surrogate markers) to identify children who are at risk for developing HUS following verotoxin-producing E coli gastroenteritis, other intervention studies and a more accurate understanding of permanent renal insufficiency in children who have had HUS.
Related Concept Videos
 01:24
Nephrotic Syndrome I : Introduction
 01:18
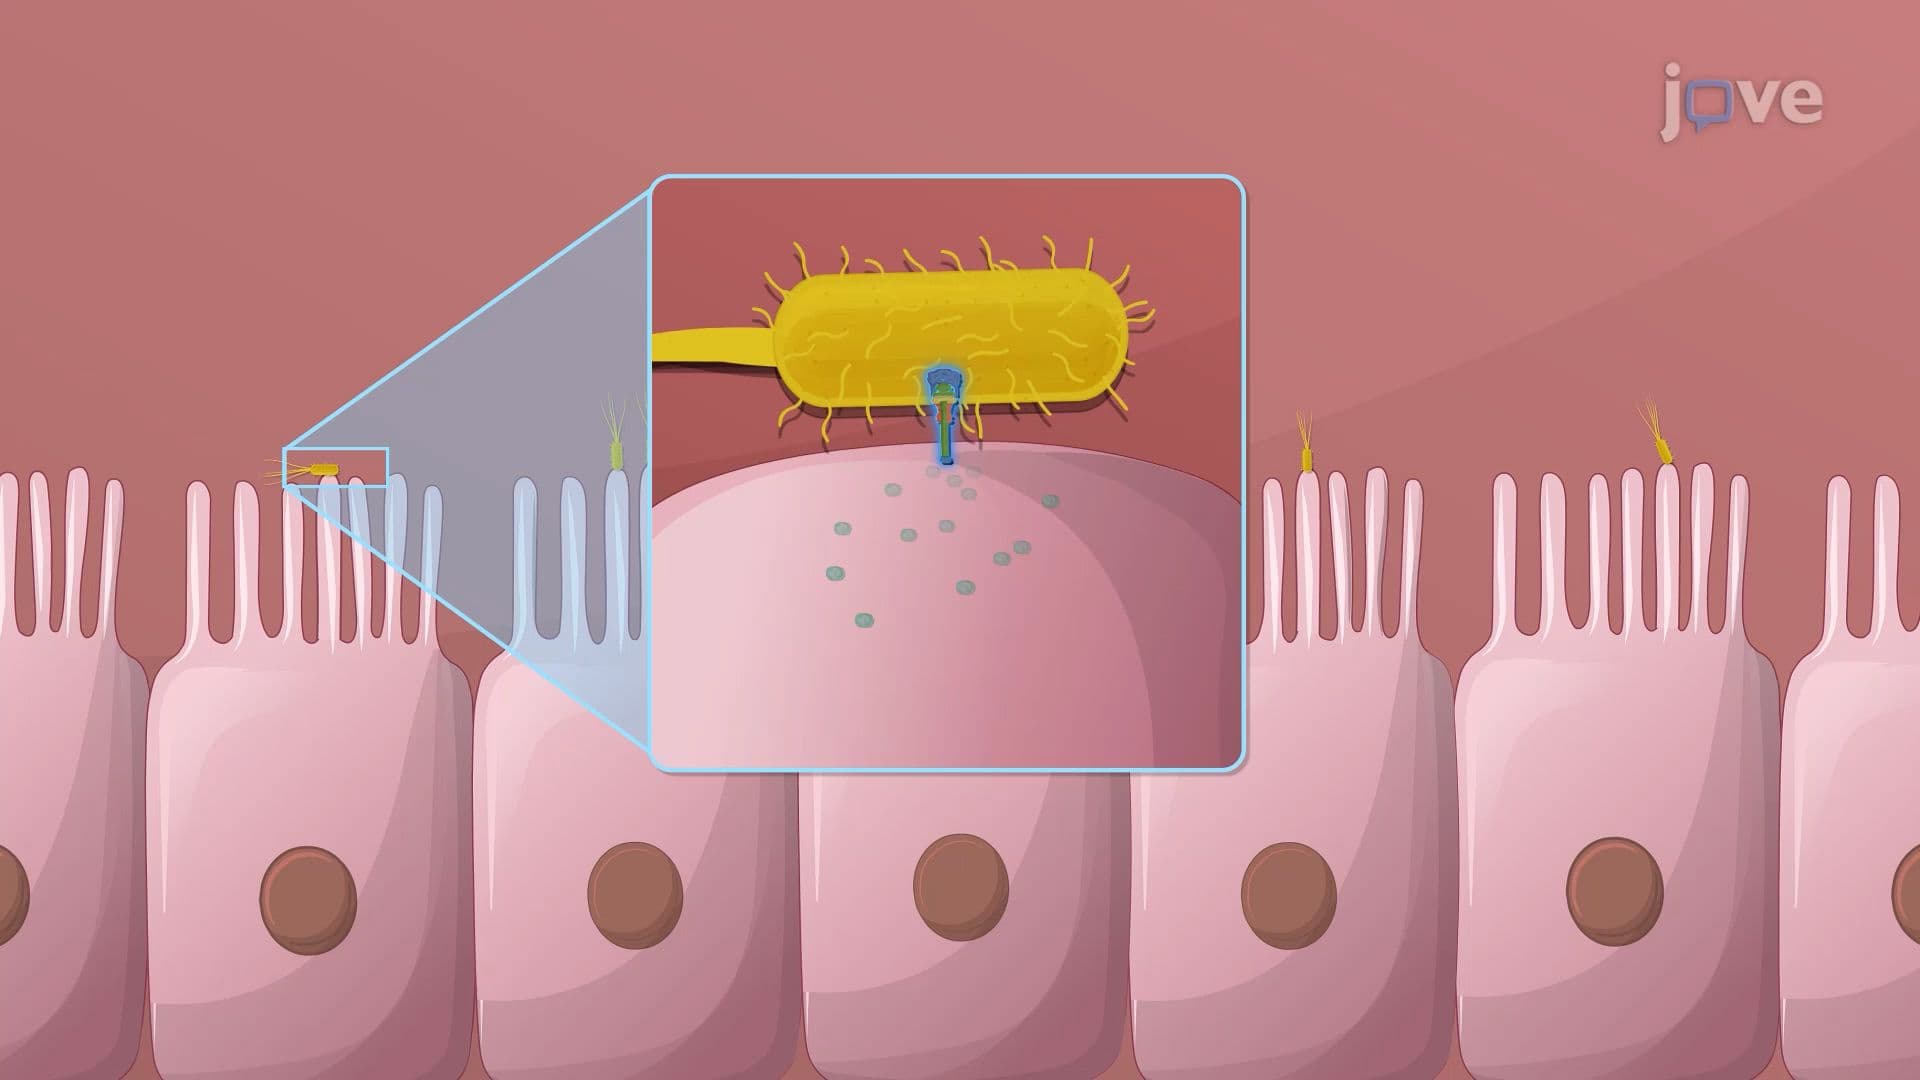
Bacterial Gastroenteritis
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:24
Hemodialysis II: Procedure and Complications
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:29
Acute Kidney Injury III: Clinical Manifestations