Clindamycin-resistant group B Streptococcus and failure of intrapartum prophylaxis to prevent early-onset disease

Anne J Blaschke1, Laurie S Pulver, E Kent Korgenski

  • 1Division of Pediatric Infectious Diseases, Department of Pediatrics, University of Utah School of Medicine, Salt Lake City, UT, USA. anne.blaschke@hsc.utah.edu

Guidelines recommend intrapartum antibiotic prophylaxis (IAP) for parturient women who have a screen positive for group B Streptococcus (GBS). Clindamycin should be used for IAP only if the maternal GBS isolate is susceptible. We report a case of clindamycin-resistant GBS disease in a newborn infant whose mother received clindamycin IAP, and we review clindamycin susceptibility testing.

Related Concept Videos

Clinical Significance of Antibiotic Resistance01:25

Clinical Significance of Antibiotic Resistance

Methicillin-resistant Staphylococcus aureus (MRSA) presents a critical public health threat, arising from its capacity to resist β-lactam antibiotics due to acquisition of the mecA gene within the staphylococcal cassette chromosome mec (SCCmec). This gene encodes penicillin-binding protein 2a (PBP2a), which impairs binding efficacy of methicillin and other β-lactams. MRSA has evolved into distinct clonal lineages impacting humans and animals alike, reinforcing its significance within the One...
Development of the Oral Microbiota01:28

Development of the Oral Microbiota

The establishment of the oral microbiome begins before birth, challenging the long-held belief that the fetal oral cavity is sterile. The presence of oral microbes such as Streptococcus and Fusobacterium in amniotic fluid suggests that microbial exposure may occur in utero, potentially through translocation from the maternal oral or gastrointestinal tract. This early colonization primes the neonatal immune system and sets the stage for subsequent microbial succession. Maternal health,...
Mechanism of Antibiotic Resistance in MRSA01:25

Mechanism of Antibiotic Resistance in MRSA
Antibiotic resistance in bacteria arises when microorganisms evolve the ability to withstand drugs designed to kill them or inhibit their growth, rendering once-effective treatments useless. This phenomenon, driven by genetic change and selection under antibiotic exposure, poses a profound threat to modern medicine. Mechanisms include drug-inactivating enzymes (e.g., β-lactamases), efflux pumps that eject antibiotics, mutations altering antibiotic targets, decreased drug uptake, and acquisition...
Streptococcal Pharyngitis01:27

Streptococcal Pharyngitis

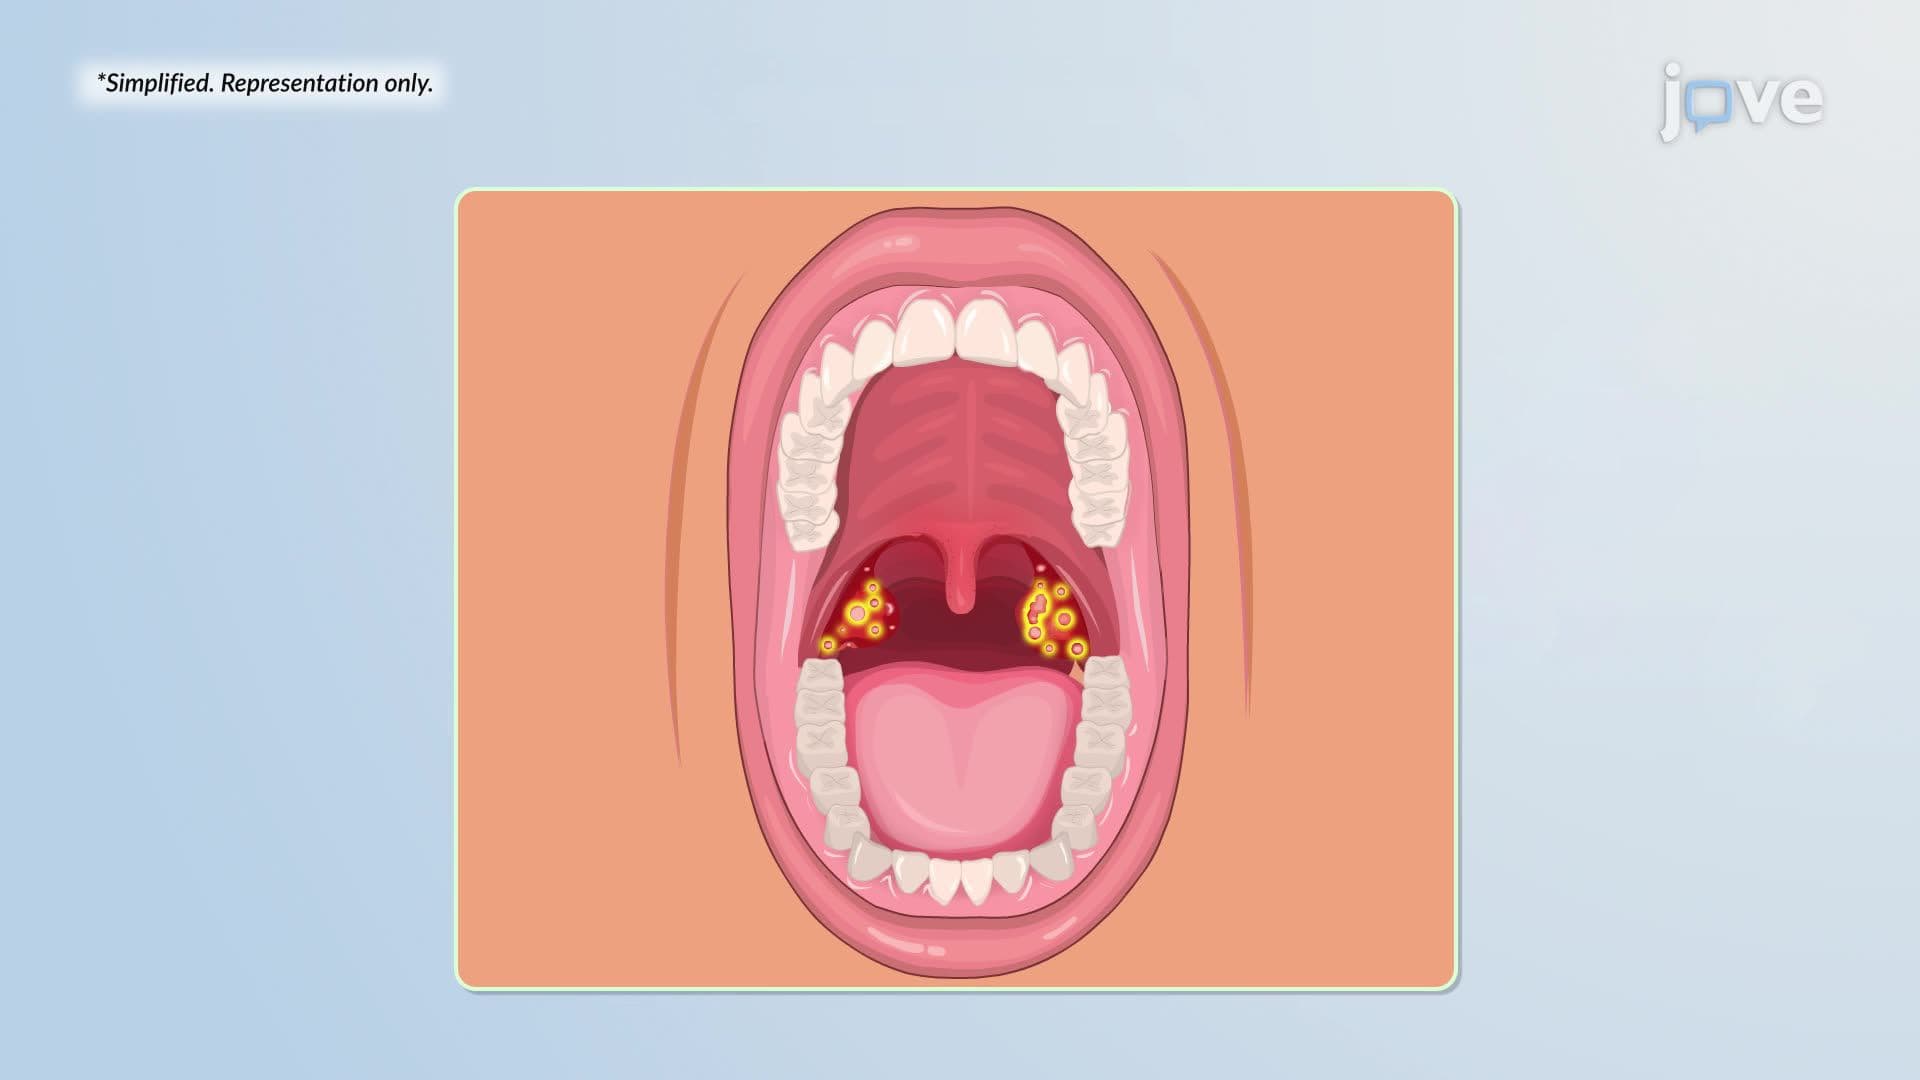
Streptococcal pharyngitis, commonly known as “strep throat,” is an acute infection of the oropharyngeal tissues caused by the Gram‑positive Group A Streptococcus (Streptococcus pyogenes). Transmission occurs primarily through respiratory droplets expelled during coughing, sneezing, or talking.Mechanisms of Host Entry and Immune EvasionUpon entering the host, S. pyogenes adheres to the mucosal epithelial cells of the pharynx via surface proteins, notably lipoteichoic acid and the antiphagocytic...
Bacterial Meningitis II: Pathophysiology01:26

Bacterial Meningitis II: Pathophysiology
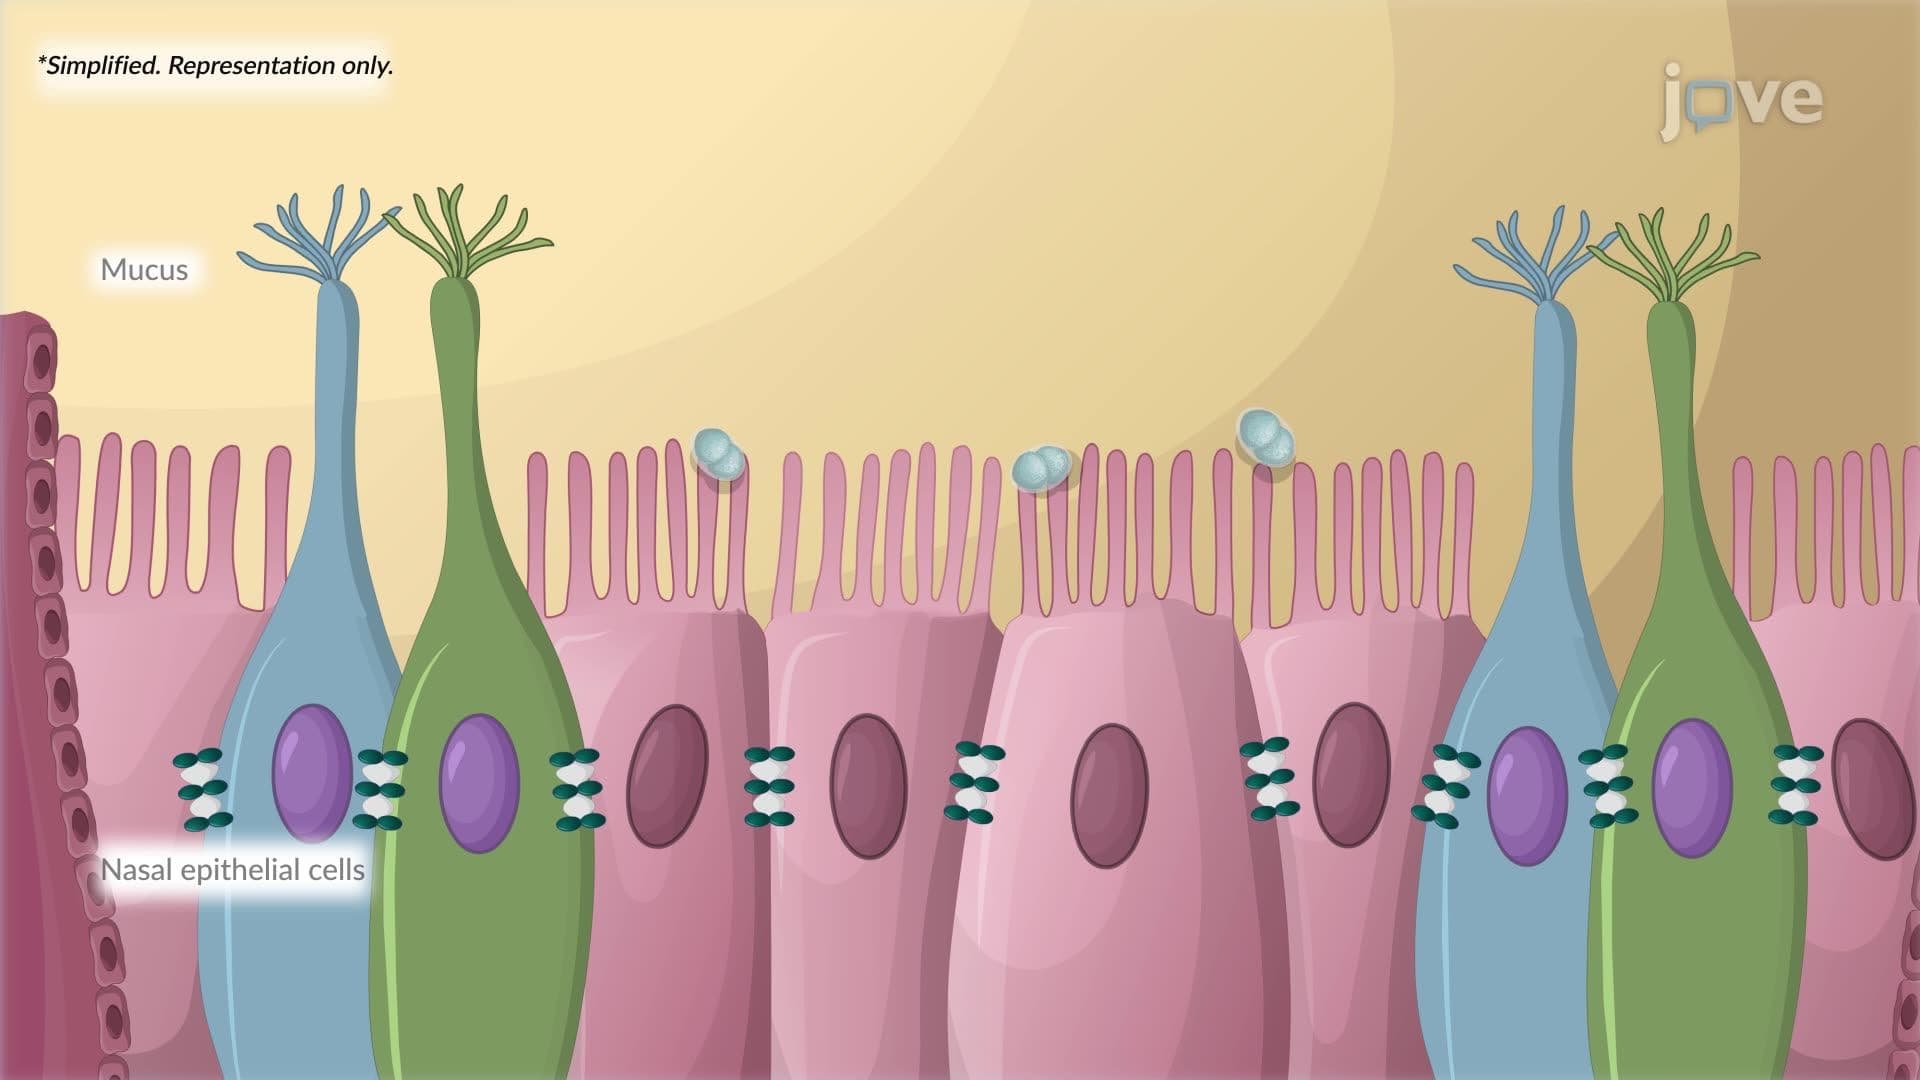
Bacterial meningitis typically begins when pathogens such as Neisseria meningitidis and Streptococcus pneumoniae colonize the nasopharynx and invade the bloodstream. This process is facilitated by bacterial virulence factors, such as polysaccharide capsules, which resist phagocytosis and complement-mediated killing. Less commonly, bacteria reach the central nervous system via contiguous spread from infections like otitis media or sinusitis, through congenital or acquired dural defects, or...
Bacterial Meningitis01:24

Bacterial Meningitis

Bacterial meningitis is a severe infectious disease involving inflammation of the meninges, the protective membranes surrounding the brain and spinal cord. It occurs when pathogenic bacteria cross the blood–brain barrier and enter the cerebrospinal fluid. Common causative organisms include Neisseria meningitidis, Streptococcus pneumoniae, Haemophilus influenzae type b, Listeria monocytogenes, and Escherichia coli K1. The exact route of entry varies by pathogen and host condition.Routes of Entry...