Related Experiment Video
Updated: Jun 17, 2026
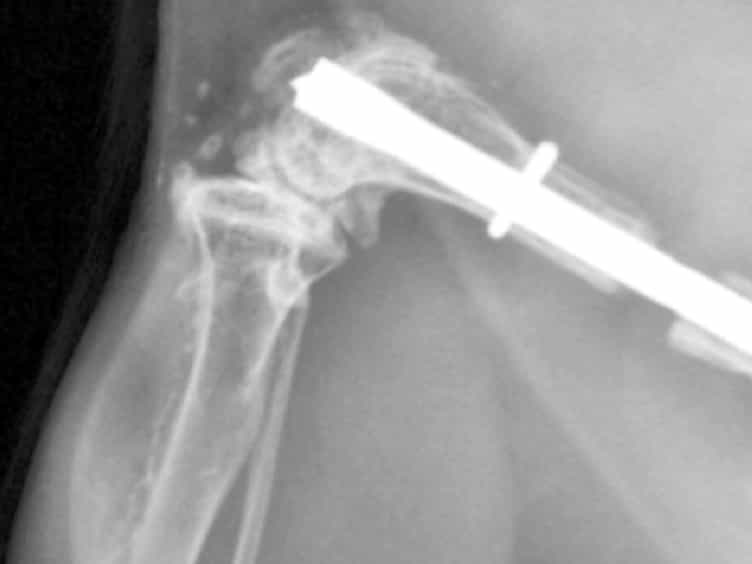

An Intramedullary Locking Nail for Standardized Fixation of Femur Osteotomies to Analyze Normal and Defective Bone Healing in Mice
Published on: November 13, 2016
[Fixation of fractures of the distal radius using the "nail-plate"]
1Marienklinik, Handchirurgische Praxis, Bozen, Italien. d.espen@handteam.eu

Objective:
Stable fixation of unstable distal radius fractures by means of a "nail-plate" with the distal plate section lying on the dorsal surface of the distal radius fragment, and the proximal nail section inside the diaphysis of the radius.
Indications:
Unstable extraarticular fractures of the distal radius AO types A2 and A3, which can be managed by closed or indirect reduction. Intraarticular fractures of the distal radius showing a nondisplaced articular component. Also indicated in patients with osteoporosis.
Contraindications:
Extraarticular distal radius fractures with a distal fragment too small for placement of the distal locking pegs and/or a comminution extending into the diaphyseal portion of the radius. Displaced intraarticular fractures of the distal radius. Nascent malunions of the distal radius.
Surgical Technique:
Closed reduction of the fracture, straight dorsal incision of 3-4 cm length centered over Lister's tubercle. The extensor pollicis longus tendon is released and retracted toward the radial side. Lister's tubercle is exposed subperiosteally and removed with a rongeur. This creates a flat surface for seating the head of the implant. Proximal dissection is carried out to expose the fracture site and the dorsal ridge on the proximal fragment. The medullary canal is opened with an awl. The radiocarpal joint line is located by inserting a needle. The silhouette of the head of the implant is drawn with a marker pen, with its distal edge resting 4-6 mm proximal to the joint line. This is done to carve a notch on the distal edge of the proximal fragment in line with the third extensor compartment with the purpose of receiving the neck of the device. The insertion jig is assembled to the implant. The implant is then introduced in a retrograde fashion, through the fracture site, into the proximal fragment and advanced with gentle rotational motion. The head of the device is seated flush on the distal fragment. Under fluoroscopic guidance, in an anatomic lateral view, the tract for the central peg is drilled and the peg is applied in the central hole. This peg fixes the palmar tilt. By use of the jig, the proximal unicortical holes are drilled, and the proximal locking screws, which fix the radial length, are applied. After removal of the insertion jig, the remaining distal pegs are applied. During drilling, the distal fragment must be pushed up against the implant to assure that the head is flush with its surface. After application, the extensor pollicis longus tendon will course proximal to the head of the implant in the subcutaneous position while the tendons of the second and fourth extensor compartments will travel on each side of the implant, thereby avoiding tendon impingement.
Postoperative Management:
Use of a palmar synthetic splint for 10 days. Active range of motion of the fingers is allowed immediately after surgery. On the 11th postoperative day, a custom-formed short arm splint is provided and active wrist motion is started. Radiologic control 4 weeks postoperatively.
Results:
In the time between April 2005 and October 2006, 32 distal radius fractures were treated at the author's institution using the "nail-plate". Two complications were observed: loosening of a locking screw, and rupture of the extensor pollicis longus tendon 4 months postoperatively. In a study of more than 200 cases, only few complications were reported: a wound hematoma in a dialysis patient, loss of fixation of an articular fracture that was poorly indicated, and hypertrophic scar formation. In one patient complaining of persistent discomfort at the implantation site, the implant was removed.
More Related Videos
 11:21
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a short...
 01:15
Bones of the Upper Limb: Ulna
 01:05
Accessory Structures of the Skin: Nails
The main components of a nail include the following.
Nail Plate: The nail plate is the visible portion of the nail that extends beyond the fingertips or toes. It is a hard, translucent...