Related Experiment Video
Updated: Jun 17, 2026
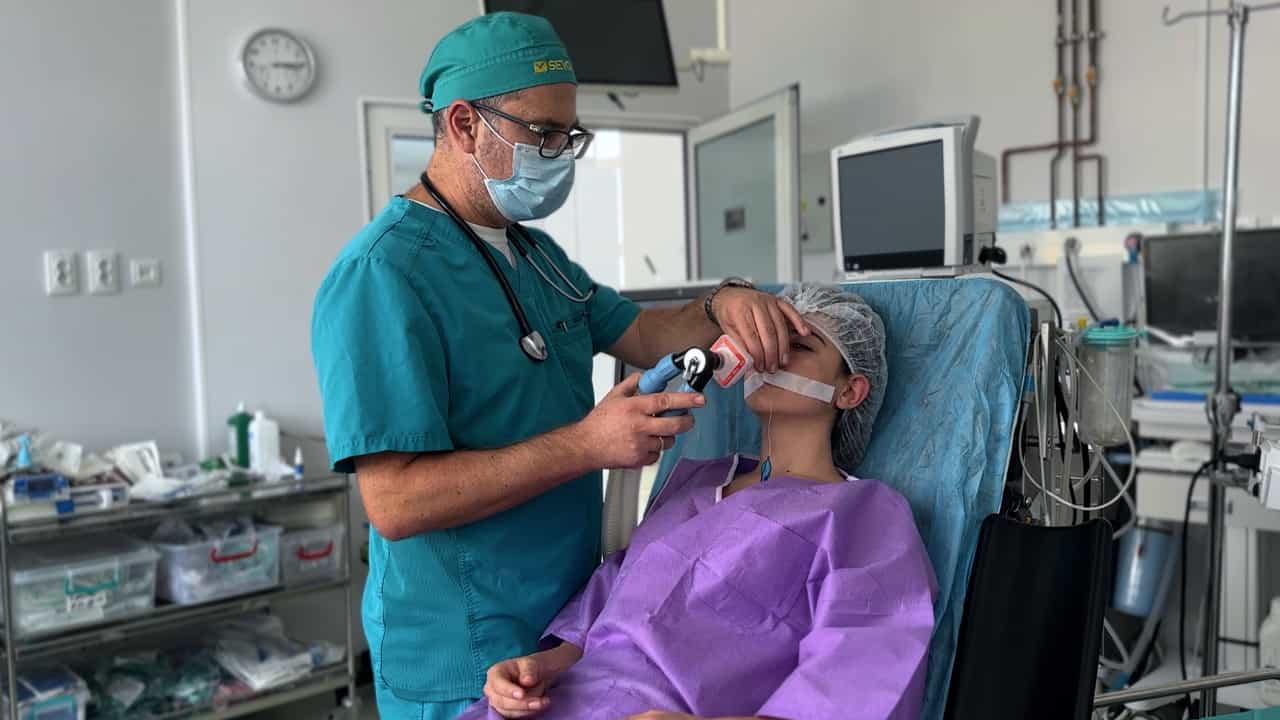
The Flexible Rhino-Laryngoscope for Awake Nasotracheal Intubation
Published on: August 2, 2024
Endoscopic surgical treatment of laryngotracheal clefts: indications and limitations
Eréa-Noël Garabedian1, Stéphane Pezzettigotta, Nicolas Leboulanger
1Service d'Oto-Rhino-Laryngologie et de Chirurgie Cervico-faciale, Hôpital d'Enfants Armand-Trousseau, 26 Av du Dr Netter, 75012 Paris, France.

Objective:
To present the indications, techniques, results, and limitations of endoscopic surgical treatment of laryngotracheal cleft.
Design:
Retrospective case note study (2005-2009).
Setting:
Department of Otolaryngology-Head and Neck Surgery, Armand Trousseau Children's Hospital, Paris, France.
Patients:
Eleven patients who underwent endoscopic cleft closure as a primary (n = 8) or secondary (n = 3) procedure among 22 patients treated for laryngotracheal clefts. We report patients' demographics, symptoms leading to the diagnosis, endoscopic evaluation method, medical examination results, and surgical techniques.
Intervention:
Endoscopic closure of the cleft under spontaneous ventilation via 2-layer interrupted sutures after excision of the mucosal edge using a carbon dioxide laser in 10 patients and a thulium laser in 1.
Main Outcome Measures:
Analysis of postoperative complications, revision surgery, need for intensive care unit admission, closure of the cleft, and long-term symptom results.
Results:
Successful closure of the 11 clefts (with revision surgery in 3 patients) without the need for intubation or intensive care unit admission enabled the elimination of aspiration in 10 patients and significant improvement in 1 patient with bilateral vocal cord paralysis. There were no significant postoperative complications.
Conclusions:
Endoscopic closure of laryngotracheal clefts is a reliable technique that significantly reduces perioperative and postoperative morbidity. The results of this technique are entirely satisfactory, and we suggest that it is suitable as a primary procedure for the treatment of type I, II, and III clefts extending to the cervical trachea, including in neonates.
Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...