Related Experiment Video
Updated: Jun 16, 2026


Optimized Griess Reaction for UV-Vis and Naked-eye Determination of Anti-malarial Primaquine
Published on: October 11, 2019
Pharmacokinetics of chloroquine and monodesethylchloroquine in pregnancy
Harin A Karunajeewa1, Sam Salman, Ivo Mueller
1School of Medicine and Pharmacology, University of Western Australia, Perth, Western Australia, Australia.

In order to determine the pharmacokinetic disposition of chloroquine (CQ) and its active metabolite, desethylchloroquine (DECQ), when administered as intermittent presumptive treatment in pregnancy (IPTp) for malaria, 30 Papua New Guinean women in the second or third trimester of pregnancy and 30 age-matched nonpregnant women were administered three daily doses of 450 mg CQ (8.5 mg/kg of body weight/day) in addition to a single dose of sulfadoxine-pyrimethamine. For all women, blood was taken at baseline; at 1, 2, 4, 6, 12, 18, 24, 30, 48, and 72 h posttreatment; and at 7, 10, 14, 28, and 42 days posttreatment. Plasma was subsequently assayed for CQ and DECQ by high-performance liquid chromatography, and population pharmacokinetic modeling was performed. Pregnant subjects had significantly lower area under the plasma concentration-time curve for both CQ (35,750 versus 47,892 microg.h/liter, P < 0.001) and DECQ (23,073 versus 41,584 microg.h/liter, P < 0.001), reflecting significant differences in elimination half-lives and in volumes of distribution and clearances relative to bioavailability. Reduced plasma concentrations of both CQ and DECQ could compromise both curative efficacy and posttreatment prophylactic properties in pregnant patients. Higher IPTp CQ doses may be desirable but could increase the risk of adverse hemodynamic effects.
In order to determine the pharmacokinetic disposition of chloroquine (CQ) and its active metabolite, desethylchloroquine (DECQ), when administered as intermittent presumptive treatment in pregnancy (IPTp) for malaria, 30 Papua New Guinean women in the second or third trimester of pregnancy and 30 age-matched nonpregnant women were administered three daily doses of 450 mg CQ (8.5 mg/kg of body weight/day) in addition to a single dose of sulfadoxine-pyrimethamine. For all women, blood was taken at baseline; at 1, 2, 4, 6, 12, 18, 24, 30, 48, and 72 h posttreatment; and at 7, 10, 14, 28, and 42 days posttreatment. Plasma was subsequently assayed for CQ and DECQ by high-performance liquid chromatography, and population pharmacokinetic modeling was performed. Pregnant subjects had significantly lower area under the plasma concentration-time curve for both CQ (35,750 versus 47,892 microg.h/liter, P < 0.001) and DECQ (23,073 versus 41,584 microg.h/liter, P < 0.001), reflecting significant differences in elimination half-lives and in volumes of distribution and clearances relative to bioavailability. Reduced plasma concentrations of both CQ and DECQ could compromise both curative efficacy and posttreatment prophylactic properties in pregnant patients. Higher IPTp CQ doses may be desirable but could increase the risk of adverse hemodynamic effects.
More Related Videos
 09:04
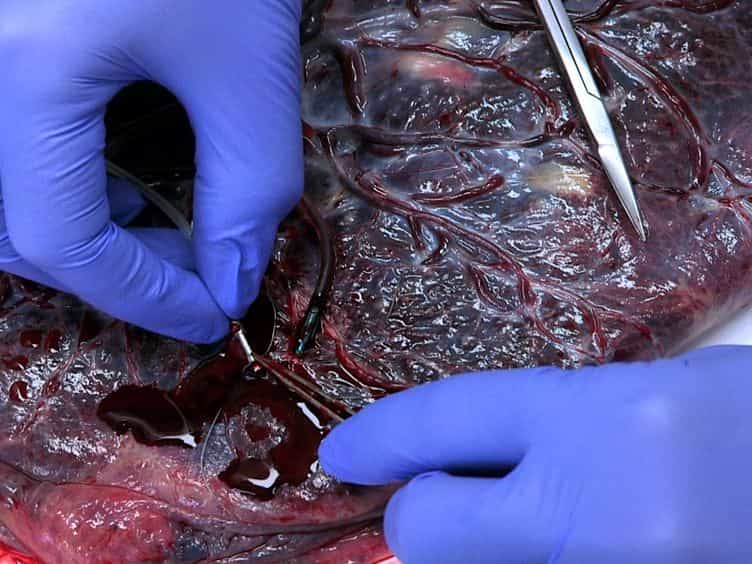
Comprehensive Evaluation of the Effectiveness and Safety of Placenta-Targeted Drug Delivery Using Three Complementary Methods
Published on: September 10, 2018
 08:08
Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:23
Nonlinear Pharmacokinetics: Dependence of Elimination Half-Life and Dose Clearance
A study on guinea pigs examined the...
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:22
Indirect-Acting Cholinergic Agonists: Pharmacokinetics
Reversible agents containing quaternary amines, such as neostigmine and edrophonium, are not easily absorbed orally because they are...