Related Experiment Video
Updated: Jun 16, 2026
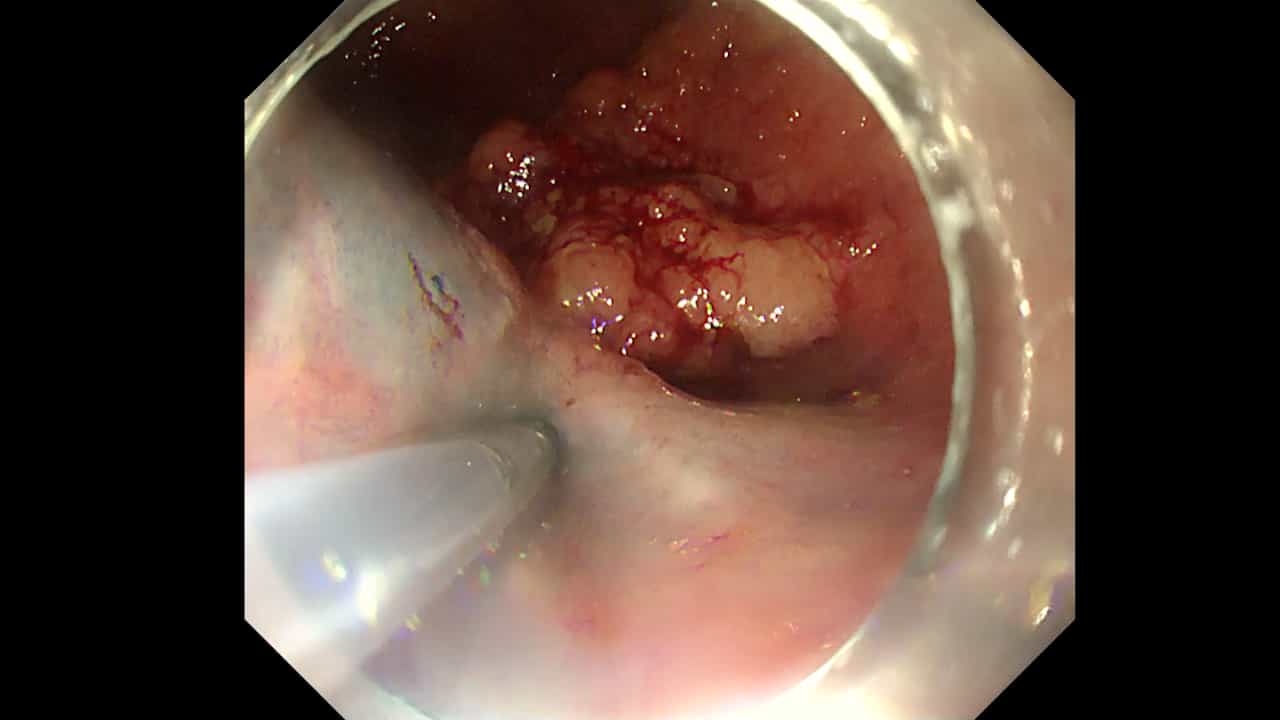

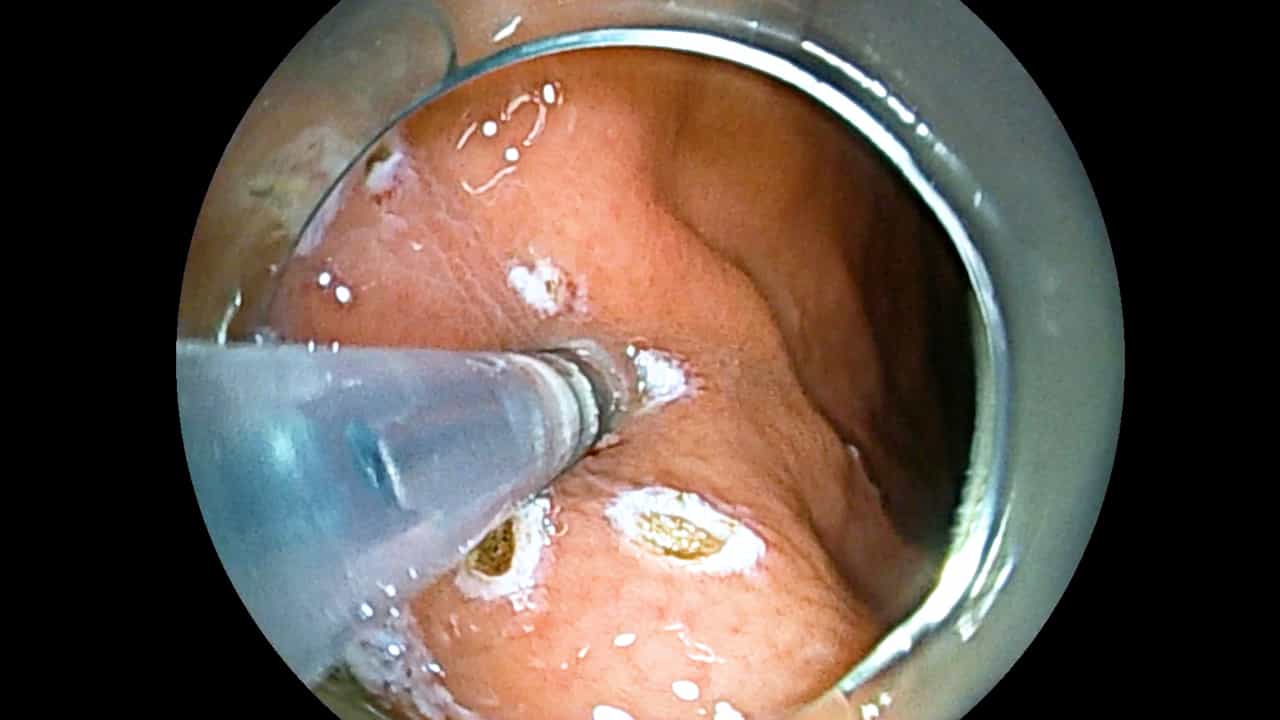
The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Endoscopic submucosal dissection for colorectal epithelial neoplasms
Hitoshi Nishiyama1, Hajime Isomoto, Naoyuki Yamaguchi
1Department of Gastroenterology and Hepatology, Nagasaki University Hospital, Sakamoto, Nagasaki, Japan.

Purpose:
Endoscopic submucosal dissection permits removal of colorectal epithelial neoplasms en bloc, but long-term clinical outcomes remain unknown.
Methods:
Endoscopic submucosal dissection was performed in 282 patients having 296 colorectal tumors that fulfilled the inclusion criteria, which included lesions greater than 20 mm in size for which en bloc resection would be difficult with endoscopic mucosal resection, lesions with fibrotic scar due to previous endoscopic treatment or biopsies, locally residual lesions after endoscopic resection, or invasive carcinoma with slight submucosal penetration. En bloc or piecemeal resection, complete (en bloc with tumor-free lateral/basal margins) or incomplete resection, and complications were assessed, and factors related to each were analyzed using logistic regression. Patients with early colon cancer received endoscopic follow-up and metastatic surveys for a median of 34 months.
Results:
En bloc resection was achieved in 89.2% (264/296) and 234 lesions (79.1%) were deemed to have undergone complete resection. A right-side colonic location was the significant contributor to incomplete resection. Perforation was seen in 24 cases (8.1%) in association with tumor size and the presence of fibrosis. There was 1 case of locally recurrent tumor with incomplete resection, whereas neither recurrence nor residual disease was observed in the complete resection group. Neither cancer-related nor cancer-unrelated death was observed.
Conclusions:
Precise assessment of curability with successful en bloc resection may reduce tumor recurrence after endoscopic submucosal dissection. The prognosis of early colorectal cancer in patients treated by endoscopic submucosal dissection is likely to be excellent, although further longer follow-up studies are warranted.
Insights
Endoscopic submucosal dissection (ESD) offers en bloc removal of colorectal tumors, with excellent outcomes and low recurrence rates observed in this study. Long-term follow-up suggests a favorable prognosis for early colorectal cancer treated with ESD.
Area of Science:
- Gastroenterology
- Surgical Oncology
- Endoscopy
Background:
- Endoscopic submucosal dissection (ESD) enables en bloc resection of colorectal epithelial neoplasms.
- Long-term clinical outcomes following ESD for colorectal neoplasms are not well-established.
Purpose of the Study:
- To evaluate the long-term clinical outcomes of endoscopic submucosal dissection (ESD) for colorectal epithelial neoplasms.
- To assess factors influencing resection completeness and complications.
Main Methods:
- ESD was performed on 296 colorectal tumors in 282 patients, including large, fibrotic, residual, or superficially invasive lesions.
- Resection completeness (en bloc/piecemeal, complete/incomplete), complications, and recurrence were assessed.
- Logistic regression analyzed factors associated with outcomes, with a median follow-up of 34 months for early colon cancer patients.
Main Results:
- En bloc resection was achieved in 89.2% of cases, with complete resection in 79.1%.
- Right-sided colonic location was linked to incomplete resection; tumor size and fibrosis increased perforation risk.
- No recurrence or residual disease was seen in the complete resection group; one recurrence occurred with incomplete resection.
Conclusions:
- Accurate assessment of curability and successful en bloc resection with ESD can minimize tumor recurrence.
- Endoscopic submucosal dissection likely offers an excellent prognosis for early colorectal cancer, warranting further long-term studies.