Related Experiment Video
Updated: Jun 16, 2026
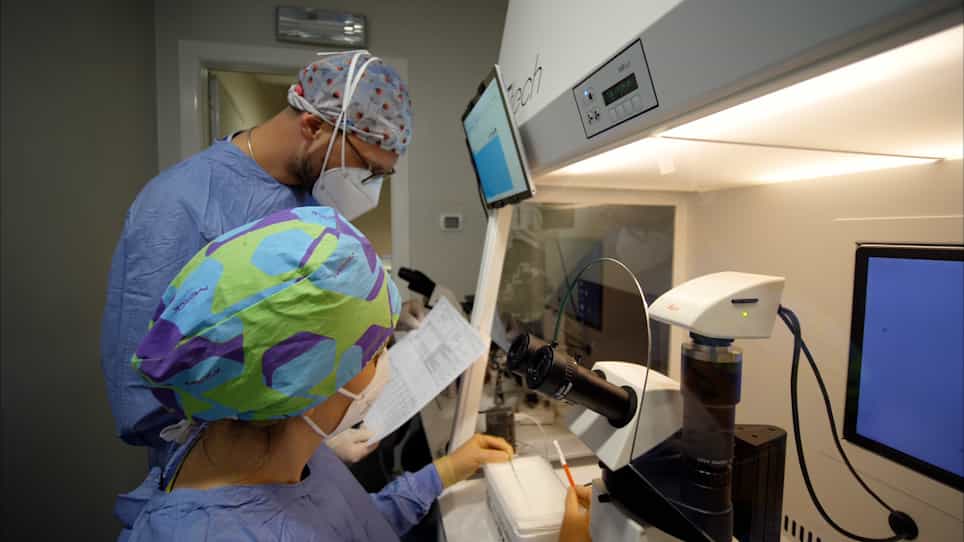

Fertility Preservation Through Oocyte Vitrification: Clinical and Laboratory Perspectives
Published on: September 16, 2021
Oral contraceptive pill, progestogen or estrogen pre-treatment for ovarian stimulation protocols for women undergoing
Brechtje Smulders1, Sanne M van Oirschot, Cindy Farquhar
1Medical School, Radboud University Nijmegen, Nijmegen, Netherlands.

Background:
For many subfertile women, assisted reproductive techniques (ART) is the only hope for a pregnancy and live birth. The combined oral contraceptive pill (OCP) given prior to the hormone therapy in an IVF cycle may result in better pregnancy outcomes of ART.
Objectives:
To assess whether pre-treatment with combined OCPs, progestogens or estrogens in ovarian stimulation protocols affects outcomes in subfertile couples undergoing ART.
Search Strategy:
We searched the Cochrane Menstrual Disorders and Subfertility Group Specialised Register, The Cochrane Central Register of Controlled Trials, MEDLINE, EMBASE, CINAHL, PsycINFO. Other electronic resources on the Internet, reference list of relevant articles were also searched as well as the ESHRE abstracts (2008). All these searches were conducted in November 2008.
Selection Criteria:
Randomised controlled trials of pre-treatment with combined OCP, progestogen or estrogen in subfertile women undergoing IVF/ICSI.
Data Collection And Analysis:
Two authors independently extracted the data and assessed risk of bias. We calculated Peto odds ratios for dichotomous data and weighted mean difference for continuous variables. Authors of trials were contacted in case of missing data.
Main Results:
No evidence of effect was found with regard to the number of live births when using a pre-treatment. However, the combined OCP in GnRH antagonist cycles, compared to no pre-treatment, is associated with fewer clinical pregnancies (Peto OR 0.69, P = 0.03) and more days and a higher amount of gonadotrophin therapy (respectively: MD 1.44, P < 0.00001; and MD 691.69, P < 0.00001). Also compared to placebo or no pre-treatment, a progestogen pre-treatment in GnRH agonist cycles, is associated with more clinical pregnancies (Peto OR 1.95, P = 0.007) and fewer ovarian cysts (Peto OR 0.21, P < 0.00001). At last, in estrogen pre-treated GnRH antagonist cycles, compared to no pre-treatment, more oocytes are retrieved (MD 2.01, P < 0.00001), but a higher amount of gonadotrophin therapy is needed (MD 207.08, P < 0.00001). For the other outcomes no evidence of effect was found or there were not enough studies available in the subgroup for pooling.
Authors' Conclusions:
There was evidence of improved pregnancy outcomes with progestogen pre-treatment and poorer pregnancy outcomes with a combined OCP pre-treatment. However, we conclude that major changes in ART protocols should not be made at this time, since the number of overall studies in the subgroups is small and reporting of the major outcomes is inadequate.

Related Concept Videos
 01:22
Birth Control Methods
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:27
Ovarian Cycle
 02:07
Oogenesis
 01:22
Oogenesis
Each primary oocyte is surrounded by a layer of pre-granulosa cells, forming what is known...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.