Related Experiment Video
Updated: Jun 16, 2026

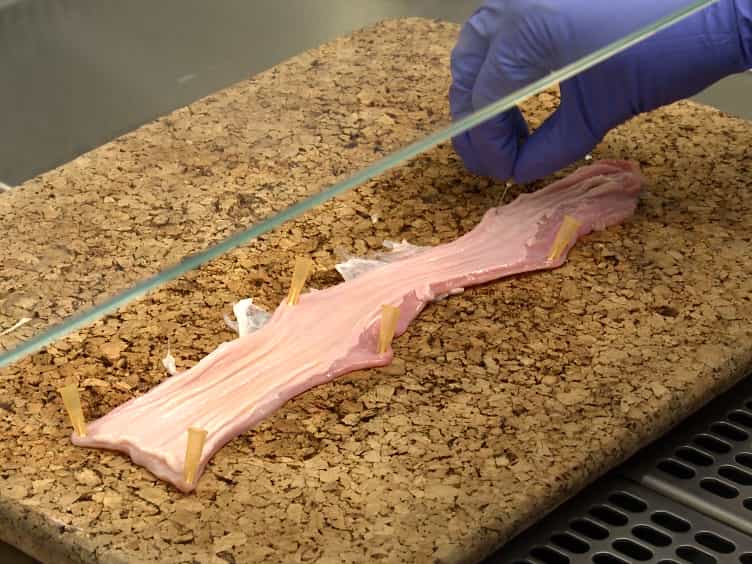
Three-Dimensional Cell Culture Models to Investigate the Epithelial Barrier in Eosinophilic Esophagitis
Published on: May 10, 2024
Esophageal epithelium of women with AIDS: thickness and local immunity
Laura Rocha1, Renata Silva, Janaínna Olegário
1General Pathology Division, Triângulo Mineiro Federal University, Uberaba, Minas Gerais, Brazil.

Abstract:
The aim of this study was to evaluate the morphological characteristics of the esophageal epithelium (EE) and its local immunity. Esophageal fragments of autopsied women were collected from 1980 to 2008, and two groups were analyzed: with AIDS (n=17) and without AIDS (n=12). The measurement of the esophageal epithelium was carried out through the image analysis software ImageJ, and the immunostaining of Langerhans cells (LCs) was carried out using anti-S100 antibody. Women with AIDS, when compared with women without AIDS, had significantly thinner EE (220.6 versus 243.5 microm), a less number of LCs (6.2 versus 18.8 LCs/mm(2)), and a higher percentage of immature or morphologically altered LCs (66.6 versus 40.0%). The malnourished women, when compared with normonourished women, regardless of AIDS, had significantly thinner EE (227.1 versus 238.0 microm) and a less number of LCs (6.2 versus 12.5 LCs/mm(2)). The percentage of immature or morphologically altered LCs was the same in both groups. Additionally, the women with AIDS (7.0 versus 2.8%) and the malnourished women (5.8 versus 3.1%) presented a significantly higher percentage of fibrosis. We concluded that AIDS and malnutrition contribute to the decrease in esophagus local immunity and, therefore, to a possible increase in local opportunistic infections.
Related Concept Videos
 01:27
Esophageal Achalasia
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:25
Mucosal Barrier of the Stomach
Within parietal cells, carbonic acid is first formed through the reaction of water and carbon dioxide. The dissociation of carbonic acid releases bicarbonate and hydrogen ions. The bicarbonate...
 01:24
Esophagus
The movement of edibles from the pharynx into the esophagus is facilitated by the upper esophageal sphincter, which is formed primarily by the...
 01:26
Gastritis II: Pathophysiology
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...