Related Experiment Video
Updated: Jun 16, 2026
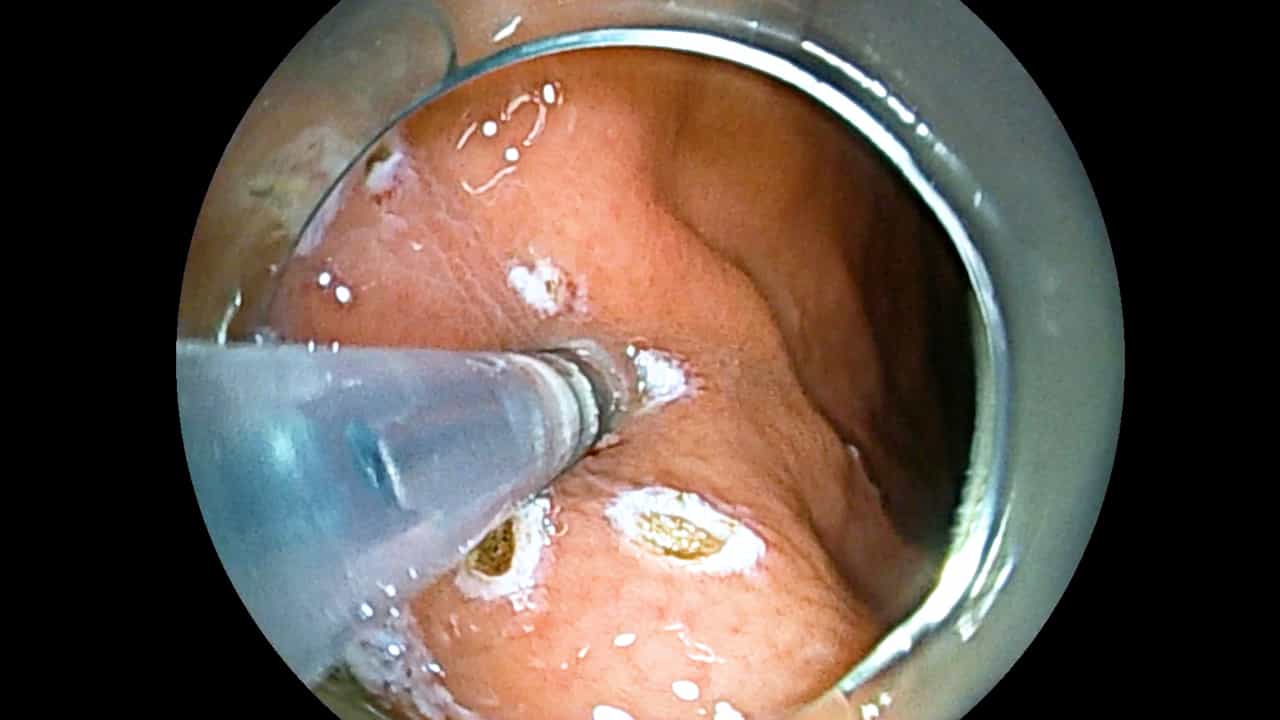

Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Clinical course of subepithelial lesions detected on upper gastrointestinal endoscopy
Yeun Jung Lim1, Hee Jung Son, Jong-Soo Lee
1Center for Health Promotion, Department of Medicine, Samsung Medical Center, Sungkyunkwan University School of Medicine, 50, Irwon-dong, Gangnam-gu, Seoul 135-710, South Korea.

Aim:
To evaluate the natural history of subepithelial lesions.
Methods:
We reviewed the medical records of 104159 patients who underwent upper gastrointestinal endoscopy at the Center for Health Promotion of Samsung Medical Center between 1996 and 2003. Subepithelial lesions were detected in 795 patients (0.76%); 252 patients were followed using upper gastrointestinal endoscopy for 82.5 +/- 29.2 mo (range, 12-160 mo; median, 84 mo; 1st quartile, 60 mo; 3rd quartile, 105 mo). The median interval of follow-up endoscopy was 12 mo (range, 6-105 mo; 1st quartile, 12 mo; 3rd quartile, 24 mo).
Results:
The mean patient age was 53 years (range, 22-80 years), and the male-to-female ratio was 2.36:1 (177/75). The lesion size at initial measurement averaged 8.9 mm (range, 2-25 mm; median, 8 mm; 1st quartile, 5 mm; 3rd quartile, 10 mm). Of the 252 lesions, 244 (96.8%) were unchanged and 8 (3.2%) were significantly increased in size (from 12.9 +/- 6.0 to 21.2 +/- 12.2 mm) after a mean interval of 59.1 +/- 27.5 mo (range, 12-86 mo). Surgical resection of lesions was performed when the lesions were > or = 3 cm in diameter. Two lesions were diagnosed as gastrointestinal stromal tumors with an intermediate or high risk of malignancy and one lesion was classified as a schwannoma.
Conclusion:
Most small subepithelial lesions do not change as shown by endoscopic examination, and regular follow-up with endoscopy may be considered in small, subepithelial lesions, especially lesions < 1 cm in size.

Related Concept Videos
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:27
Peptic Ulcer
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:26
Gastritis II: Pathophysiology
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis