Related Experiment Video
Updated: Jun 16, 2026
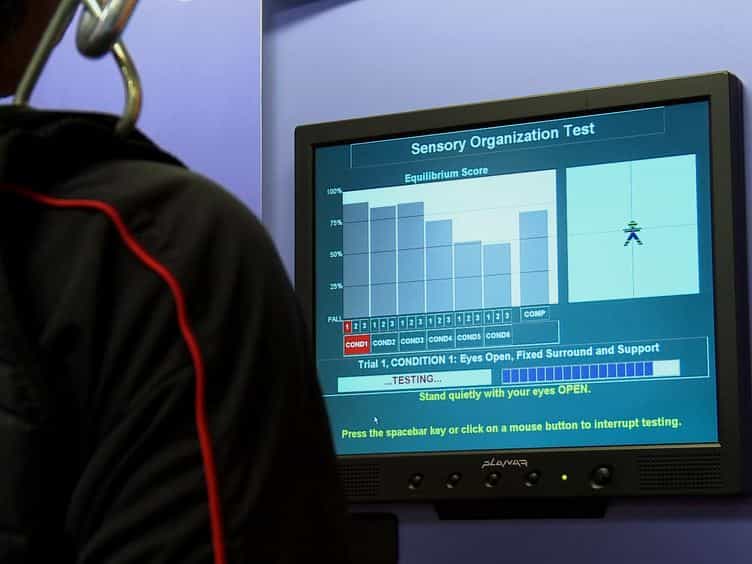

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
The effectiveness of walking stick use for neurogenic claudication: results from a randomized trial and the effects
Christine M Comer1, Mark I Johnson, Paul R Marchant
1Academic Unit of Musculoskeletal Disease, University of Leeds, Leeds, UK.

Unlabelled:
Comer CM, Johnson MI, Marchant PR, Redmond AC, Bird HA, Conaghan PG. The effectiveness of walking stick use for neurogenic claudication: results from a randomized trial and the effects on walking tolerance and posture.
Objectives:
To determine the immediate effects of using a stick on walking tolerance and on the potential explanatory variable of posture, and to provide a preliminary evaluation of the effects of daily walking stick use on symptoms and function for people with neurogenic claudication.
Design:
A 2-phase study of neurogenic claudication patients comprising a randomized trial of 2 weeks of home use of a walking stick and a crossover study comparing walking tolerance and posture with and without a walking stick.
Setting:
A primary care-based musculoskeletal service.
Participants:
Patients aged 50 years or older with neurogenic claudication symptoms (N=46; 24 women, 22 men, mean age=71.26y) were recruited.
Intervention:
Walking stick.
Main Outcome Measures:
Phase 1 of the trial used the Zurich Claudication Questionnaire symptom severity and physical function scores to measure outcome. The total walking distance during a shuttle walking test and the mean lumbar spinal posture (measured by using electronic goniometry) were used as the primary outcome measurements in the second phase.
Results:
Forty of the participants completed phase 1 of the trial, and 40 completed phase 2. No significant differences in symptom severity or physical function were shown in score improvements for walking stick users (stick user scores - control scores) in the 2-week trial (95% confidence interval [CI], -.24 to .28 and -.10 to .26, respectively). In the second phase of the trial, the ratio of the shuttle walking distance with a stick to without a stick showed no significance (95% CI, .959-1.096) between the groups. Furthermore, the use of a walking stick did not systematically promote spinal flexion; no significant difference was shown for mean lumbar spinal flexion for stick use versus no stick (95% CI, .351 degrees -.836 degrees ).
Conclusions:
The prescription of a walking stick does not improve walking tolerance or systematically alter the postural mechanisms associated with symptoms in neurogenic claudication.