Related Experiment Video
Updated: Jun 16, 2026

Studying the Hypothalamic Insulin Signal to Peripheral Glucose Intolerance with a Continuous Drug Infusion System into the Mouse Brain
Published on: January 4, 2018
Timing of bolus in children with type 1 diabetes using continuous subcutaneous insulin infusion (TiBoDi Study)
Andrea E Scaramuzza1, Dario Iafusco, Laura Santoro
1Department of Paediatrics, University of Milano, Ospedale Luigi Sacco, 20154 Milan, Italy. scaramuzza.andrea@hsacco.it

Insights
Administering insulin boluses 15 minutes before meals significantly improves glycemic control in children with type 1 diabetes. This timing helps maintain blood glucose levels closer to the therapeutic target after eating.
Area of Science:
- Pediatric Endocrinology
- Metabolic Disorders
- Diabetes Management
Background:
- Continuous subcutaneous insulin infusion (CSII) is a safe and effective method for insulin delivery in children with type 1 diabetes (T1D).
- Achieving stable glycemic control in pediatric T1D patients using CSII remains challenging.
- Optimizing basal rates and bolus timing are critical factors for effective diabetes management.
Purpose of the Study:
- To evaluate the optimal timing for a preprandial bolus dose delivered via insulin pump in pediatric patients with type 1 diabetes.
- To determine if bolus timing impacts postprandial glycemic control in children with T1D.
Main Methods:
- The study involved 30 children diagnosed with type 1 diabetes.
- Participants received a standard meal following different timing strategies for their insulin bolus dose.
- Postprandial glucose levels were monitored to assess the impact of bolus timing.
Main Results:
- Postprandial glucose levels were lower when bolus doses were administered 15 minutes or immediately before meals compared to after meals.
- A statistically significant difference was observed at the 1-hour postprandial time point, with pre-meal boluses yielding better glucose control.
- While the overall area under the curve (AUC) did not differ significantly, the standard deviation of the AUC was lowest with a 15-minute pre-meal bolus, indicating more consistent glucose responses.
Conclusions:
- The findings support administering preprandial insulin boluses before, rather than after, meals in pediatric patients with type 1 diabetes.
- This timing strategy can be beneficial even in cases where patients experience pre-meal hypoglycemia.
- Optimizing bolus timing is a key strategy for improving glycemic control in children managed with insulin pumps.
Background:
Continuous subcutaneous insulin infusion is considered a safe and effective way to administer insulin in pediatric patients with type 1 diabetes, but achieving satisfactory and stable glycemic control is difficult. Several factors contribute to control, including fine-tuning the basal infusion rate and bolus timing. We evaluated the most effective timing of a pump-delivered, preprandial bolus in children with type 1 diabetes.
Methods:
We assessed the response of 30 children with type 1 diabetes to a standard meal after different timing of a bolus dose.
Results:
The glucose levels for 3 h after the meal were lower (i.e., closer to the therapeutic target of <140 mg/dL) when the bolus doses were administered 15 min or immediately before the meal, rather than after the meal. However, these differences were not statistically significant, except at the 1-h postprandial time point: bolus just after meal, 177 +/- 71 mg/dL (9.83 +/- 3.94 mmol/L); 15 min before meal, 136 +/- 52 mg/dL (7.55 +/- 2.89 mmol/L) (P = 0.044); and just before meal, 130 +/- 54 mg/dL (7.22 +/- 3.00 mmol/L) (P = 0.024). The area under the curve (AUC) (in mg/min) did not differ significantly with different bolus times, but the SD of the AUC was the lowest with the bolus given 15 min before the meal.
Conclusions:
These data support injection of the bolus before, rather than after, eating, even if the patient is hypoglycemic before meals.


Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:18
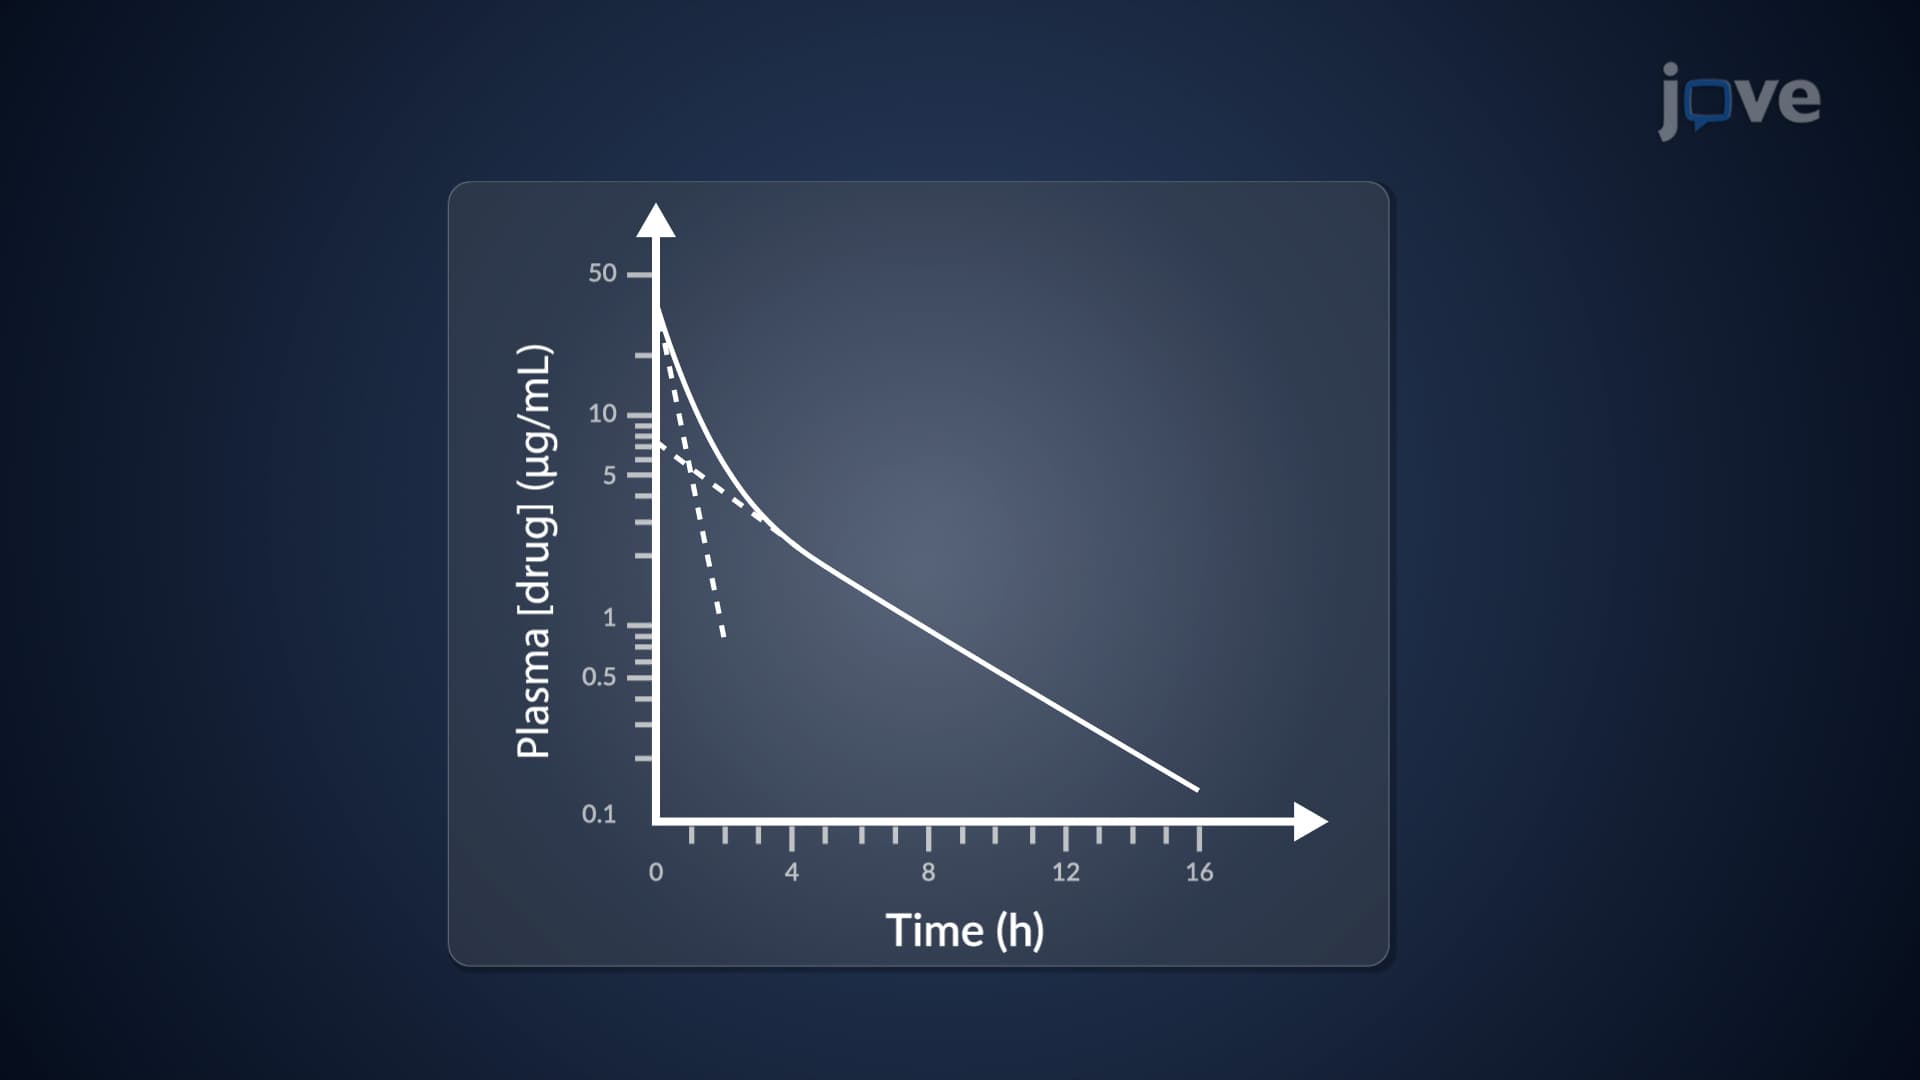
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...
 01:19
One-Compartment Open Model for IV Bolus Administration: General Considerations
The drug's presence in the body is defined by an equation representing the difference between the rates of drug entry and exit. Key parameters—elimination rate constant, half-life,...
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 00:56
One-Compartment Open Model for IV Bolus Administration: Estimation of Clearance
In the one-compartment open model for intravenous (IV) bolus administration, clearance is estimated by dividing the elimination rate by the plasma drug concentration. This equation leverages the elimination rate constant and the apparent...