Related Experiment Video
Updated: Jun 16, 2026
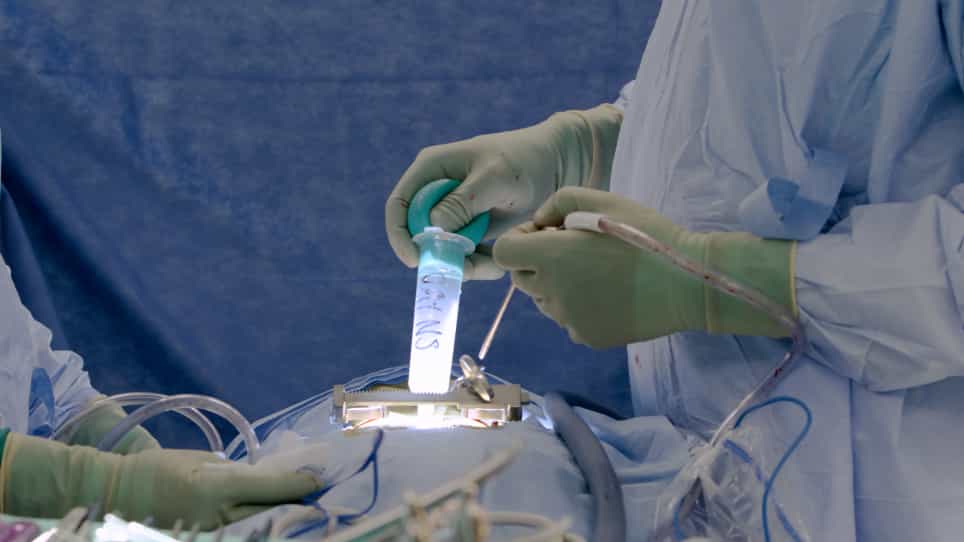

Intraoperative Ultrasound in Spinal Surgery
Published on: August 17, 2022
Nondysraphic pediatric intramedullary spinal cord lipomas: report of 5 cases
Karen L Fleming1, Laurence Davidson, Ignacio Gonzalez-Gomez
1Division of Neurosurgery, Childrens Hospital Los Angeles, Keck School of Medicine, University of Southern California, Los Angeles, California 90027, USA. kflemi2@uic.edu

Insights
Pediatric intramedullary spinal cord lipomas, rare tumors, benefit from subtotal resection and decompressive laminectomy. Long-term follow-up is crucial for managing potential regrowth and ensuring optimal neurological outcomes.
Area of Science:
- Pediatric Neurosurgery
- Spinal Cord Oncology
Background:
- Intramedullary spinal cord lipomas without dysraphism are rare pediatric tumors.
- They typically affect the cervical and thoracic regions of the spinal cord.
Observation:
- A retrospective review of 5 pediatric patients (2 months to 4 years) with these tumors was conducted.
- Four patients underwent subtotal resection with laminectomy/laminoplasty; one had decompressive laminoplasty alone.
- Median follow-up was 8 years, with two cases experiencing tumor regrowth.
Findings:
- Subtotal resection combined with decompressive laminectomy yielded the best long-term neurological outcomes.
- Gross-total excision is generally not feasible or necessary.
- Postoperative kyphosis occurred in 3 patients but did not require intervention.
Implications:
- Decompressive laminectomy and debulking are recommended for pediatric intramedullary spinal cord lipomas.
- Regular long-term monitoring is essential to detect and manage tumor recurrence or growth.
- Repeat debulking may be necessary for neurological deterioration due to tumor regrowth.
Object:
Intramedullary spinal cord lipomas not associated with dysraphism are infrequently reported. When present, they typically occur in children and have a predilection for the cervical and thoracic spinal cord. The authors review the presentation, treatment, and disease course in 5 pediatric patients, and compare the outcomes with previously reported cases.
Methods:
With institutional review board approval, a retrospective chart review was undertaken at Children's Hospital Los Angeles.
Results:
Four patients with intramedullary spinal cord lipomas and 1 patient with a lipoblastoma, none associated with dysraphism, were retrospectively reviewed. There were 2 boys and 3 girls ranging in age from 2 months to 4 years. Four patients underwent a laminectomy or laminoplasty with one or more subtotal resections. One patient initially underwent a decompressive laminoplasty without debulking. The median follow-up was 8 years (range 12 months-11 years). Two patients had regrowth of their lipoma, necessitating a second surgery in one patient and 3 debulking surgeries in the other. Postoperatively, 3 patients developed mild kyphosis, none significant enough to require orthopedic intervention. One patient underwent a stabilization procedure at the time of the initial laminectomy and tumor debulking. No patient received chemotherapy or radiation. At the most recent follow-up visit, patients demonstrated improved neurological function when compared with preoperative status.
Conclusions:
In addition to a decompressive laminectomy, debulking of the lipoma provides the best long-term neurological outcome. Gross-total excision is not warranted and usually is not possible. Long-term follow-up is needed, and repeat debulking of the lipoma is indicated if there is an increase in tumor size due to hyperplasia of residual adipocytes, when tumor growth is associated with neurological deterioration.
