Related Experiment Video
Updated: Jun 16, 2026

Clinical Efficacy of an Innovative Multidimensional Traction Therapy in Moderate Adolescent Idiopathic Scoliosis
Published on: February 10, 2026
Changes of deformity due to the position and anesthesia in adolescent idiopathic scoliosis
Choon Sung Lee1, Chang Ju Hwang, Sung-Woo Lee
1Department of Orthopaedic Surgery, Asan Medical Center, College of Medicine, University of Ulsan, Seoul, Korea.

Study Design:
Restrospective case series.
Objective:
To determine changes in the end vertebra and neutral vertebra, and in the magnitudes of coronal and rotational deformities according to position and anesthesia in patients with adolescent idiopathic scoliosis.
Summary Of Background Data:
Although it is known that coronal deformity of scoliosis has a tendency to decrease by position and anesthesia, there have been few reports on the effects of position and anesthesia on the rotational deformity of scoliosis. End vertebra and neutral vertebra can change after positioning and anesthesia, but little is known about it.
Methods:
Sixty-two structural curves in 31 patients were evaluated using standing, supine, side bending, postanesthesia, and postoperative anteroposterior plain radiographs. Cobb angles and rotation angles by Perdriolle torsionmeter were measured, and the end vertebra and neutral vertebra were identified in each radiograph.
Results:
Coronal Cobb angles decreased significantly with the correction rates of 25.0%, 31.7%, 59.5%, and 74.0%, and rotational deformities decreased with the correction rates of 6.1%, 24.5%, 6.2%, and 25.7% by supine position, anesthesia, side bending, and surgery, respectively. The end vertebrae changed in 18 patients (58.1%) in both supine and postanesthesia radiographs, and the neutral vertebrae changed in 10 patients (32.3%) in supine radiographs and in 20 patients (64.5%) in postanesthesia radiographs.
Conclusions:
Coronal deformities are significantly corrected by supine position and anesthesia. Anesthesia significantly corrects axial rotation, but further correction cannot be achieved by rod derotation. The end vertebra and neutral vertebra have a tendency to vary by position and anesthesia, which gives rise to confusion in the determination of fusion levels.
More Related Videos
 07:01
Clinical Efficacy of Ultrasound-Assisted Scoliosis-Specific Exercise in Mild-Grade Adolescent Idiopathic Scoliosis
Published on: December 2, 2025
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:16
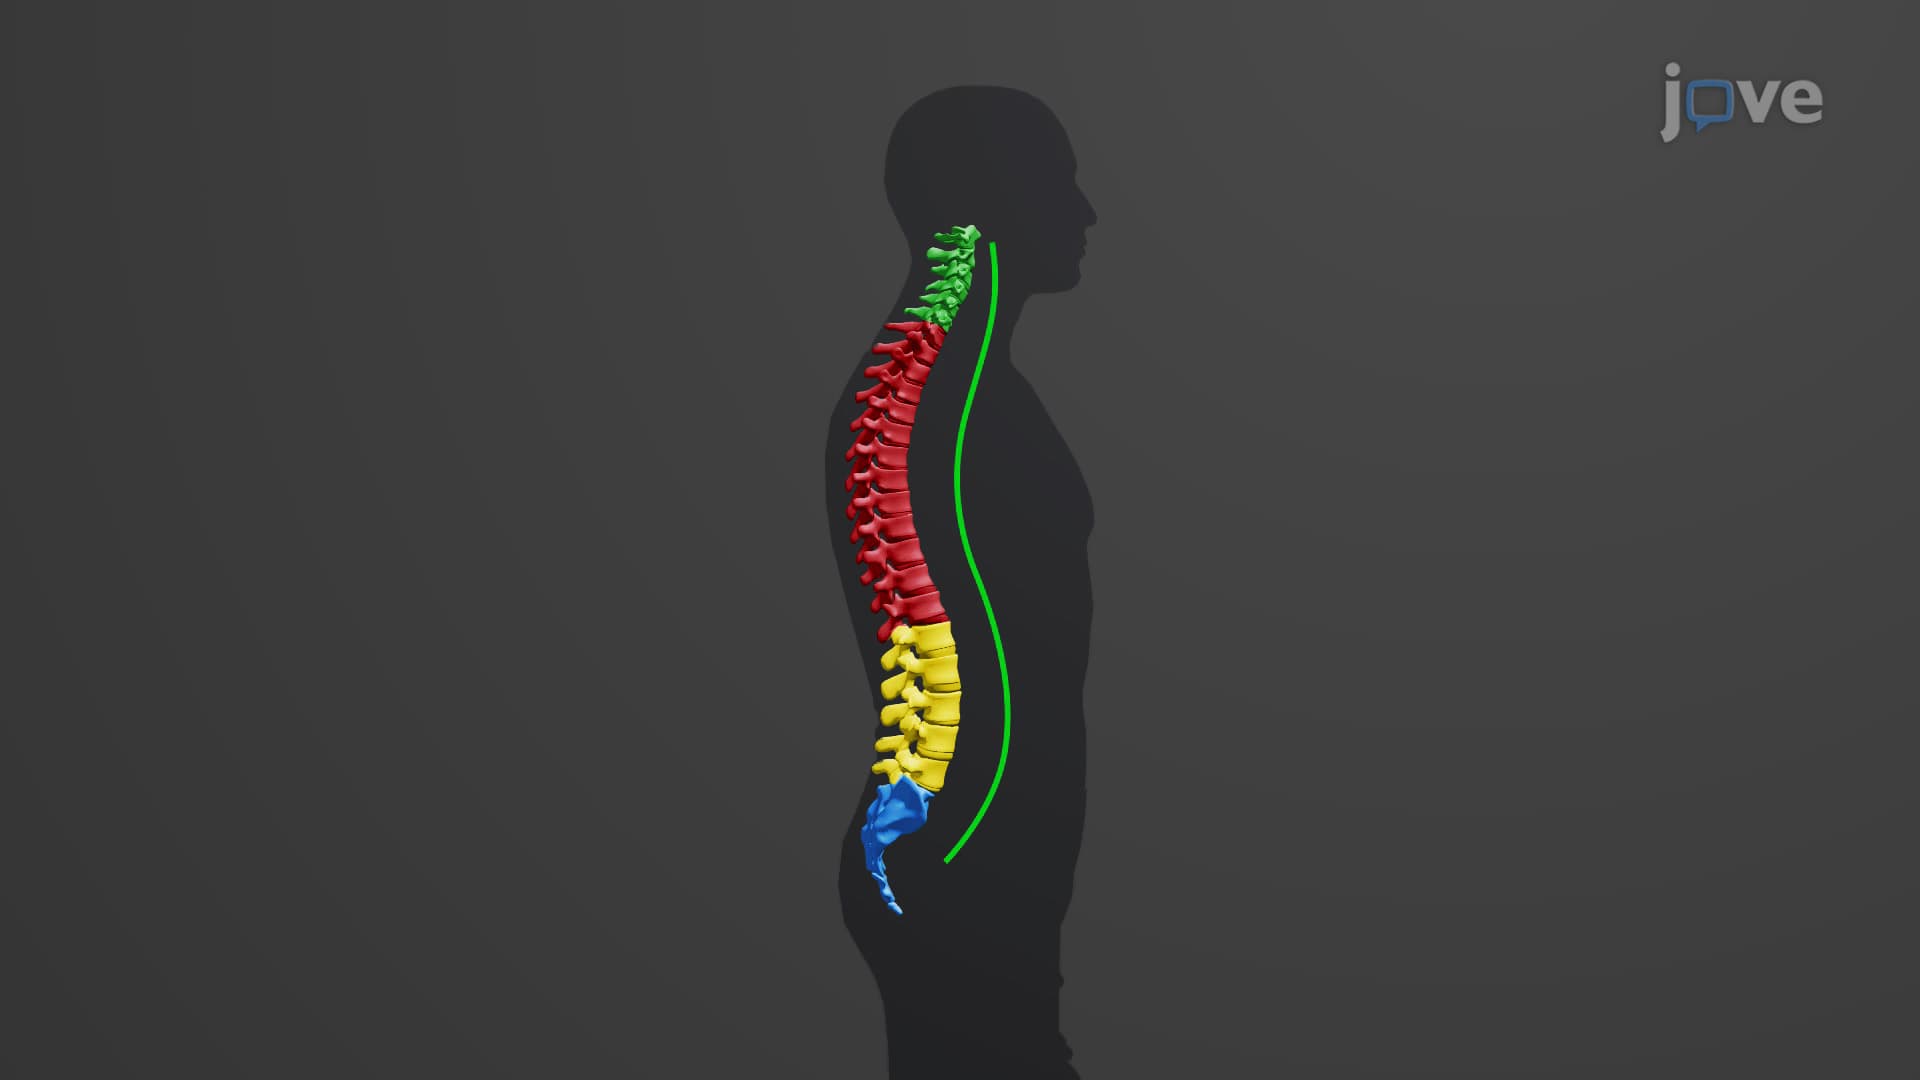
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:11
Deformation of Member under Multiple Loadings
In the case of a member with a variable cross-section, the strain is not constant but depends on the position. The deformation of an...