Related Experiment Video
Updated: Jun 16, 2026

Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Spirometry in preschool children: time has come for new reference values
H Kalhoff1, R Breidenbach, H J Smith
1Pediatric Clinic, Dortmund, Germany. hermann.kalhoff@klinikumdo.de

Insights
Current lung function reference values overestimate maximal flow rates in preschool children. Standardized spirometry in young children is crucial for accurate lung function monitoring and early asthma diagnosis.
Area of Science:
- Pediatric Pulmonology
- Respiratory Physiology
- Diagnostic Spirometry
Background:
- Lung function tests are vital for diagnosing and monitoring childhood asthma.
- Existing reference values for lung function are outdated, based on older populations from decades ago.
- Accurate, current reference values are needed for proper clinical evaluation of children's lung health.
Purpose of the Study:
- To assess the validity of current lung function reference values in 6-year-old children.
- To evaluate the correlation between lung function parameters and Body Mass Index (BMI) in this age group.
- To determine the feasibility of standardized spirometry for early lung function assessment in preschoolers.
Main Methods:
- A cross-sectional study involving 518 children (mean age 6.0 years) undergoing spirometry before school enrollment.
- Measurements included forced vital capacity (FVC), forced expiratory volume in one second (FEV1), maximal expiratory flow (PEF), and maximal expiratory flow at 75%, 50%, and 25% of vital capacity (MEF75, MEF50, MEF25).
- Spirometry followed ATS/ERS criteria, with a focus on maneuvers where expiratory time (TE) exceeded 1 second.
Main Results:
- FEV1 and FVC values were comparable to existing reference values (101.0% in boys, 95.4% in girls).
- Maximal expiratory flow parameters (PEF, MEF50) were significantly lower than reference values (68.9% in boys, 75.9% in girls) when TE > 1 sec.
- No significant correlation was found between lung function parameters and BMI in this cohort.
Conclusions:
- Current reference values significantly overestimate maximal expiratory flow rates in preschool children using spirometry with TE > 1 sec.
- Increased BMI does not appear to impair forced expiratory flow rates in 6-year-old children.
- Implementing standardized spirometry in preschool children enables precise evaluation of individual lung function development.
Abstract:
Lung function measurements play an essential role in early diagnosis and monitoring of bronchial asthma in children. For clinical evaluation, measurements are commonly compared to reference values. However, these reference values are calculated based on measurements performed in groups of mostly older children and young adults two or three decades ago. In the present, cross-sectional study, lung function measurements were performed in 518 children (241 boys and 277 girls; mean age 6.0+/-0.3 years) at a regular medical check prior to school enrollment. Spirometry was done using the MasterScreen IOS (Cardinal Health, Wurzburg). We recorded forced vital capacity (FVC), forced expiratory volume in one second (FEV(1)), maximal expiratory flow (PEF), and maximal expiratory flow at 75, 50, and 25% of vital capacity (MEF(75), MEF(50), MEF(25)). We found that FEV(1) and FVC corresponded to reference values (101.0+/-14.9% and 95.4+/-13.6%, in boys and girls, respectively). In maneuvers satisfying ATS/ERS criteria (T(E) >1 sec), forced expiratory (parameters (PEF, MEF(50)) reached only 68.9+/-13.6 and 75.9+/-26.6% of reference values, in boys and girls, respectively). There was no significant correlation of lung function parameters to BMI. In conclusion, the hitherto reference values largely overestimate the maximal flow rates of preschool children performing a forced spirometry with T(E) >1 sec. At the age of 6, forced expiratory flow values are not (yet) impaired by an increased BMI. Standardized spirometry starting in preschool children allows closely evaluating the individual development of lung function during follow-up measurements.

Related Concept Videos
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:26
Respiratory Volumes and Capacities I
 01:22
Respiratory Volumes and Capacities
 01:15
Respiratory Volumes
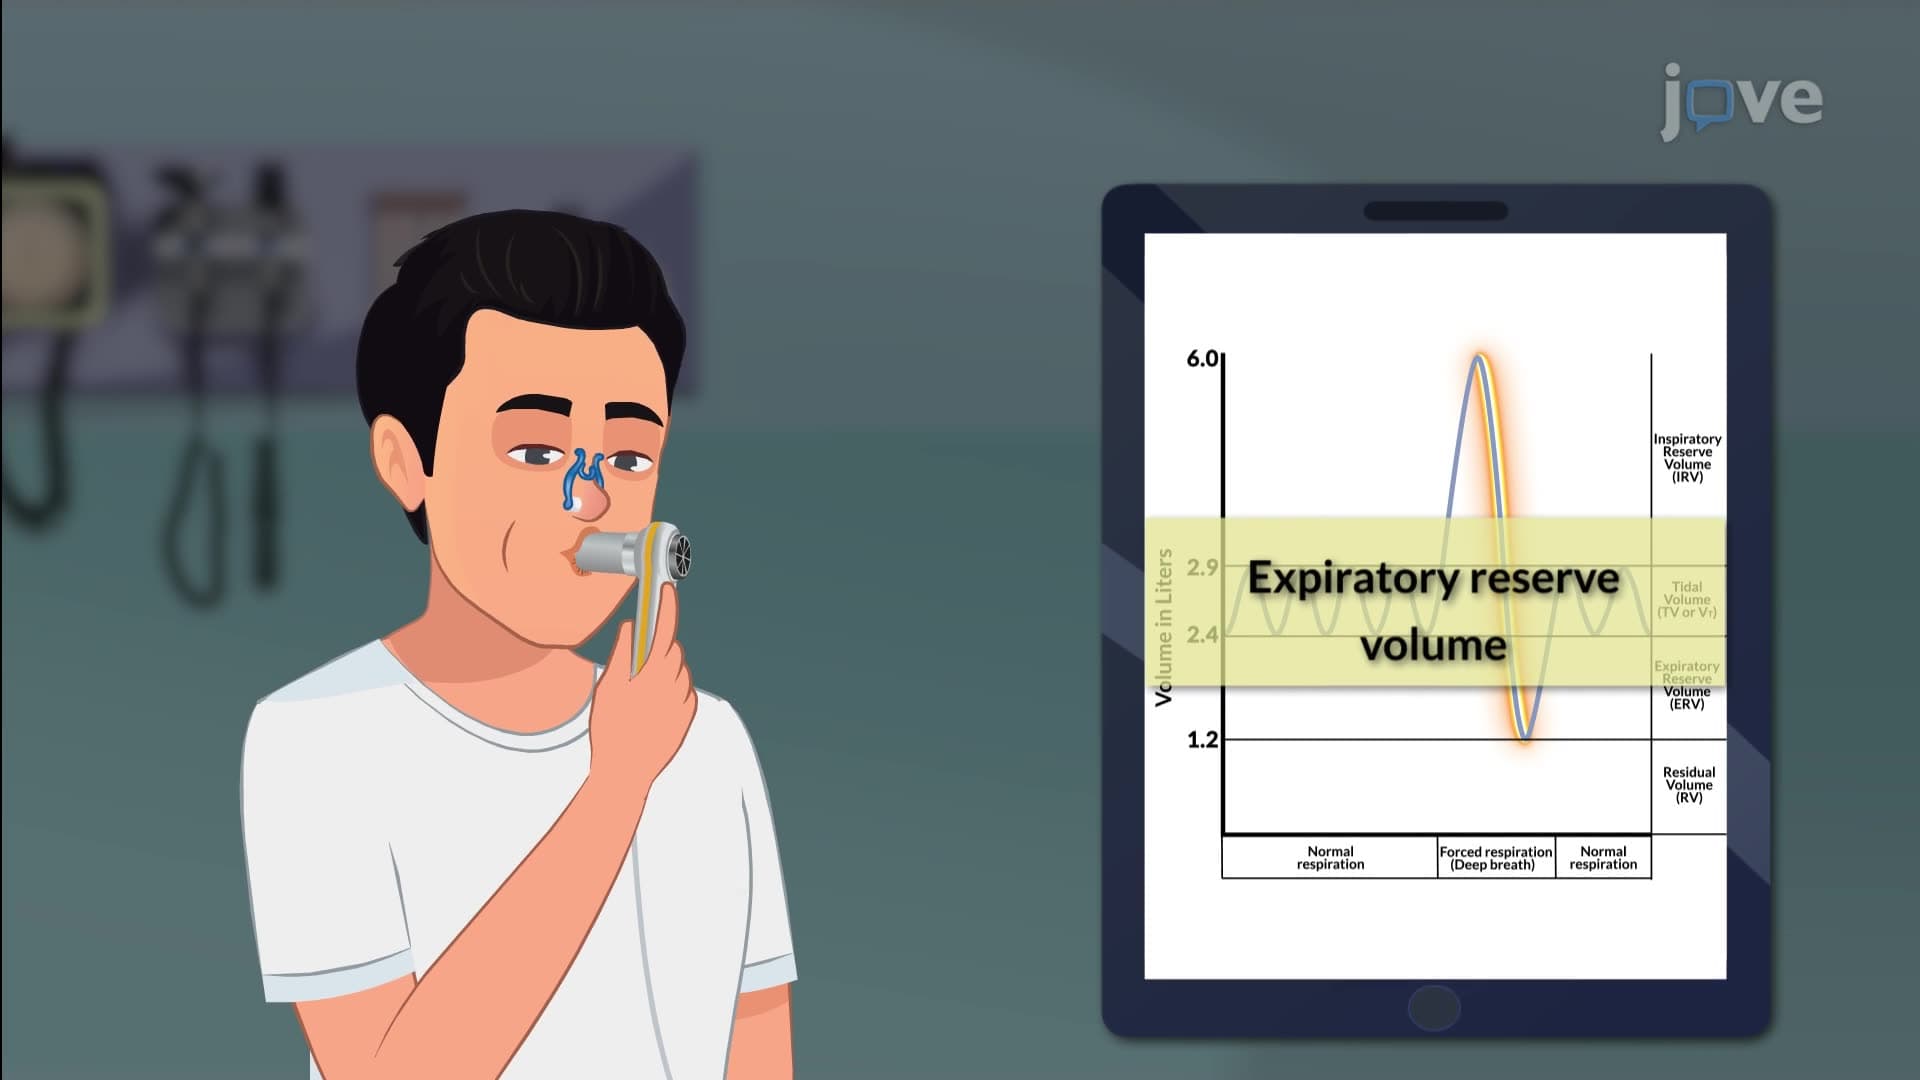
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...