Related Experiment Video
Updated: Jun 16, 2026
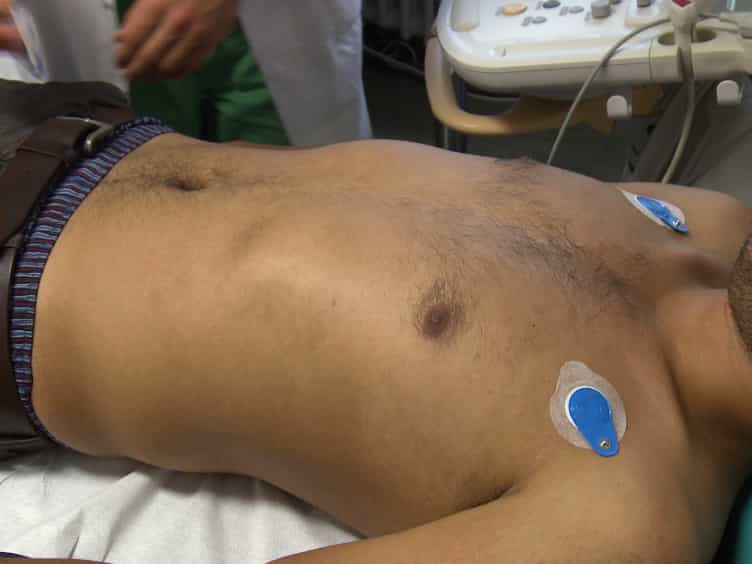
Transthoracic Speckle Tracking Echocardiography for the Quantitative Assessment of Left Ventricular Myocardial Deformation
Published on: October 20, 2016
Sequential changes of longitudinal and radial myocardial deformation indices in the healthy neonate heart
José Luiz Barros Pena1, Marconi Gomes da Silva, José Mariano Sales Alves
1Heart Institute (InCor) USP, São Paulo, Brazil. jlpena.bh@terra.com.br

Background:
Significant hemodynamic changes, including preload and afterload modifications, occur during the transition from the fetal to the neonatal environment. The ductus arteriosus closes, pulmonary vascular resistance decreases, and pulmonary blood flow increases. Strain rate (SR) and strain (epsilon) have been proposed as ultrasound indices for quantifying regional wall deformation. This study was designed to determine if these indices can detect variations in regional deformation between early and late neonatal periods.
Methods:
Data were obtained from 30 healthy neonates (15 male). The initial study was performed at a mean age of 20.1+/-14 hours (exam 1) and the second at 31.9+/-2.9 days (exam 2). Apical and parasternal views were used to quantify regional left ventricular (LV) and right ventricular (RV) longitudinal and radial SR and epsilon, and systolic, early, and late diastolic values were calculated from these curves. A paired-samples t test was performed comparing the two groups.
Results:
Compared with exam 1, LV radial deformation showed significant reductions in peak systolic epsilon in the basal and mid segments (51+/-15% vs 46+/-9%, P<.01). LV longitudinal deformation behaved similarly, showing significant peak systolic epsilon reductions in all measured segments. Systolic SR showed reductions only in the basal and apical segments of the lateral wall and in the mid portion of the inferior wall (-1.9+/-0.5 vs -1.7+/-0.3 s(-1) and -1.9+/-0.4 vs -1.7+/-0.2 s(-1), respectively, P=.03). RV longitudinal free and inferior wall systolic SR and epsilon values were significantly higher in exam 2.
Conclusions:
LV peak systolic epsilon decreases in exam 2 were possibly due to afterload increase and preload decrease. The lower RV initial deformation indices could be attributed to increased afterload caused by physiologic pulmonary hypertension or immature RV contractile properties. SR seemed to be a more robust index than epsilon and less influenced by preload and afterload hemodynamic alteration.
More Related Videos
 11:50
High-frequency High-resolution Echocardiography: First Evidence on Non-invasive Repeated Measure of Myocardial Strain, Contractility, and Mitral Regurgitation in the Ischemia-reperfused Murine Heart
Published on: July 9, 2010
 07:55
Echocardiographic Characterization of Left Ventricular Structure, Function, and Coronary Flow in Neonate Mice
Published on: April 7, 2022
