Related Experiment Video
Updated: Jun 16, 2026
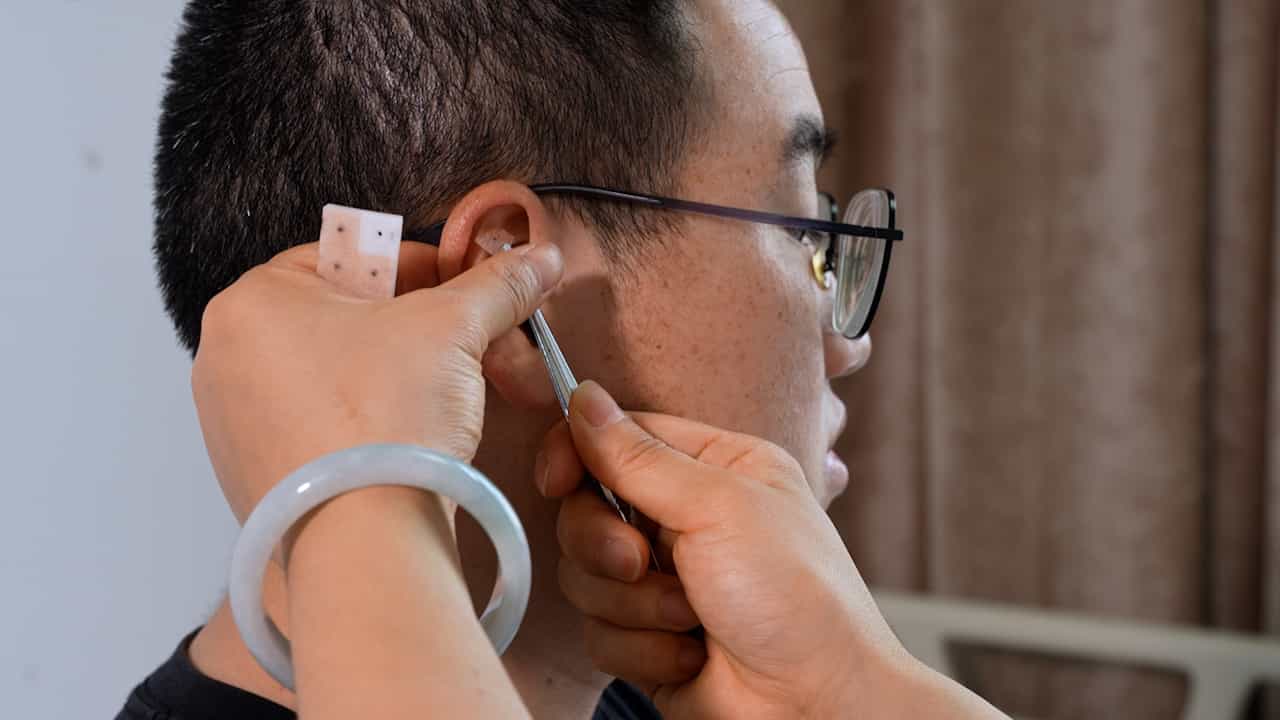

Auricular Acupressure as an Adjuvant Treatment for Wheezing in Stable Chronic Obstructive Pulmonary Disease
Published on: May 10, 2024
Pertinent issues in diagnosis and management of wheezing in under-five children at community level
1Department of Pediatrics, University College of Medical Sciences (University of Delhi) and GTB Hospital, Delhi 110 095, India. shahdheeraj@hotmail.com

Insights
Wheezing is common in children with acute respiratory infections, affecting up to 75% with pneumonia. Current diagnostic methods for wheeze are insufficient, highlighting the need for updated community management strategies.
Area of Science:
- Pediatrics
- Respiratory Medicine
- Infectious Diseases
Background:
- Wheezing is a frequent symptom in children experiencing acute respiratory infections (ARIs), often accompanying pneumonia.
- Up to 75% of children diagnosed with pneumonia or severe pneumonia (WHO criteria) exhibit wheezing.
- Current community-based diagnostic and management approaches for wheeze are inadequate.
Purpose of the Study:
- To highlight the limitations of current wheeze diagnosis in community settings.
- To emphasize the need for updated management strategies for wheezing in children with ARIs.
- To explore the potential role of inhaled bronchodilators and historical data in diagnosing and managing wheeze.
Main Methods:
- Review of existing literature and clinical observations regarding wheezing in pediatric ARIs.
- Analysis of the prevalence of wheezing in children with pneumonia.
- Evaluation of diagnostic indicators such as audible wheeze and history of respiratory distress.
- Assessment of the response to inhaled bronchodilator therapy.
Main Results:
- Audible wheeze is detected in less than one-third of wheezy children, indicating its unreliability as a sole diagnostic criterion.
- A history of prior respiratory distress episodes demonstrates high sensitivity for diagnosing wheezy disorders.
- Inhaled bronchodilator treatments can normalize respiratory rate and reduce chest indrawing in a substantial number of children.
- The effectiveness of current community-based ARI management programs in addressing wheezing requires further investigation.
Conclusions:
- Wheezing is a prevalent and significant clinical feature in pediatric acute respiratory infections.
- Relying solely on audible wheeze for diagnosis is insufficient; a comprehensive approach including patient history is crucial.
- Inhaled bronchodilators show promise in managing acute wheezing episodes in children.
- Further operational research is essential to integrate effective wheeze management into community-based ARI programs.
Abstract:
Wheezing in acute respiratory infections is a rule rather than exception. A large proportion of children (up to 75%) having pneumonia or severe pneumonia as per WHO definitions have associated wheezing. The current strategies to diagnose and manage wheeze in the community need to be updated, as audible wheeze is present in only less than one third of wheezy children, and can not be relied upon solely. A history of previous episodes of respiratory distress has a high sensitivity to diagnose wheezy disorders. In a significant proportion of children, the respiratory rate comes back to normal and the chest indrawing disappear after two to three cycles of inhaled bronchodilator medications. Operational research is needed to evaluate the feasibility of including management of wheezing in the community based ARI management programs.

Related Concept Videos
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:30
Asthma-IV: Nursing Management
First, in...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:28
Asthma I: Introduction
 01:29
Asthma-I: Introduction
 01:13
Asthma III: Clinical Manifestations