Related Experiment Video
Updated: Jun 16, 2026
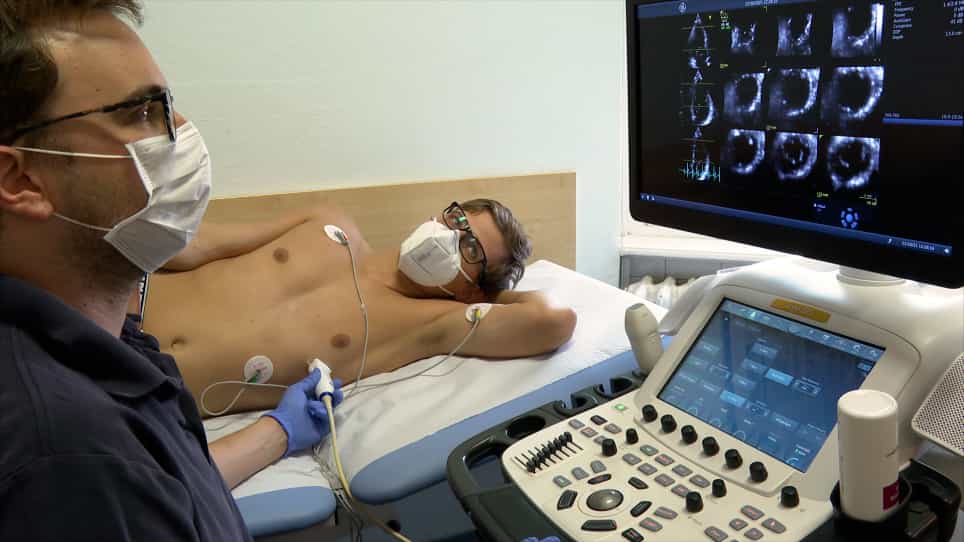

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Association of hyperhomocysteinemia with left ventricular dilatation and mass in human heart
Peter Alter1, Heinz Rupp, Marga B Rominger
1Internal Medicine-Cardiology, Philipps University, Marburg, Germany. alter@staff.uni-marburg.de

Insights
High homocysteine levels are linked to enlarged left ventricles (LV) in dilated cardiomyopathy. This suggests hyperhomocysteinemia contributes to LV dilatation and hypertrophy, potentially through oxidative stress.
Area of Science:
- Cardiology
- Biochemistry
- Medical Imaging
Background:
- Hyperhomocysteinemia is a known risk factor for ischemic heart disease.
- Mechanisms linking hyperhomocysteinemia to non-ischemic heart failure, specifically dilated cardiomyopathy, are being explored.
- This study investigates the association between elevated homocysteine levels and left ventricular (LV) changes in dilated cardiomyopathy.
Purpose of the Study:
- To determine if hyperhomocysteinemia is associated with left ventricular (LV) dilatation and hypertrophy in patients with dilated cardiomyopathy.
- To explore the relationship between homocysteine levels and cardiac structural and functional parameters.
Main Methods:
- Homocysteine levels were measured in 66 individuals with suspected cardiomyopathy.
- Cardiac magnetic resonance imaging (CMR) was utilized to assess LV volume, mass, and wall stress.
- Patients were categorized based on homocysteine levels and compared for cardiac parameters.
Main Results:
- Hyperhomocysteinemia ( > 12 micromol/L) was prevalent in 68% of patients.
- Patients with hyperhomocysteinemia exhibited significantly greater LV mass compared to those with normal homocysteine levels (83 vs. 67 g/m²).
- Elevated homocysteine correlated with increased LV mass, LV end-diastolic volume (LVEDV), and LV end-systolic volume (LVESV), and LV dilatation was more common in patients with hyperhomocysteinemia.
Conclusions:
- Hyperhomocysteinemia is implicated in disproportionate LV dilatation in dilated cardiomyopathy.
- The observed hypertrophy may not adequately compensate for increased wall stress.
- Increased oxidative stress due to hyperhomocysteinemia could be a mechanism contributing to muscle fiber changes and LV remodeling.
Background:
Hyperhomocysteinemia is a risk factor for ischemic heart disease. Several other mechanisms apply also to dilative types of heart failure of various, non-ischemic etiologies. We hypothesized that hyperhomocysteinemia is associated with left ventricular (LV) dilatation and hypertrophy in dilative cardiomyopathy.
Methods:
Homocysteine was measured in 66 individuals with suspected cardiomyopathy. Cardiac magnetic resonance imaging was used to assess LV volume, mass, and wall stress.
Results:
Hyperhomocysteinemia (> 12 micromol/L) was found in 45 patients (68%). LV mass was greater in these patients compared with individuals with normal homocysteine (83+/-27 vs. 67+/-19 g/m(2); p<0.02). Homocysteine was increased in patients with increased brain natriuretic peptide > or = 100 pg/mL (18.3+/-5.9 vs. 14.9+/-5.1 micromol/L; p=0.018). LV mass, LV end-diastolic and end-systolic volume (LVEDV, LVESV) were significantly increased in individuals in the upper quartile compared with the lower quartile (90+/-25 vs. 65+/-18 g/m(2), p=0.021; 114+/-50 vs. 71+/-23 mL/m(2), p=0.042; 76+/-51 vs. 36+/-22 mL/m(2), p=0.045). LV dilatation (LVEDV > or = 90 mL/m(2)) was more common in hyperhomocysteinemia (> 12 micromol/L, p=0.0166). Normalized LV mass was correlated with homocysteine (r=0.346, p=0.065). Homocysteine was not significantly correlated with LVEDV (r=0.229, p=0.065), LV end-diastolic wall stress (r=0.226, p=0.069) and LV ejection fraction.
Conclusions:
Hyperhomocysteinemia appears to be, at least in part, involved in a disproportional LV dilatation, where the ensuing hypertrophy is not sufficient to compensate for the increased wall stress. A potential mechanism is the hyperhomocysteinemia associated increase in oxidative stress that favors muscle fiber slippage.

Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Heart Failure II: Pathophysiology
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:22
Mitral Stenosis I: Introduction
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:20
Mitral Regurgitation I: Introduction