Related Experiment Video
Updated: Jun 16, 2026
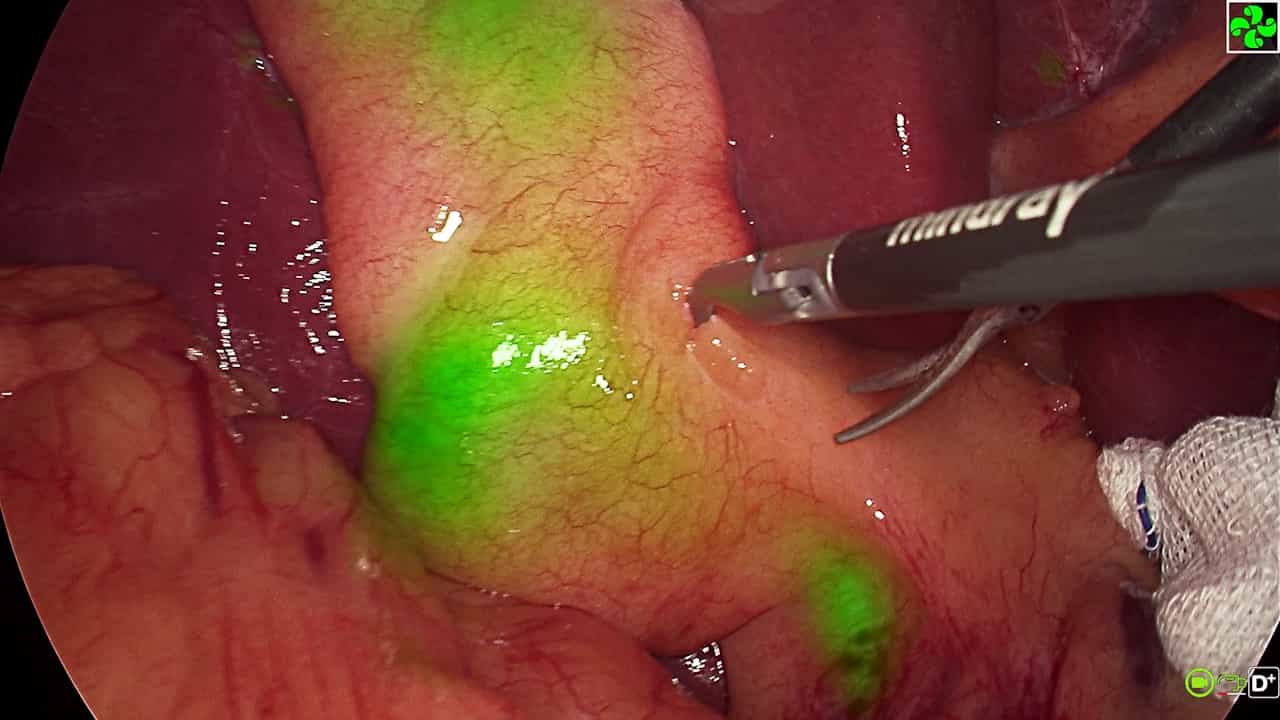

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Conservative treatment for acute cholecystitis: clinical and radiographic predictors of failure
Orly Barak1, Ram Elazary, Liat Appelbaum
1Department of General Surgery, Hadassah-Hebrew University Medical Center, Jerusalem, Israel.

Background:
Current treatment options for acute calculous cholecystitis include either early cholecystectomy, or conservative treatment consisting of intravenous antibiotics and an interval cholecystectomy several weeks later. Percutaneous drainage is reserved for patients in whom conservative therapy failed or as a salvage procedure for high risk patients.
Objective:
To identify clinical and radiographic factors leading to failure of conservative treatment.
Methods:
We prospectively collected data on consecutive patients admitted with the diagnosis of acute cholecystitis. Parameters were compared between patients who were successfully treated conservatively and those who required percutaneous cholecystostomy. Logistic regression analysis was performed to identify predictors for failure of conservative treatment.
Results:
The study population comprised 103 patients with a median age of 60 who were treated for acute cholecystitis. Twenty-seven patients (26.2%) required PC. On univariate analysis, age above 70 years, diabetes, elevated white blood cell count, tachycardia (> 100 beats/min) at admission, and a distended gallbladder (> 5 cm transverse diameter) were found to be significantly more common in the PC group (P < 0.001). WBC was higher in the PC group throughout the initial 48 hours. On multivariate analysis, age above 70 (odds ratio 3.6), diabetes (OR 9.4), tachycardia at admission (OR 5.6), and a distended gallbladder (OR 8.5) were predictors for cholecystostomy (P < 0.001). Age above 70 (OR 5.2) and WBC $15,000 (OR 13.7) were predictors for failure of conservative treatment after 24 and 48 hours (P < 0.001).
Conclusions:
Age above 70, diabetes, and a distended gallbladder are predictors for failure of conservative treatment and such patients should be considered for early cholecystostomy. Persistently elevated WBC (> 15,000) suggests refractory disease and should play a central role in the clinical follow-up and decision-making process for elderly patients with acute cholecystitis.
Related Concept Videos
 01:20
Cholecystitis
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...