Related Experiment Video
Updated: Jun 16, 2026
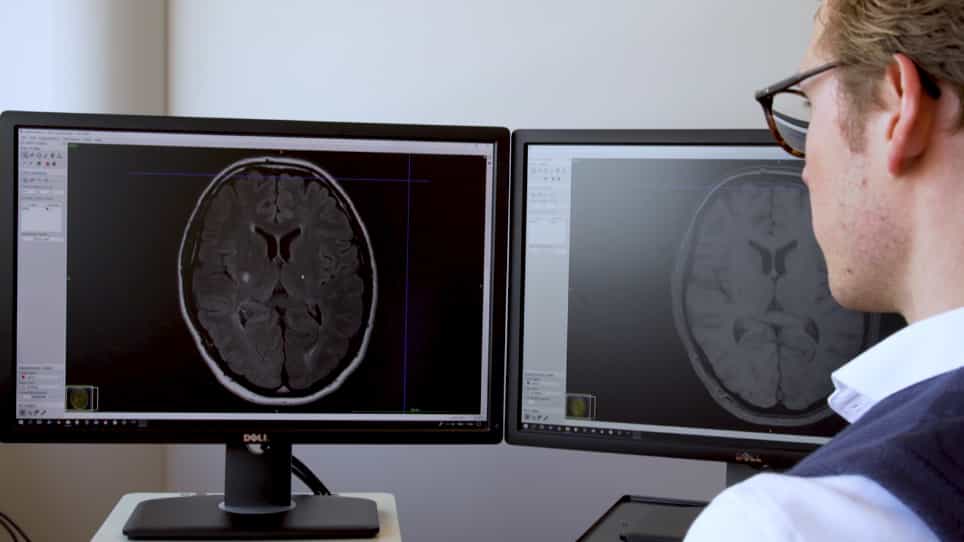

Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
Associations of clinical stroke misclassification ('clinical-imaging dissociation') in acute ischemic stroke
Gillian Potter1, Fergus Doubal, Caroline Jackson
1Department of Clinical Neurosciences, University of Edinburgh, Western General Hospital, Edinburgh, UK.

Background:
Up to 20% of lacunar infarcts are clinically misdiagnosed as cortical infarcts and vice versa. The reasons for this discrepancy are unclear. We assessed clinical and imaging features which might explain this 'clinical-imaging dissociation' (C-ID).
Methods:
Patients with an acute stroke syndrome (cortical or lacunar) underwent magnetic resonance imaging including diffusion-weighted imaging (DWI). We recorded DWI-positive infarcts and proximity to cortex for small subcortical infarcts. We examined factors associated with C-ID.
Results:
137 patients with a mild cortical or lacunar syndrome had an acute ischemic lesion on DWI. Of these, 21/93 (23%) with a cortical syndrome had an acute lacunar infarct and 7/44 (16%) with a lacunar syndrome had an acute cortical infarct. From 72 patients with an acute lacunar infarct on DWI, lesion proximity to cortex (odds ratio (OR) 14.5, 95% confidence interval (CI) 1.61-130.1), left hemisphere location (OR 8.95, 95% CI 1.23-64.99) and diabetes (OR 17.1, 95% CI 1.49-196.16) predicted C-ID. On multivariate analysis of all 137 patients, C-ID was associated with diabetes (OR 7.12, 95% CI 1.86-27.2).
Conclusions:
C-ID occurs in a fifth of patients with mild stroke. Lacunar infarcts lying close to cortex are more likely to cause cortical symptoms. Diabetes is associated with any clinical-imaging mismatch. Stroke misclassification which can arise with clinical classification alone should be minimized in research by verification with high-sensitivity imaging.
Related Concept Videos
 01:15
Ischemic Stroke ll: Pathophysiology
 01:15
Ischemic Stroke l: Introduction